Related Experiment Video
Updated: Aug 10, 2026


Continuous Manual Exchange Transfusion for Patients with Sickle Cell Disease: An Efficient Method to Avoid Iron Overload
Published on: March 14, 2017
High serum transferrin receptor level in anemia of chronic disorders indicates coexistent iron deficiency
1Hematology Section, Department of Laboratory Medicine, P.D. Hinduja National Hospital and Medical Research Centre, Mumbai, India. dr_adasgupta@hindujahospital.com

Blood transferrin receptor (TR) level is largely determined by the quantum of erythropoiesis and by intracellular iron content of the cells of the erythroid lineage. Hence, a high serum TR level has been found to be useful in distinguishing iron deficiency anemia (IDA) from anemia of chronic disorders (ACD). In order to examine its potential role in the diagnosis of concomitant iron deficiency in ACD, we determined serum TR levels in 130 cases of ACD, in 25 cases of IDA, and in 40 normal adults. As expected, all patients of IDA had significantly higher serum TR levels compared to the normal subjects (4.2-19.2 microg/dL vs. 1.3-3.0 microg/dL) (P < 0.002). In 11/25 cases of IDA, the total iron-binding capacity (TIBC) was in the normal range although bone marrow iron store was absent and serum TR levels were high, thereby highlighting the superiority of TR level in the diagnosis of iron deficiency compared to TIBC. Although 54% (70/130) patients of ACD had normal or low serum TR levels (0.9-3.0 microg/dL) as expected, in 46% (60/130) of ACD patients, serum TR levels were high (3.2-11.0 microg/dL). Mean corpuscular volume, red cell distribution width, and transferrin saturation were significantly lower (P < 0.001) in the latter group of patients compared to the former, and these parameters resembled those in IDA patients. Also, serum iron was lower and TIBC was higher in this group of ACD patients compared to those with normal or low serum TR. All these features point to an "IDA-like" profile of ACD patients with high TR and support the possibility of co-existent iron deficiency in this subgroup of ACD patients. In light of these observations it would be prudent to treat ACD patients with high serum TR levels with iron replacement therapy.
Blood transferrin receptor (TR) level is largely determined by the quantum of erythropoiesis and by intracellular iron content of the cells of the erythroid lineage. Hence, a high serum TR level has been found to be useful in distinguishing iron deficiency anemia (IDA) from anemia of chronic disorders (ACD). In order to examine its potential role in the diagnosis of concomitant iron deficiency in ACD, we determined serum TR levels in 130 cases of ACD, in 25 cases of IDA, and in 40 normal adults. As expected, all patients of IDA had significantly higher serum TR levels compared to the normal subjects (4.2-19.2 microg/dL vs. 1.3-3.0 microg/dL) (P < 0.002). In 11/25 cases of IDA, the total iron-binding capacity (TIBC) was in the normal range although bone marrow iron store was absent and serum TR levels were high, thereby highlighting the superiority of TR level in the diagnosis of iron deficiency compared to TIBC. Although 54% (70/130) patients of ACD had normal or low serum TR levels (0.9-3.0 microg/dL) as expected, in 46% (60/130) of ACD patients, serum TR levels were high (3.2-11.0 microg/dL). Mean corpuscular volume, red cell distribution width, and transferrin saturation were significantly lower (P < 0.001) in the latter group of patients compared to the former, and these parameters resembled those in IDA patients. Also, serum iron was lower and TIBC was higher in this group of ACD patients compared to those with normal or low serum TR. All these features point to an "IDA-like" profile of ACD patients with high TR and support the possibility of co-existent iron deficiency in this subgroup of ACD patients. In light of these observations it would be prudent to treat ACD patients with high serum TR levels with iron replacement therapy.


Related Concept Videos
 01:14
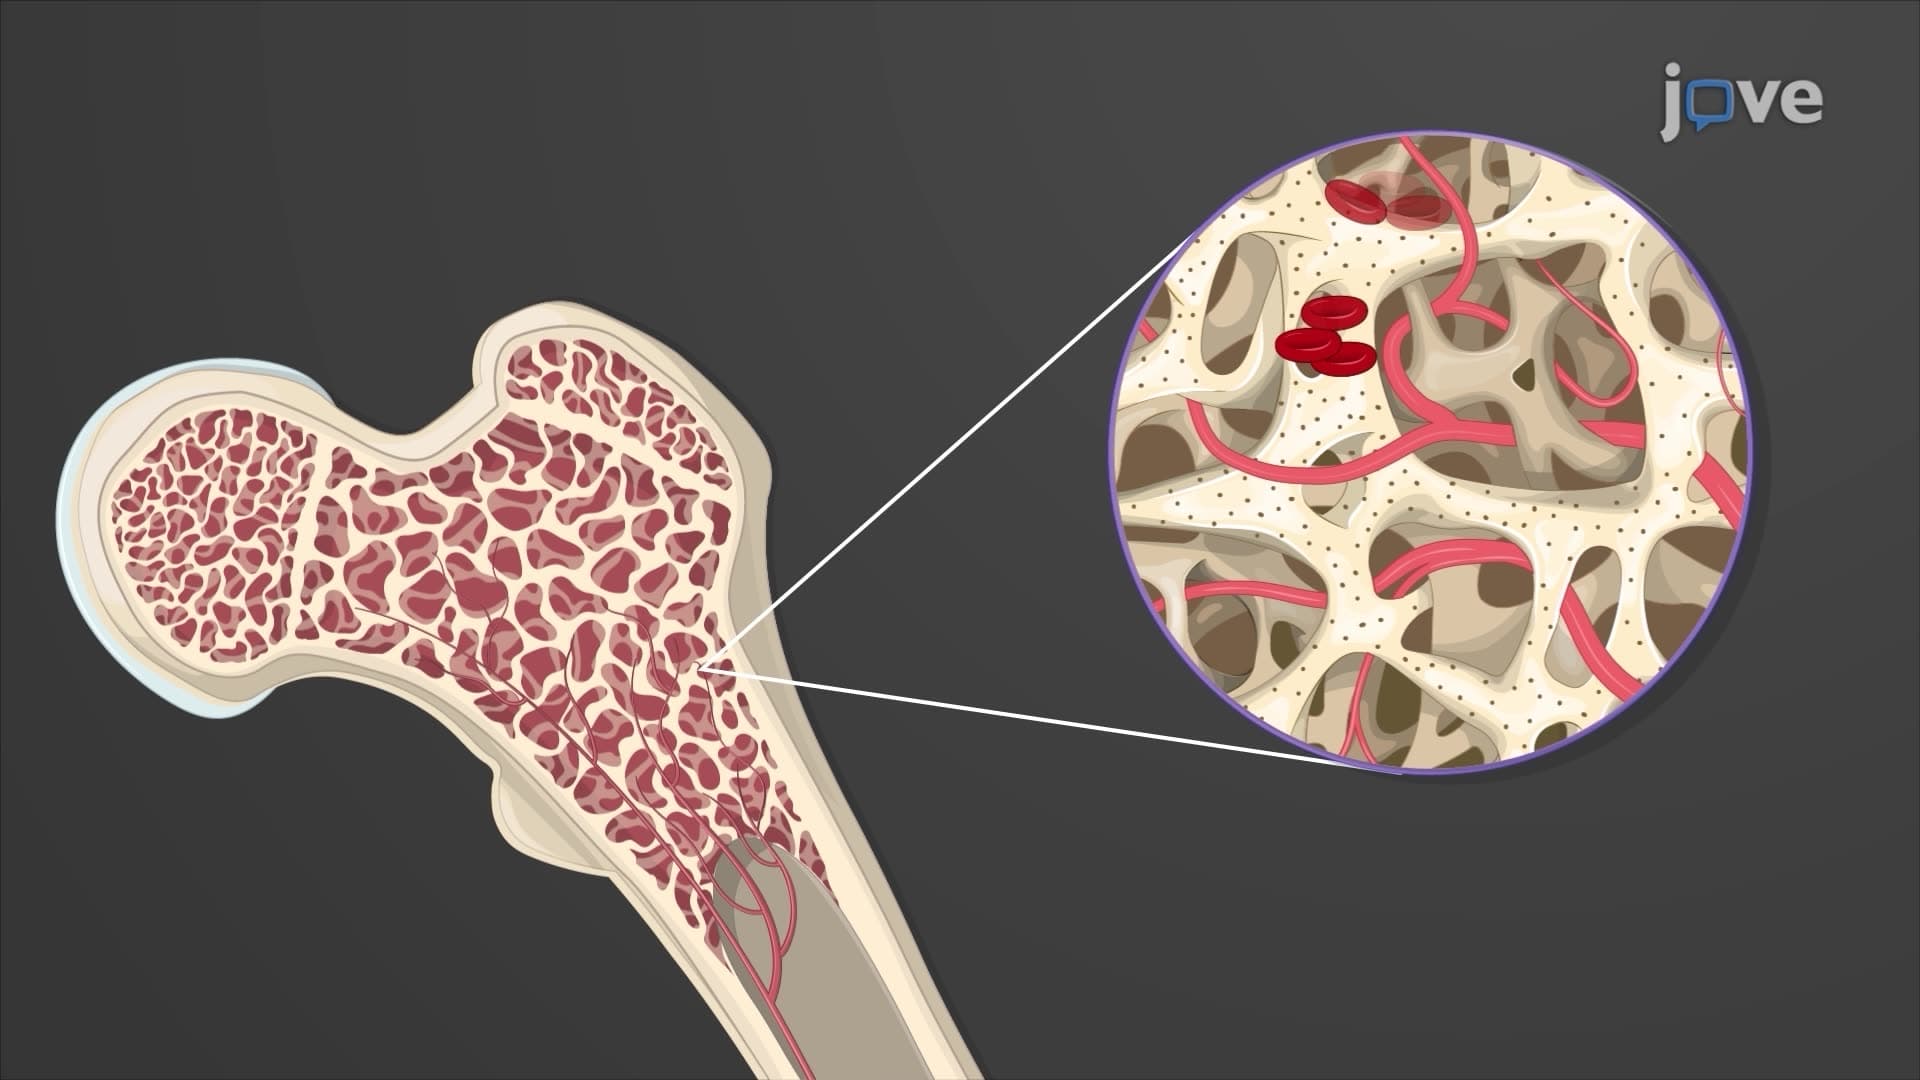
Erythropoiesis
 01:22
Lifecycle of Erythrocytes
The resident phagocytic macrophages deal with these damaged cells by engulfing them and separating their globin and heme groups.
 01:27
Disorders of Erythrocytes
Erythrocyte disorders can be broadly categorized into two main types: anemic and polycythemic conditions.
A low oxygen-carrying capacity of the blood due to the loss, lower production, or destruction of erythrocytes is termed anemia. Hemorrhagic anemia, for example, occurs when bleeding from an external wound or internal ulcer reduces erythrocyte counts.
On the other...
 01:25
Blood Studies for Cardiovascular System III: Serum Lipid Profile
Serum lipids are fats and fatty substances in the blood and are crucial for various bodily functions, including energy storage, cellular structure, and hormone production. Serum lipids consist of cholesterol, triglycerides, and phospholipids.
Cholesterol is a soft, fat-like substance found in all body cells. It is crucial for producing hormones, vitamin D, and substances that aid...
 01:24
Cirrhosis II: Pathophysiology
 01:22
Portal Hypertension