[Cholestasis and vomiting: unusual differential diagnosis in a case of Peutz-Jeghers syndrome]
1Klinik und Poliklinik für Innere Medizin I, Klinikum der Universität Regensburg. falitsa.mandraka@medicdat.de

History And Clinical Findings:
A 54-year-old patient with painless jaundice and vomiting had been diagnosed with a Peutz-Jeghers syndrome 20 years before.
Investigations:
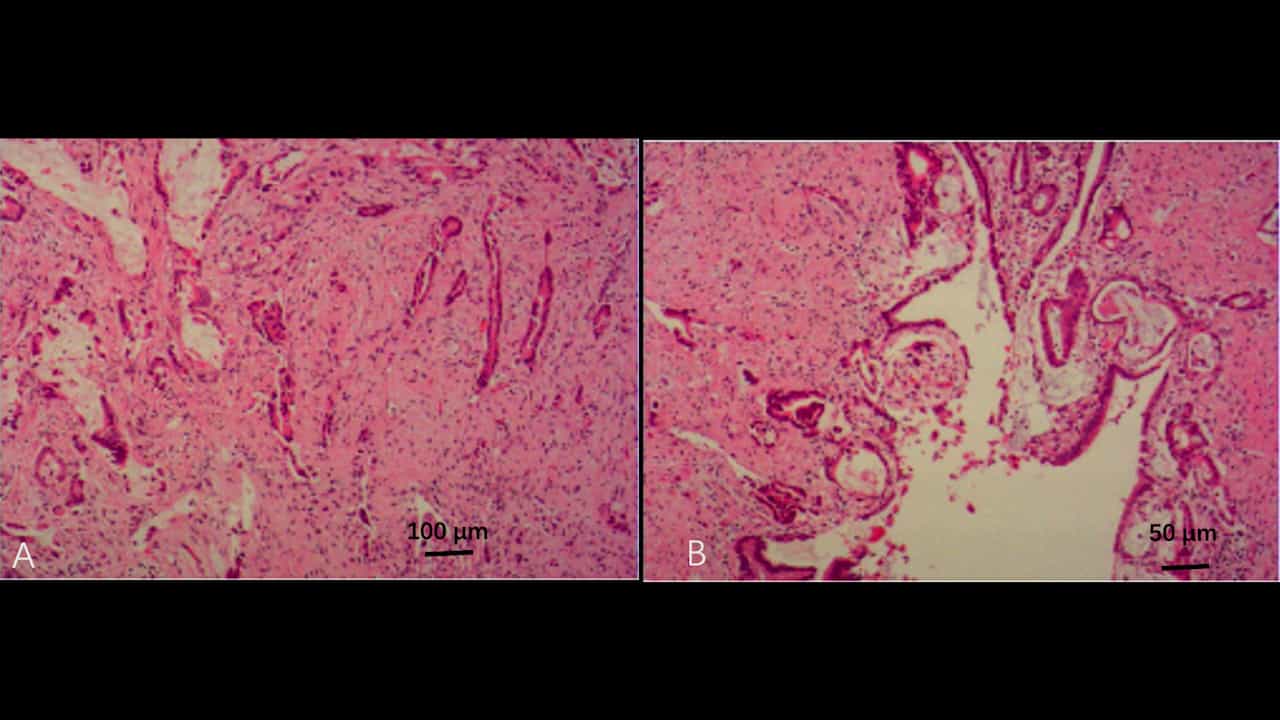
The blood analysis showed a cholestatic constellation as well as increased transaminases. Sonographic, radiological, endoscopic and histological findings indicated multiple hamartomatous polyps of the Peutz-Jeghers' type in the entire small and large bowel with occlusion of the papilla of Vater and the superior gastrointestinal tract by a big polyp.
Treatment And Course:
After an initial percutaneous transhepatic cholangiographic drainage, Whipple's operation and a segmental resection of small and large bowel were performed. A highly differentiated adenocarcinoma of the duodenum was found in the resected specimen.
Conclusion:
This case demonstrates the potentially severe complications of a Peutz-Jeghers syndrome that had been neglected for years.
Related Concept Videos
 01:21
Chronic Pancreatitis II: Pathophysiology
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:26
Gastritis II: Pathophysiology
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:20
Cholecystitis
 01:22
Pathophysiology of Vomiting