Related Experiment Video
Updated: Sep 26, 2026
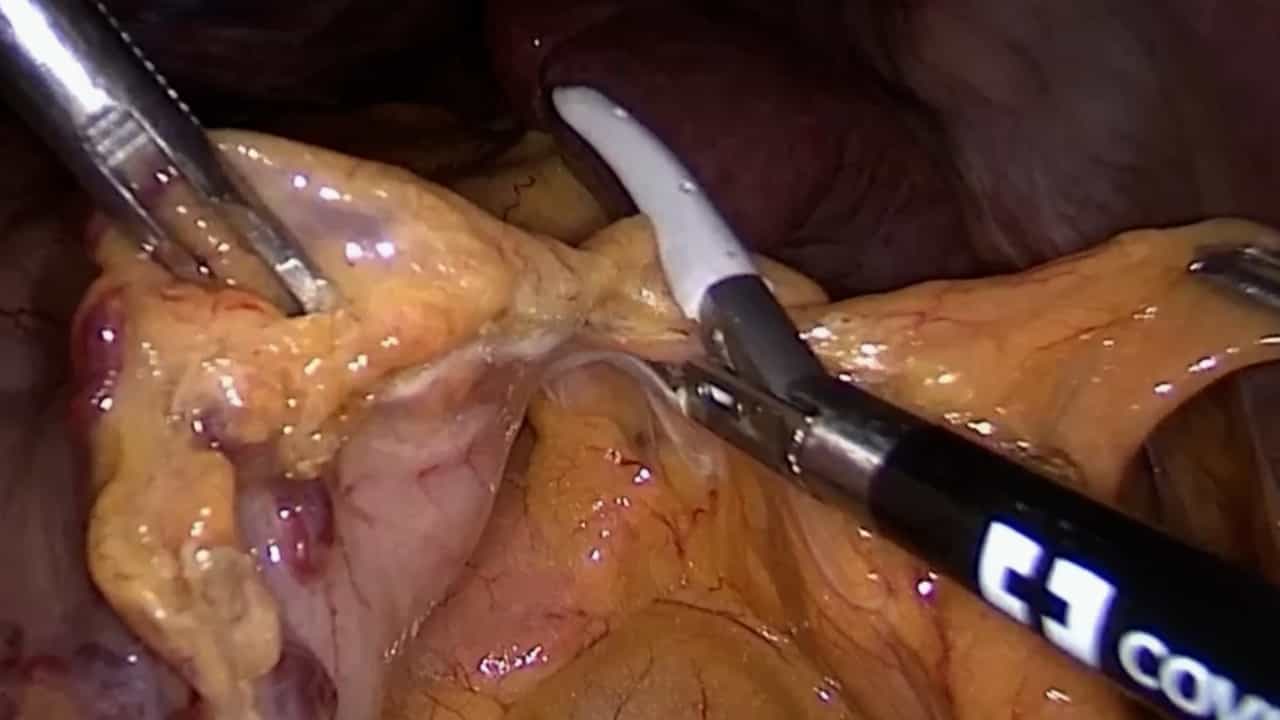
Application of Laparoscopic Partial Splenectomy with Total Blood Flow Occlusion in Benign Splenic Lesions
Published on: December 20, 2024
Role of splenectomy in chronic idiopathic thrombocytopenic purpura
S Srinivasan1, K Sabapathy, T P R Bharadwaj
1Department of Hematology, Government General Hospital, Chennai, India.

Insights
Splenectomy offers good long-term remission for chronic idiopathic thrombocytopenic purpura (ITP) patients who initially respond to steroids. Key predictors for sustained remission include steroid response and post-operative platelet count.
Area of Science:
- Hematology
- Surgical Oncology
Background:
- Chronic idiopathic thrombocytopenic purpura (ITP) is an autoimmune disorder characterized by low platelet counts.
- Splenectomy is a treatment option for ITP, but its long-term efficacy and predictive factors for remission require evaluation.
Purpose of the Study:
- To assess the effectiveness of splenectomy in achieving long-term remission in chronic ITP patients.
- To identify factors that predict sustained remission after splenectomy for ITP.
Main Methods:
- Retrospective analysis of 364 chronic ITP patients diagnosed between 1983-1996.
- Evaluation of 71 patients who underwent splenectomy, with follow-up for an average of 58 months.
- Statistical analysis using non-parametric tests (Chi-square) to identify predictors of remission.
Main Results:
- Short-term (1 month) complete response rate was 82%, with 42% maintaining complete response at 60 months.
- Long-term remission was significantly predicted by preoperative response to steroids (p=0.018) and postoperative platelet count > 300 x 10(9)/L (p=0.013).
- Age, sex, initial platelet count, and time to splenectomy were not significant predictors of long-term remission.
Conclusions:
- Patients with initial complete response to steroids and postoperative platelet count > 300 x 10(9)/L are likely to achieve long-term remission.
- Splenectomy is a safe procedure for chronic ITP with minimal complications.
- Splenectomy provides good long-term remission for steroid-refractory chronic ITP patients.
Aim Of The Study:
To evaluate the usefulness of splenectomy and factors which predict long term remission in chronic idiopathic thrombocytopenic purpura (ITP).
Methods:
We reviewed the data of 364 patients diagnosed as chronic ITP between January 1983 to December 1996 of whom 71 patients underwent splenectomy. The patients were followed up for an average period of 58 months and the short and long term response to splenectomy were analyzed at the end of one month and 60 months, respectively.
Results:
At the end of one month after splenectomy, 82% had complete response, 7% partial response and 11% had no response. At the end of 60 months, 42% maintained complete response, 7% partial response, 34% had no response and 17% were lost to follow up. The results were statistically evaluated by using non-parametric test (Chi-square test) to age, sex, platelet count prior to treatment, initial response to steroids, time interval between diagnosis and splenectomy and post-operative platelet count. Of these factors only preoperative response to steroids (p value = 0.018303) and postoperative platelet count (p value = 0.013536) were found to be significant, statistically to predict long term remission. Age, sex, initial platelet count and time interval between diagnosis and splenectomy didn't seem to be statistically significant.
Conclusion:
This study suggests, that patients with an initial complete response to steroids and a post-operative platelet count > 300 x 10(9)/L at the time of discharge were associated with a long term remission. Splenectomy in ITP is a safe procedure with minimal morbidity and mortality and gives a good long term remission in steroid- failure patients with chronic ITP.
Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:24
Disorders of Hemostasis
Thromboembolic Disorders
Two factors primarily cause thromboembolic conditions.