Related Experiment Video
Updated: Sep 25, 2026
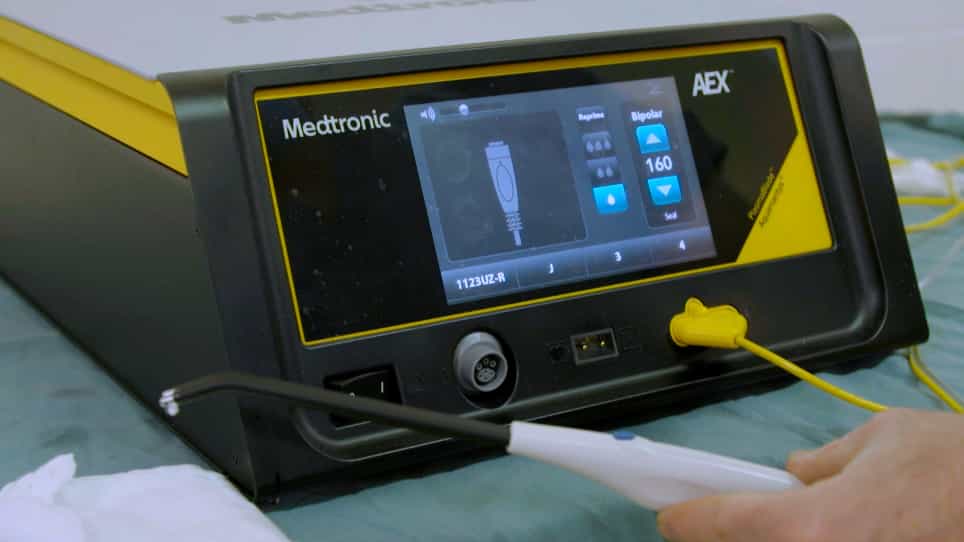

A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Multiplicity of solid organ injury: influence on management and outcomes after blunt abdominal trauma
Ajai K Malhotra1, Rifat Latifi, Timothy C Fabian
1Department of Surgery, Medical College of Virginia, Virginia Commonwealth University, Richmond, 23298, USA. akmalhot@hsc.vcu.edu

Objective:
The current study was undertaken to examine how concomitant injury to liver and spleen after blunt abdominal trauma affects management and outcomes.
Methods:
This study was a retrospective chart review of all blunt abdominal trauma patients admitted with a diagnosis of liver or spleen injury at two Level I trauma centers over a 4-year period. Presentation, injury grade, management, and outcomes were analyzed. Patients with single-organ injury (liver or spleen) were compared with patients having injury to both organs (liver and spleen). Significance was set at 95% confidence intervals.
Results:
Of 1,288 patients who met entry criteria, 1,125 had single (spleen, 573; liver, 552) organ injury (group S) and 163 had injury to both organs (group B). Group B patients had significantly higher Injury Severity Score, higher admission lactate, and lower admission systolic blood pressure and base excess. Eighty-one percent (915 of 1,125) of group S and 69% (112 of 163) of group B patients were managed nonoperatively (p < 0.05). Of the nonoperatively managed patients, 5.8% (53 of 915) in group S and 11.6% (13 of 112) in group B failed this form of therapy (p < 0.05). Higher failure rate in group B was because of bleeding from injured solid organ(s), and not non-solid organ related failures. Mortality, intensive care unit and hospital lengths of stay, and transfusion requirements were all significantly higher in group B.
Conclusion:
Blunt trauma patients with concomitant injury to liver and spleen have higher Injury Severity Score, mortality, lengths of stay, and transfusion requirements. There is a higher failure rate with nonoperative management, and therefore extra vigilance is warranted when choosing this form of therapy in the presence of injury to both organs.
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:07
Intestinal Obstruction II: Pathophysiology
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...
 01:21
Acute Pancreatitis II: Pathophysiology