Related Experiment Video
Updated: Aug 12, 2026
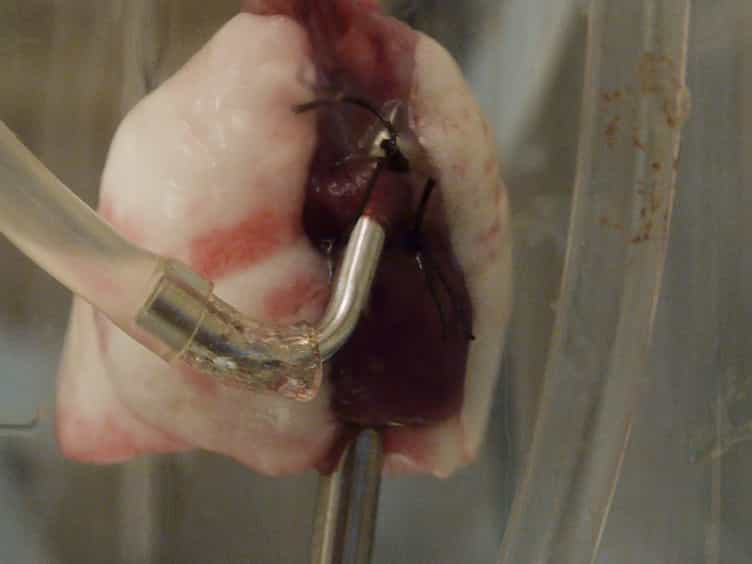
Method of Isolated Ex Vivo Lung Perfusion in a Rat Model: Lessons Learned from Developing a Rat EVLP Program
Published on: February 25, 2015
Synchronized independent lung ventilation in palliated congenital heart disease with variable sources of pulmonary
M C Almodovar1, P C Laussen, S J Roth
1Departments of Cardiology (Drs. Almodovar and Roth) and Anesthesia (Dr. Laussen), Children's Hospital, Boston, MA.

Abstract:
OBJECTIVE: Presentation of two patient studies demonstrating the use of synchronized independent lung ventilation in the management of acute respiratory failure in patients with complex palliated congenital heart disease and variable sources of pulmonary blood flow. DESIGN: Clinical course of two patients. SETTING: Cardiac intensive care unit in a tertiary care, university-affiliated pediatric teaching hospital. PATIENTS: Patient 1 was a 22-yr-old woman with a single ventricle and right lung blood flow supplied by a classic Glenn shunt and left lung blood flow through a systemic-to-pulmonary artery shunt. Patient 2 was a 12-yr-old boy with tetralogy of Fallot and complete common atrioventricular canal defect with right lung blood flow supplied by a classic Glenn shunt and left lung blood flow supplied by the right ventricle. Both patients presented with acute, left-sided lung disease and hypoxemia. INTERVENTIONS: We used selective bronchial intubation via a double-lumen tracheal tube with a bronchial extension for synchronized independent lung ventilation to permit high-pressure ventilation of the abnormal left lung low-pressure ventilation of the normal right lung supplied by a Glenn shunt. Inhaled nitric oxide was administered to both patients and continued in one when improved oxygenation was observed. MEASUREMENTS AND MAIN RESULTS: Serial arterial blood gas measurements, mechanical indices of pulmonary function, and chest radiographs were closely followed. Synchronized independent lung ventilation contributed to improvements in systemic arterial blood oxygenation and alveolar ventilation allowing resumption of conventional ventilation in both patients. No adverse effects related to bronchial tube placement or maintenance occurred. CONCLUSION: Independent lung ventilation is an effective means of isolating the two lungs for differential ventilation, as well as the selective delivery of inhaled medications. In patients with unilateral lung disease and a Glenn shunt supplying the unaffected lung, selective lung ventilation allows aggressive treatment of the abnormal lung while optimizing flow through the Glenn shunt to maximize effective pulmonary blood flow, systemic oxygenation, and hemodynamics.
Related Concept Videos
 01:29
Mechanical Ventilation I: Indication and Settings
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management