Related Experiment Video
Updated: Aug 14, 2026
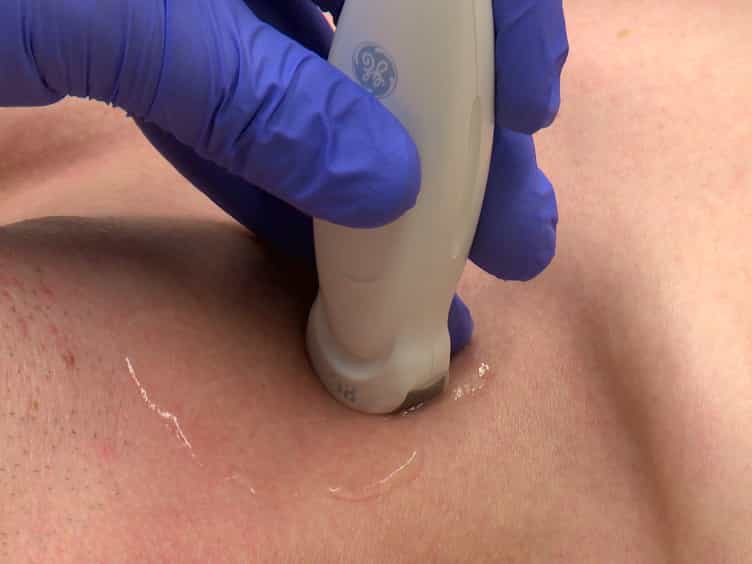

The Supraclavicular Fossa Ultrasound View for Central Venous Catheter Placement and Catheter Change Over Guidewire
Published on: December 23, 2014
Persistent left superior vena cava and central venous catheter position: clinical impact illustrated by four cases
W Schummer1, C Schummer, R Fröber
1Clinic for Anesthesiology and Intensive Care Medicine, Friedrich-Schiller University, Bachstrasse 18, 07743 Jena, Germany. cwsm.schummer@gmx.de

Insights
A persistent left superior vena cava (LSVC) is a common vascular variation. Recognizing LSVC variations is crucial for safe central venous catheterization and avoiding serious complications.
Area of Science:
- Vascular anatomy
- Embryology
- Medical imaging
Background:
- Vascular variations, such as a persistent left superior vena cava (LSVC), are frequently discovered incidentally.
- LSVC occurs in 0.3-0.5% of healthy individuals and 4% of those with congenital heart disease.
- Complications like shock and cardiac arrest can arise during catheterization in patients with LSVC.
Observation:
- The embryogenesis and anatomical variations of persistent LSVC are detailed.
- A novel classification system for superior vena cava anatomy is proposed based on central venous catheter positioning on chest radiographs.
- The classification includes Type I (normal), Type II (LSVC only), Type IIIa (connected right and left SVC), and Type IIIb (disconnected right and left SVC).
Findings:
- The study presents four clinical cases illustrating the proposed classification.
- The classification aids in identifying and categorizing LSVC variations.
- Difficulties in central venous catheterization may indicate underlying SVC anomalies.
Implications:
- Awareness of LSVC variations is essential for clinicians performing central venous catheterization.
- The proposed classification can improve the diagnosis and management of patients with SVC anomalies.
- Understanding these variations can prevent serious complications during medical procedures.
Abstract:
Variations in the course of the blood vessels are often incidental findings during clinical examination. A persistent left superior vena cava (LSVC) is really not rare (healthy individuals, 0.3-0.5%; patients with congenital heart disease, 4%) and serious complications have been described during catheterization in adults with LSVC (shock, cardiac arrest, angina). Therefore variations of the superior vena cava should be considered, especially when central venous catheterization via the subclavian or internal jugular vein is difficult. We describe the embryogenesis and the anatomic variations of persistent LSVC. Subsequently we suggest a classification of superior vena cava according to the positioning of a central venous catheter on the chest radiograph: type I, normal anatomy; type II, only persistent left superior vena cava; type IIIa, right and left superior vena cava with connection; type IIIb, right and left superior vena cava without connection. This classification is illustrated by four clinical cases.
Related Concept Videos
 01:11
Overview of Systemic Veins
The coronary sinus, the heart's principal vein, resides in the coronary sulcus on the heart's posterior aspect. This broad venous channel receives nearly all venous blood from the myocardium, the heart muscle. It is fed by three primary veins: the great cardiac vein, the middle...
 01:21
Cardiac Catheterization II: Right Heart Catheterization
 01:24
Cardiac Catheterization III: Left Heart Catheterization
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis IV: Nursing Management