Related Experiment Video
Updated: Sep 20, 2026


Mouse Model of Pressure Ulcers After Spinal Cord Injury
Published on: March 9, 2019
A sore spot in pediatrics: risk factors for pressure ulcers
1Shriners Hospitals for Children-Houston, Houston, TX, USA.

Insights
Pediatric pressure ulcers, often linked to myelodysplasia, primarily affect the feet and lower extremities. Key risk factors include paralysis, immobility, and insensate areas, with sacral ulcers appearing in older children and wheelchair users.
Area of Science:
- Pediatric wound care
- Dermatology
- Pediatric surgery
Background:
- Pressure ulcers are a significant concern in pediatric patients, impacting quality of life and healthcare costs.
- Understanding the specific risk factors and common locations of pressure ulcers in children is crucial for effective prevention and management.
- This study focuses on pressure ulcers in children, differentiating them from other skin breakdown issues.
Purpose of the Study:
- To investigate the incidence and characteristics of pressure ulcers in a pediatric population.
- To identify primary diagnoses and associated risk factors contributing to pressure ulcer development in children.
- To determine the most common sites for pressure ulcers in pediatric patients and factors influencing their location.
Main Methods:
- A retrospective, exploratory study design was employed.
- Data were collected from children seen in a hospital's wound clinic over a 1-year period.
- Analysis focused on 50 pediatric patients diagnosed with pressure ulcers.
Main Results:
- Myelodysplasia was the primary diagnosis in children with pressure ulcers.
- Identified risk factors included paralysis, insensate areas, high activity, and immobility.
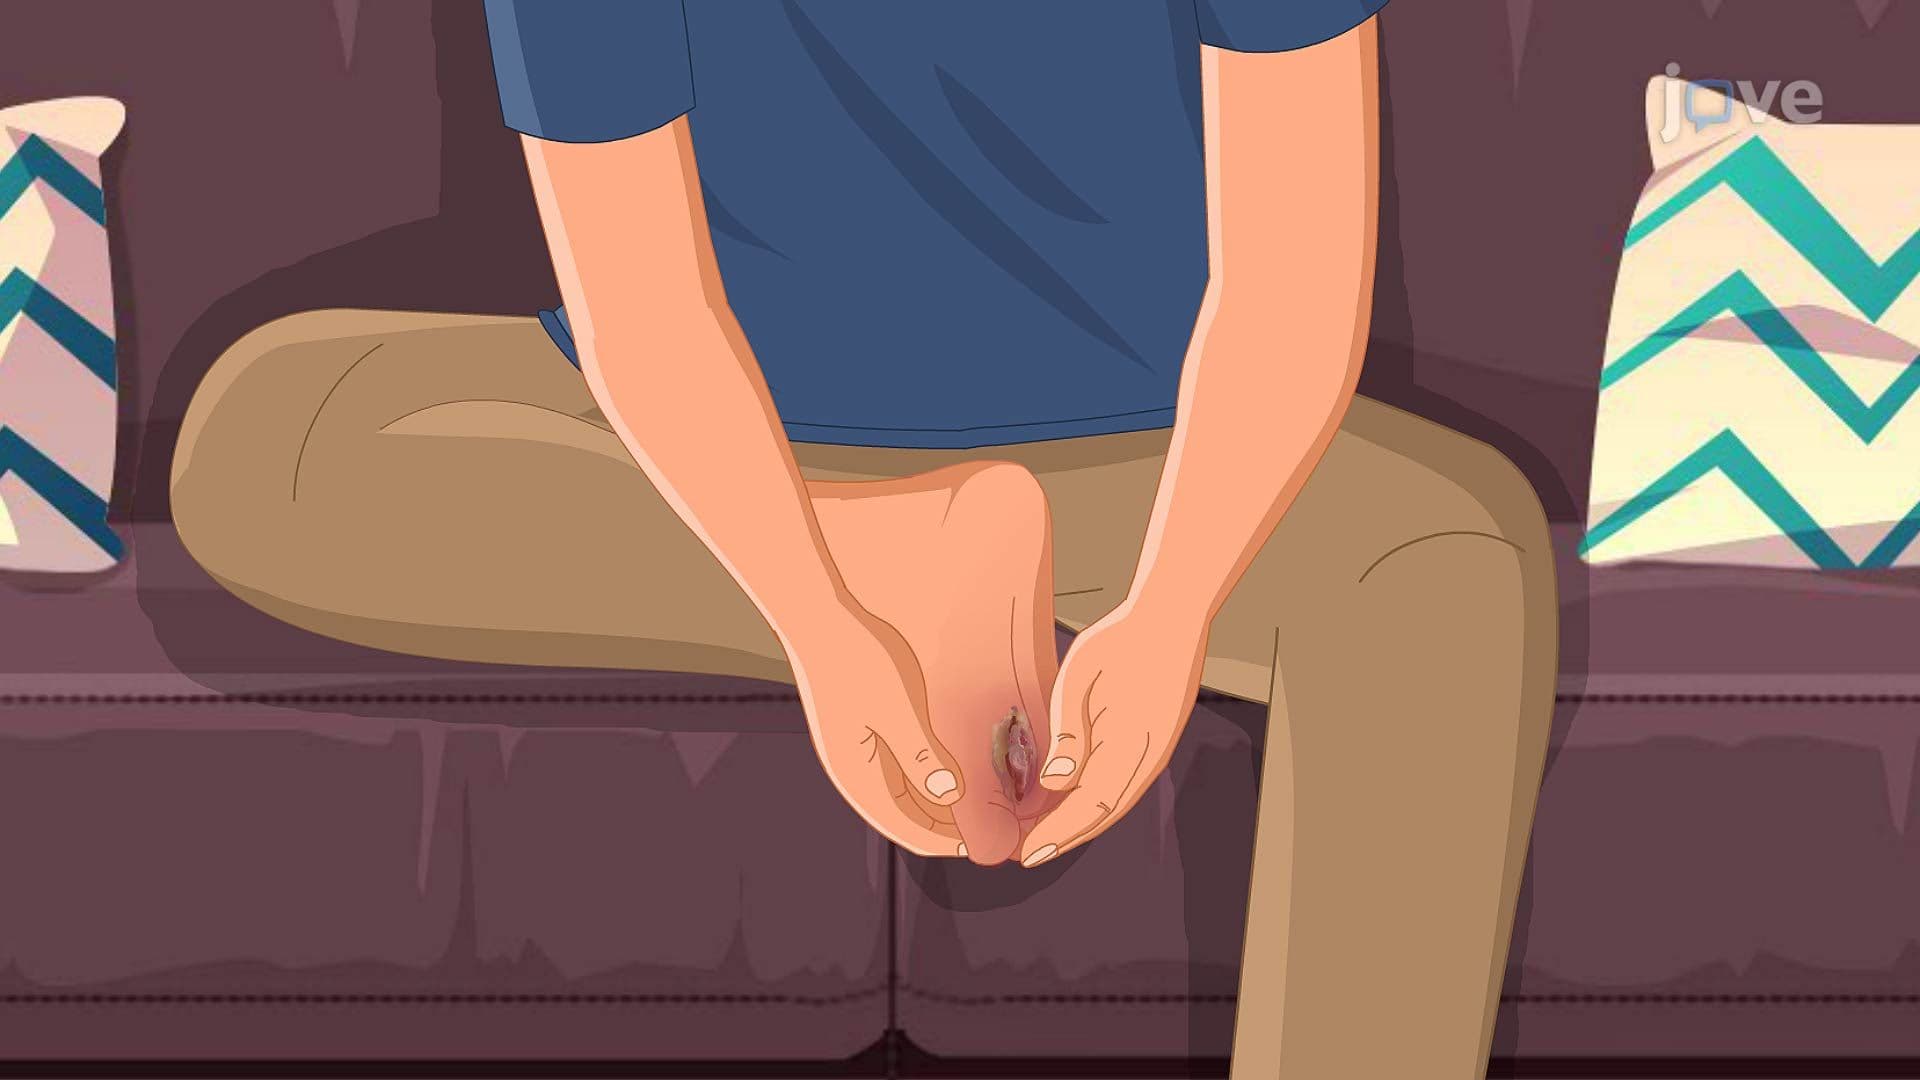
- Pressure ulcers most frequently occurred on the lower extremities, especially the feet, with sacral ulcers noted in older children and wheelchair users.
Conclusions:
- Pressure ulcers in children are often associated with underlying conditions like myelodysplasia and specific risk factors.
- The home environment is the predominant setting for pressure ulcer development in pediatric patients.
- Targeted interventions addressing identified risk factors and common ulcer locations are needed for prevention.
Abstract:
A retrospective, exploratory study was conducted as part of a performance improvement project examining pressure ulcer development in children. In 1 year, 69 children visited the hospital's wound clinic: 50 children had pressure ulcers, and 19 children had skin breakdown secondary to delayed operative wound healing. This article reviews findings from the 50 children with pressure ulcers. The primary diagnosis was myelodysplasia. Risk factors identified included (a) paralysis, (b) insensate areas, (c) high activity, and (d) immobility. The majority of the pressure ulcers occurred in the lower extremities, primarily the feet. As children get older or neurological condition deteriorates, sacral ulcers are seen particularly among wheelchair users. Pressure ulcers occur predominantly in the child's home environment.
Related Concept Videos
 01:27
Peptic Ulcer
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:25
Peptic Ulcer Disease I: Introduction
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds to M3...
 01:31
Diabetic Foot Ulcer
 01:24
Peptic Ulcer Disease II: Pathophysiology