Related Experiment Video
Updated: Aug 14, 2026

Sodium Taurocholate Induced Severe Acute Pancreatitis in C57BL/6 Mice
Published on: June 28, 2021
Infections complicating severe pancreatitis
1Section of General Surgery, Virginia Mason Medical Center, Seattle, Washington.

Abstract:
Infections accompanying severe pancreatitis are secondary and of three types: infected pancreatic necrosis, infected pseudocyst (including peripancreatic fluid collection), and pancreatic abscess. The first is an earlier, more morbid process, with antibiotics supportive and surgical debridement necessary. The latter two processes occur later in the course of pancreatitis and are less morbid. Antibiotics are supportive and invasive-nonsurgical drainage methods are possible. The decision for intervention is based first on clinical toxicity as determined by an overall assessment by the clinician. The presence of parenchymal necrosis is best determined by the dynamic bolus CT scan. The presence of infection is best determined by percutaneous CT-guided aspiration. Infected necrosis is fatal unless treated with operative intervention. A peripancreatic fluid collection, pseudocyst, or pancreatic abscess needs to be treated if symptomatic. If infected, as determined by CT-guided needle aspiration, then they should be drained. Radiologic or endoscopic invasive-nonsurgical methods are tried initially and then surgery is attempted if they fail. The nonsurgical methods are most successful with pancreatitis of a nonbiliary or a nonalcohol etiology.
Insights
Severe pancreatitis infections, including infected necrosis, pseudocysts, and abscesses, require timely intervention. Infected necrosis demands surgery, while other infections may be managed with drainage, prioritizing non-surgical methods for better outcomes.
Area of Science:
- Gastroenterology
- Infectious Diseases
- Radiology
Background:
- Severe pancreatitis can lead to secondary infections, categorized into infected pancreatic necrosis, infected pseudocyst, and pancreatic abscess.
- Infected pancreatic necrosis is a highly morbid condition requiring prompt intervention.
- Infected pseudocysts and pancreatic abscesses typically occur later and are less morbid, with less invasive treatment options.
Purpose of the Study:
- To outline the classification and management strategies for secondary infections in severe pancreatitis.
- To differentiate the treatment approaches based on the type of infection and clinical presentation.
- To emphasize the diagnostic modalities and intervention thresholds for these complications.
Main Methods:
- Clinical assessment of patient toxicity guides intervention decisions.
- Dynamic bolus CT scans are utilized to determine the presence of parenchymal necrosis.
- Percutaneous CT-guided aspiration is the gold standard for diagnosing infection.
Main Results:
- Infected pancreatic necrosis is fatal without operative intervention.
- Symptomatic pseudocysts or abscesses require drainage, with a preference for initial non-surgical methods (radiologic or endoscopic).
- Non-surgical drainage methods show higher success rates in pancreatitis cases without biliary or alcohol etiology.
Conclusions:
- Effective management of secondary infections in severe pancreatitis hinges on accurate diagnosis and appropriate intervention timing.
- Distinguishing between infected necrosis and other infected fluid collections is critical for treatment selection.
- Non-surgical drainage is a viable and often preferred initial approach for infected pseudocysts and abscesses, particularly in non-biliary/non-alcohol pancreatitis.


Related Concept Videos
 01:27
Acute Pancreatitis I: Introduction
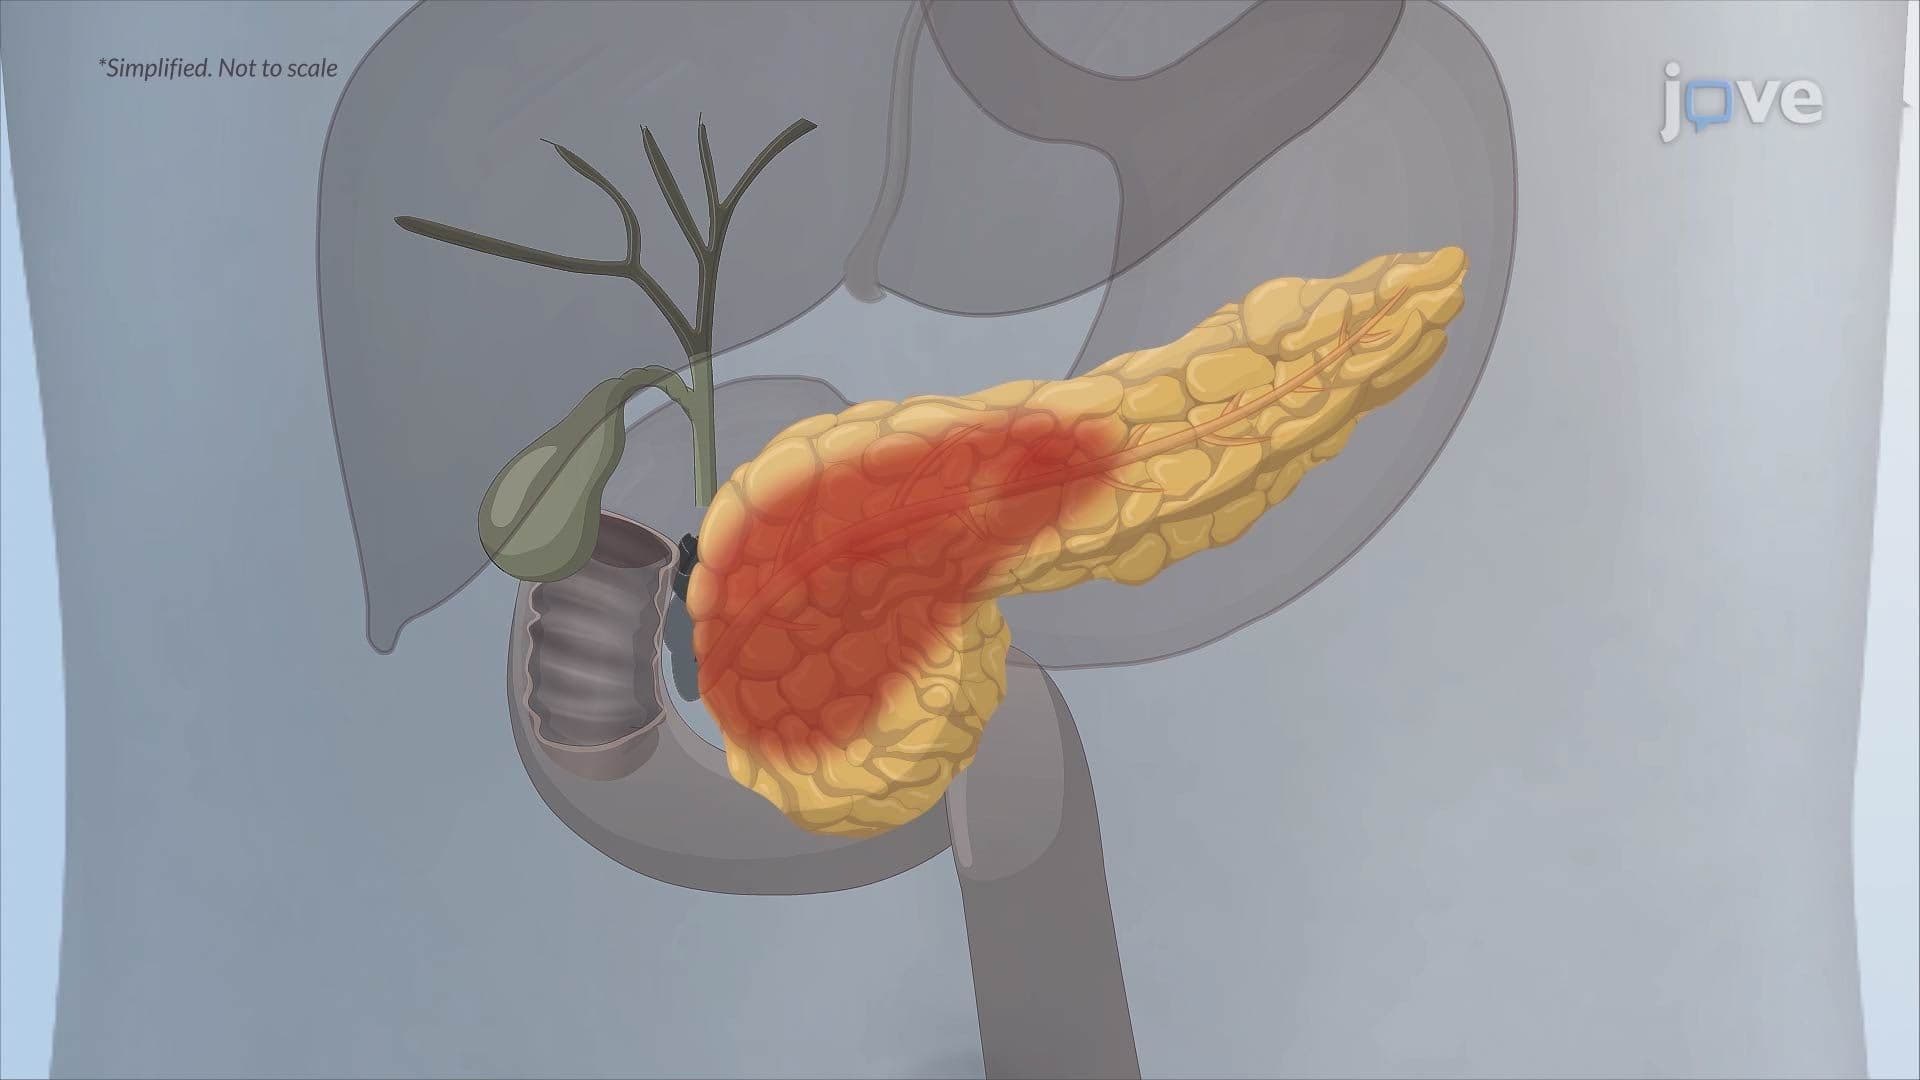
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:25
Acute Pancreatitis I: Introduction
 01:21
Acute Pancreatitis II: Pathophysiology
 01:25
Chronic Pancreatitis I: Introduction
 01:21
Chronic Pancreatitis II: Pathophysiology