Related Experiment Video
Updated: Aug 31, 2026

Measurement of Factor V Activity in Human Plasma Using a Microplate Coagulation Assay
Published on: September 9, 2012
Increased soluble fibrin in plasma of patients with disseminated intravascular coagulation
Hideo Wada1, Tomohiro Sase, Takeshi Matsumoto
1Department of Laboratory Medicine, Mie University School of Medicine, Tsu-city, Mie-ken, Japan. wadahide@cli.medic.mie-u.ac.jp

Plasma levels of soluble fibrin (SF) were measured in 1184 patients with disseminated intravascular coagulation (DIC) according to Japanese Ministry of Health and Welfare (JMHW) criteria. The usefulness of SF for the diagnosis of DIC was compared with other hemostatic molecular markers. Most hemostatic markers were significantly increased in patients with DIC than in those without DIC. Plasma levels of fibrin and fibrinogen degradation products, thrombin-antihtrombin complex, plasmin-plasmin inhibitor complex, D-dimer, thrombomodulin, and SF levels were also significantly higher in those with pre-DIC than in those without DIC. In classification of overt DIC by International Society of Thrombosis and Haemostasis (ISTH) criteria, most hemostatic markers were significantly increased in patients with overt DIC than in those without overt DIC. Plasma levels of SF 'in patients with DIC were significantly higher than those in patients with pre-DIC, which were significantly higher than in those without DIC. Plasma levels of SF were also significantly higher in patients with overt DIC than in those with non-overt DIC. The correlation between plasma SF levels and DIC score according to JMHW criteria or ISTH criteria was good. Receiver operating characteristic analysis shows that SF was the best marker for the diagnosis of DIC or overt DIC. These findings suggest that plasma SF might be useful marker for the diagnosis of DIC or overt DIC.
Plasma levels of soluble fibrin (SF) were measured in 1184 patients with disseminated intravascular coagulation (DIC) according to Japanese Ministry of Health and Welfare (JMHW) criteria. The usefulness of SF for the diagnosis of DIC was compared with other hemostatic molecular markers. Most hemostatic markers were significantly increased in patients with DIC than in those without DIC. Plasma levels of fibrin and fibrinogen degradation products, thrombin-antihtrombin complex, plasmin-plasmin inhibitor complex, D-dimer, thrombomodulin, and SF levels were also significantly higher in those with pre-DIC than in those without DIC. In classification of overt DIC by International Society of Thrombosis and Haemostasis (ISTH) criteria, most hemostatic markers were significantly increased in patients with overt DIC than in those without overt DIC. Plasma levels of SF 'in patients with DIC were significantly higher than those in patients with pre-DIC, which were significantly higher than in those without DIC. Plasma levels of SF were also significantly higher in patients with overt DIC than in those with non-overt DIC. The correlation between plasma SF levels and DIC score according to JMHW criteria or ISTH criteria was good. Receiver operating characteristic analysis shows that SF was the best marker for the diagnosis of DIC or overt DIC. These findings suggest that plasma SF might be useful marker for the diagnosis of DIC or overt DIC.
More Related Videos


Related Concept Videos
 01:16
Clot Retraction and Fibrinolysis
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:30
Venous Thrombosis I: Introduction
 01:22
Formation of the Platelet Plug
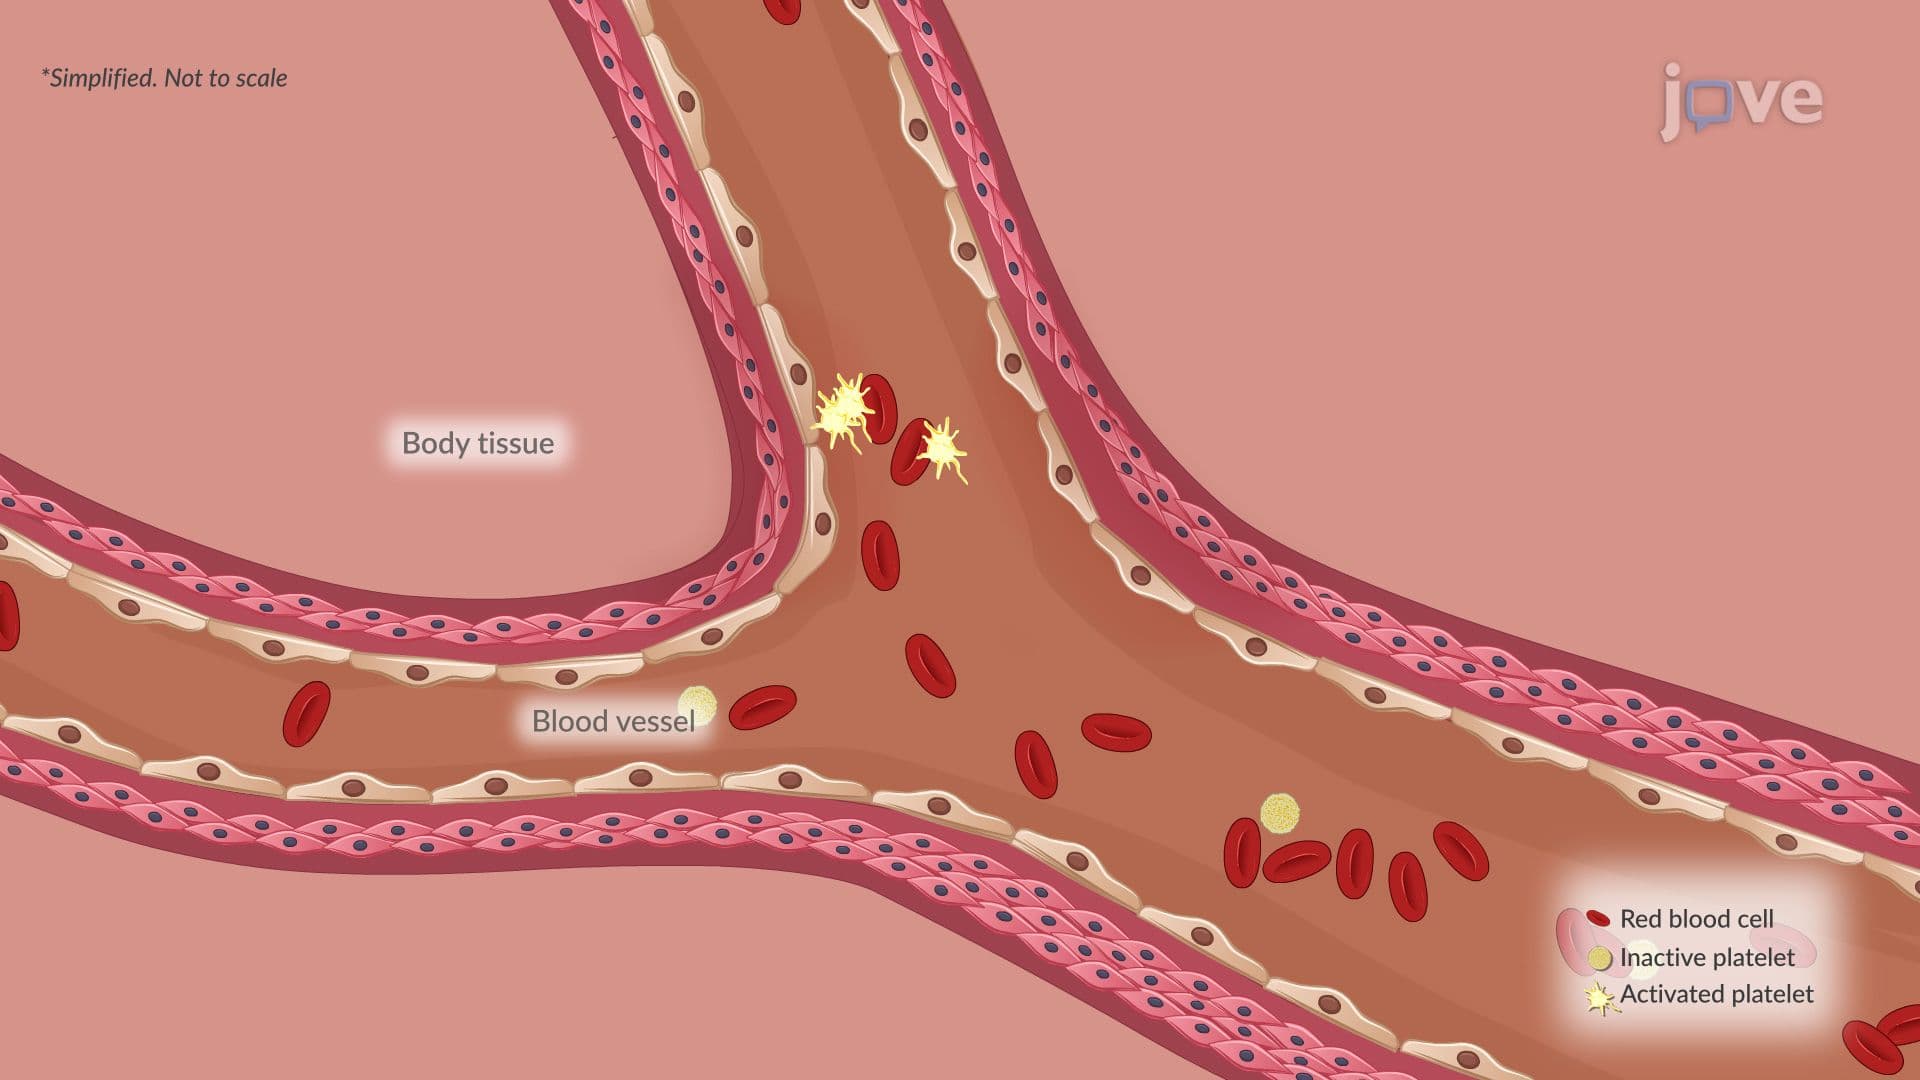
As the injured blood vessel contracts, endothelial cells undergo contraction, revealing collagen fibers in the basement membrane and underlying connective tissue. Furthermore, the plasma membrane of endothelial cells becomes adhesive, preparing the site for platelet adhesion. Platelets...
 01:25
Acute Inflammation III: Local and Systemic Effects