Related Experiment Video
Updated: Aug 30, 2026


Autoradiography as a Simple and Powerful Method for Visualization and Characterization of Pharmacological Targets
Published on: March 12, 2019
Ion-trapping, microsomal binding, and unbound drug distribution in the hepatic retention of basic drugs
Gerhard A Siebert1, Daniel Y Hung, Ping Chang
1Department of Medicine, University of Queensland, Princess Alexandra Hospital, Woolloongabba, Queensland, Australia.

Abstract:
This study investigated the relative contribution of ion-trapping, microsomal binding, and distribution of unbound drug as determinants in the hepatic retention of basic drugs in the isolated perfused rat liver. The ionophore monensin was used to abolish the vesicular proton gradient and thus allow an estimation of ion-trapping by acidic hepatic vesicles of cationic drugs. In vitro microsomal studies were used to independently estimate microsomal binding and metabolism. Hepatic vesicular ion-trapping, intrinsic elimination clearance, permeability-surface area product, and intracellular binding were derived using a physiologically based pharmacokinetic model. Modeling showed that the ion-trapping was significantly lower after monensin treatment for atenolol and propranolol, but not for antipyrine. However, no changes induced by monensin treatment were observed in intrinsic clearance, permeability, or binding for the three model drugs. Monensin did not affect binding or metabolic activity in vitro for the drugs. The observed ion-trapping was similar to theoretical values estimated using the pHs and fractional volumes of the acidic vesicles and the pKa values of drugs. Lipophilicity and pKa determined hepatic drug retention: a drug with low pKa and low lipophilicity (e.g., antipyrine) distributes as unbound drug, a drug with high pKa and low lipophilicity (e.g., atenolol) by ion-trapping, and a drug with a high pKa and high lipophilicity (e.g., propranolol) is retained by ion-trapping and intracellular binding. In conclusion, monensin inhibits the ion-trapping of high pKa basic drugs, leading to a reduction in hepatic retention but with no effect on hepatic drug extraction.

Related Concept Videos
 01:29
Drug Distribution: Plasma Protein Binding
 01:21
Drug Distribution: Tissue Binding
For...
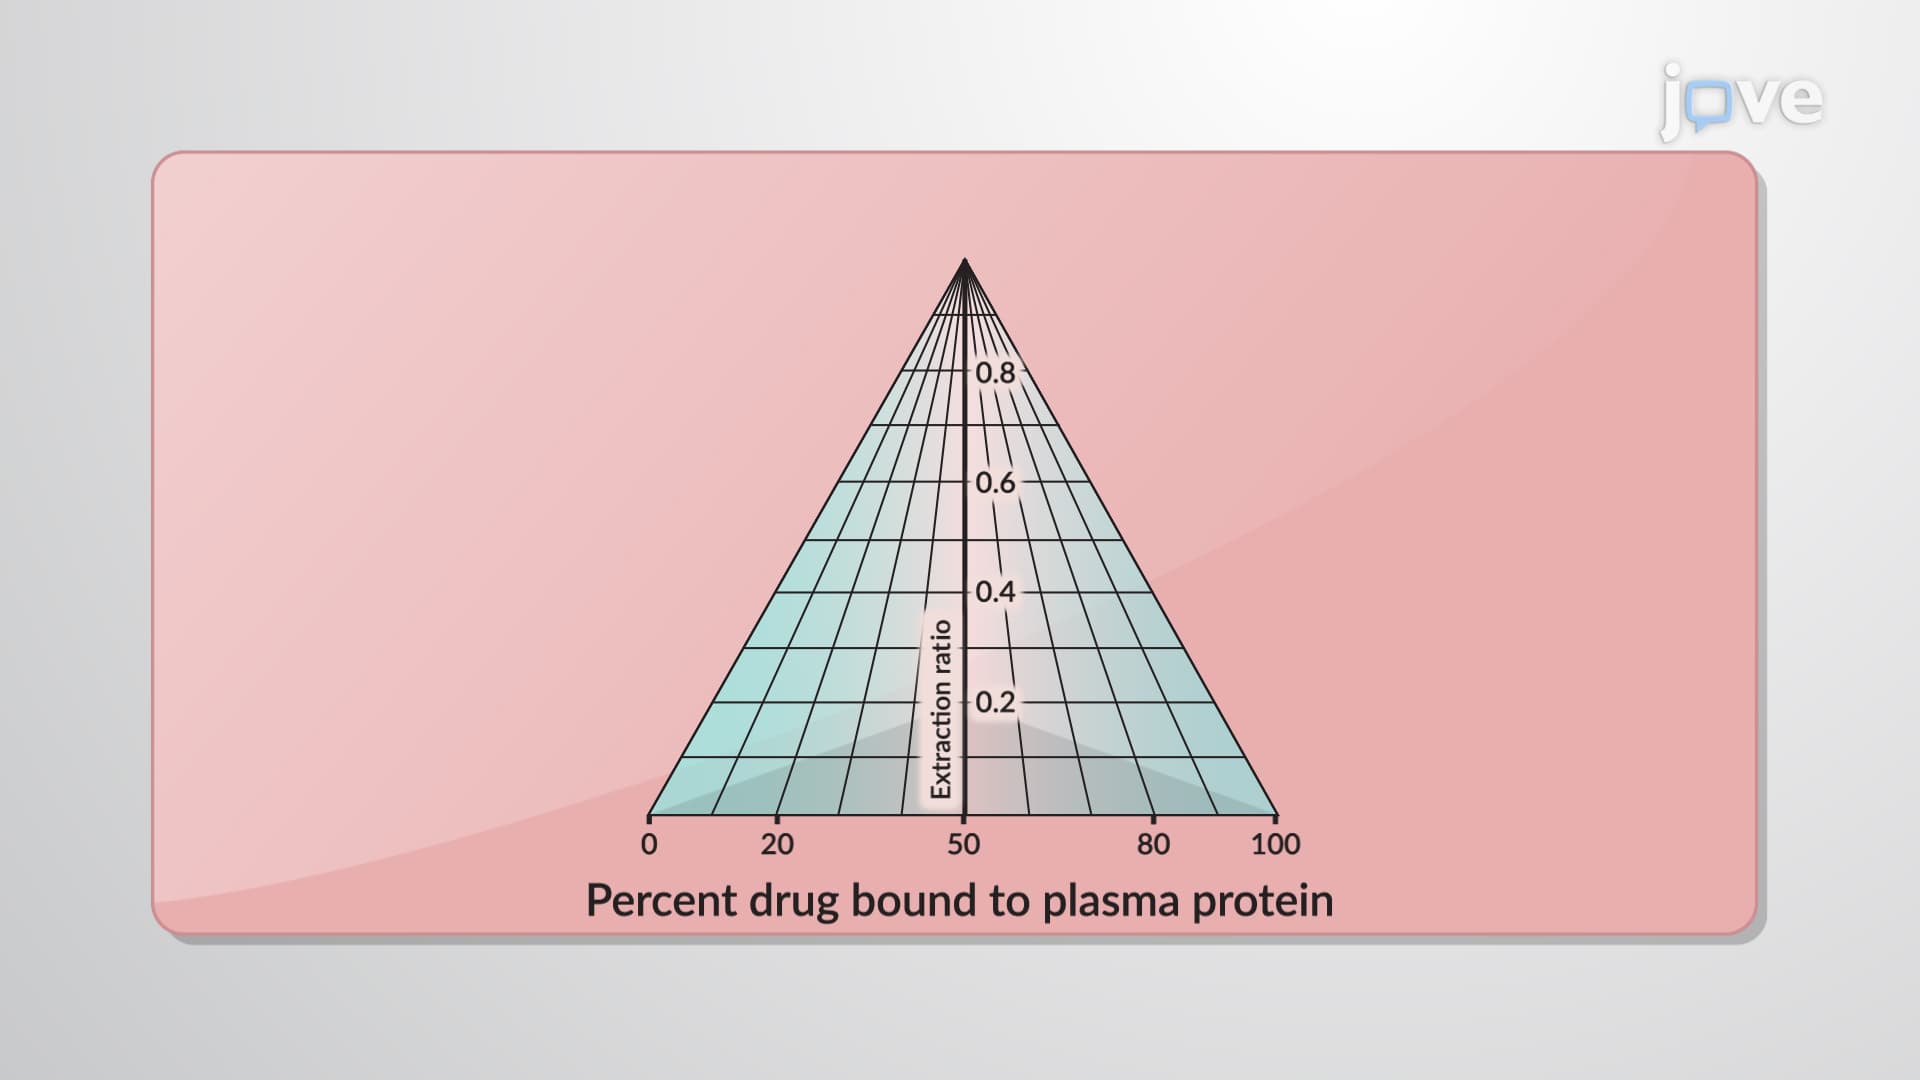 01:09
Hepatic Drug Clearance: Effect of Protein Binding
For low-extraction-ratio drugs that are less than 80% protein-bound, minor changes in protein binding...
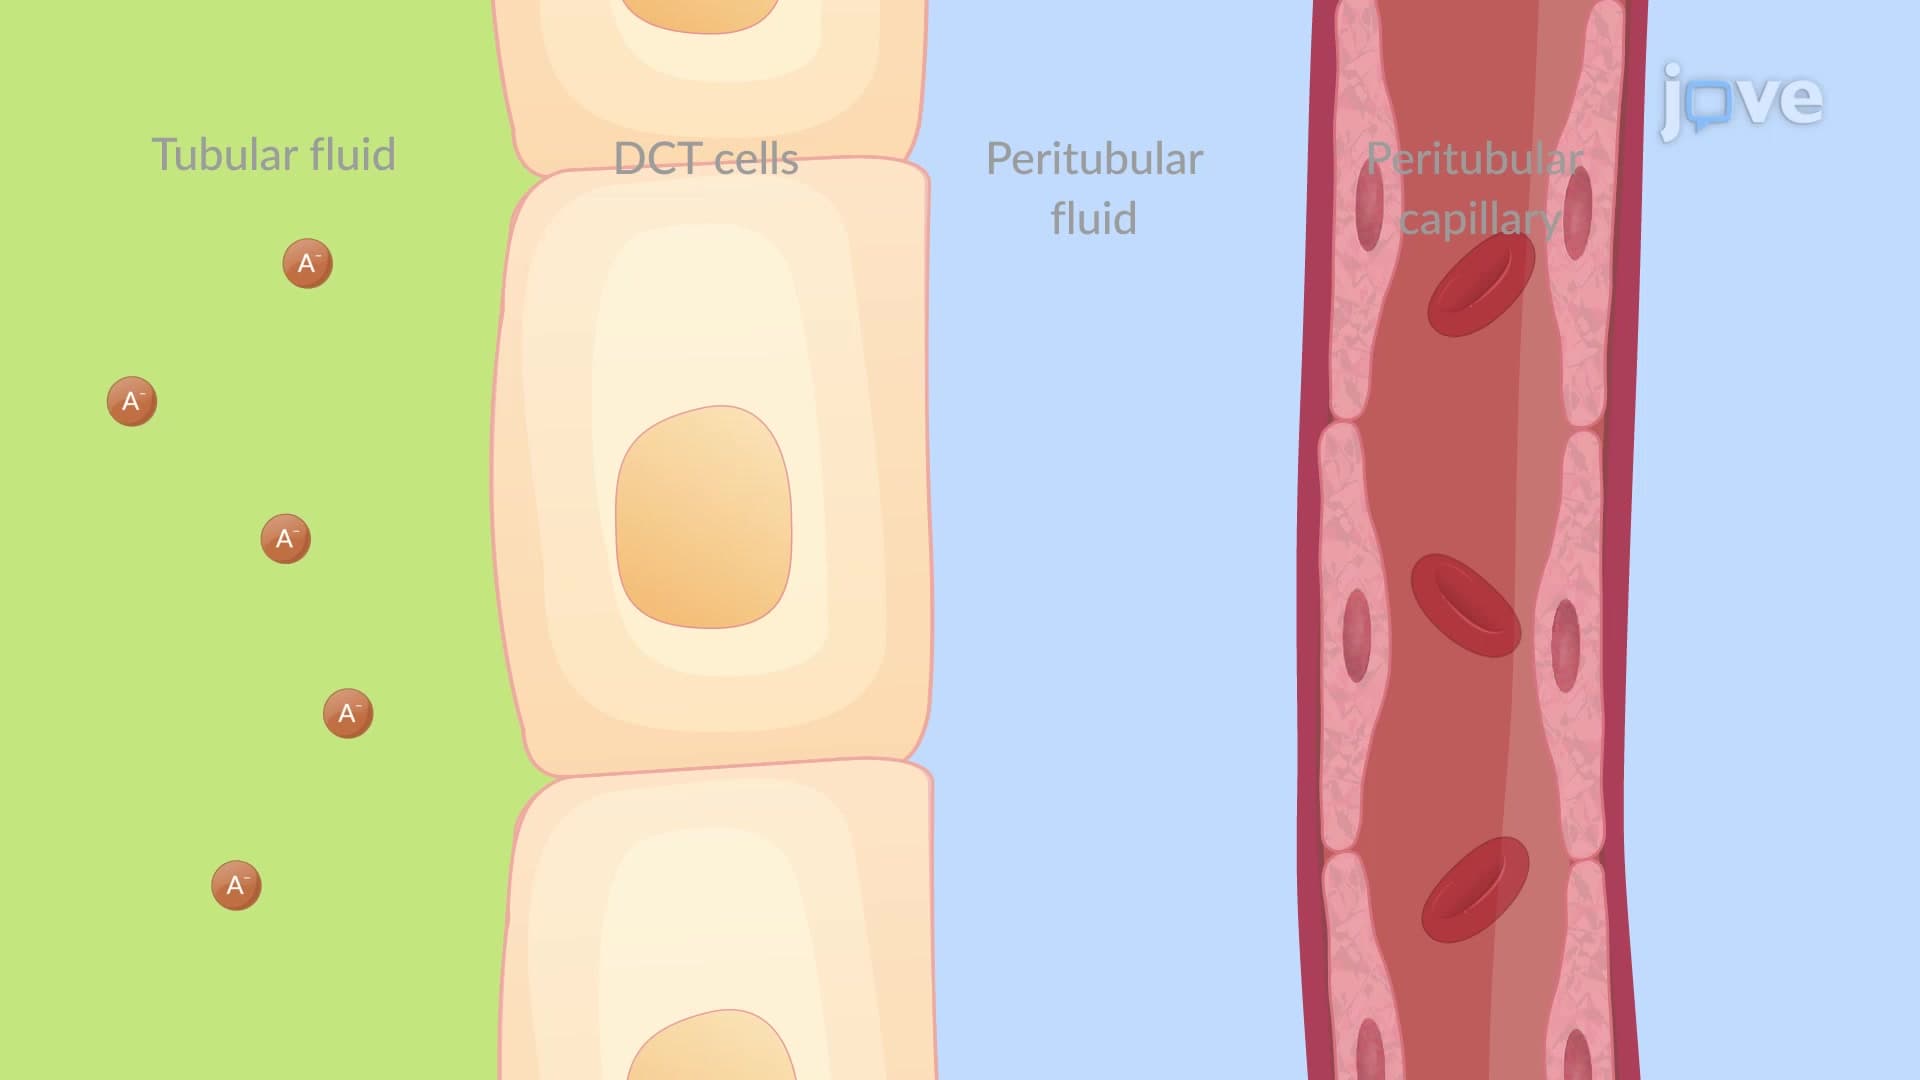 01:22
Drug Elimination by Renal Route: Tubular Reabsorption
 01:23
Drug Absorption Mechanism: Passive Membrane Transport
 01:07
Physiological Pharmacokinetic Models: Incorporating Hepatic Transporter-Mediated Clearance
A recent model describes pravastatin's hepatobiliary excretion, mediated...