Related Experiment Video
Updated: Aug 30, 2026


Endoscopic Endonasal Trans-sphenoidal Approach: Minimally Invasive Surgery for Pituitary Adenomas
Published on: January 17, 2018
Recent advances in diagnosis and treatment of pheochromocytoma
F Veglio1, F Morello, S Morra Di Cella
1Hypertension Unit, Department of Medicine and Experimental Oncology, S. Vito Hospital, University of Turin, Turin, Italy. centroiperten.torino@libero.it

Abstract:
Pheochromocytomas are rare tumours of catecholamine-producing chromaffin cells leading to hypertension and symptoms of catecholamine excess. They can be benign or malignant, sporadic or familial tumours. Genetic syndromes associated with pheochromocytoma are MEN II, VHL disease and neurofibromatosis type 1. Usually, pheochromocytomas occur in the adrenal medulla. Clinical manifestations include hypertension (which can be intermittent, stable or in the form of hypertensive peaks) and symptoms related to catecholamine excess such as headache, palpitations and tachycardia, pallor, anxiety and nervousness, nausea, vomiting, weight loss. This clinical syndrome can be mimicked by various hyperkinetic and hyperadrenergic states. When pheochromocytoma is suspected, the first diagnostic step is represented by the measurement of catecholamines and their metabolites (metanephrines) in urine and plasma. Chro-mogranin A measurement can be useful. The clonidine suppression test may be helpful in ruling out other conditions that may elevate catecholamines and metanephrines. Localiza-tion and staging of pheochromocytoma is based on MRI, which is more sensitive than CT scan, and (131)I-MIBG scintiscan. The best therapeutic option for pheochromocytoma is surgery with a laparoscopic approach. An appropriate pre-, intra- and postoperative medical management of the patient is mandatory. In the absence of optimal medical treatment, intraoperative mortality reaches 50%.
Related Concept Videos
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...
 01:27
Transducer Mechanism: Enzyme-Linked Receptors
Major types that are helpful drug targets include:
 02:57
Targeted Cancer Therapies
There are several types of targeted therapies against specific...
 01:26
Treatment for Pulmonary Arterial Hypertension: Receptor Tyrosine Kinase Inhibitors and Calcium Channel Blockers
TKIs, such as imatinib (Gleevec), are particularly effective in tackling the growth and mitogenic factors that become upregulated in PAH patients. These factors contribute to the...
 01:22
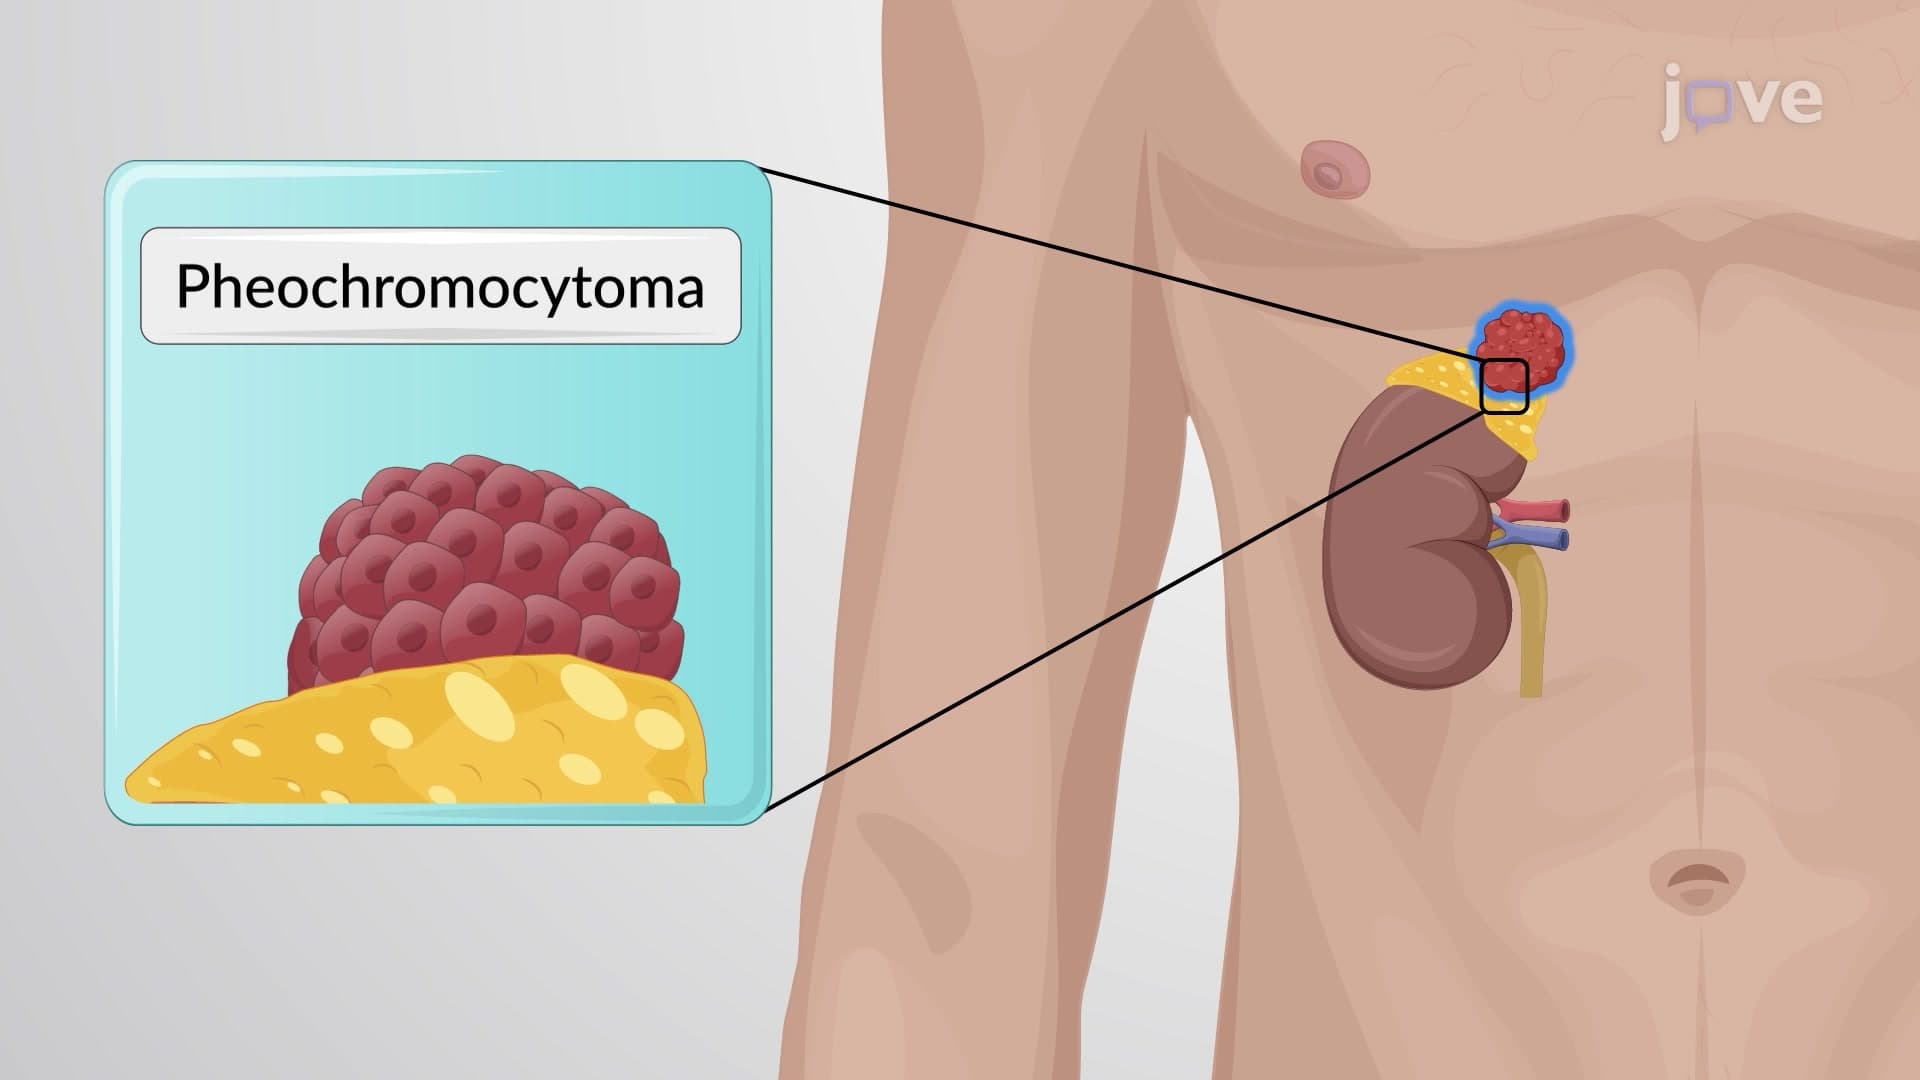
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:30
Adrenergic Agonists: Direct-Acting Agents
These agents can be classified...