Related Experiment Video
Updated: Aug 30, 2026


Preparing a Mice Model of Severe Acute Pancreatitis via a Combination of Caerulein and Lipopolysaccharide Intraperitoneal Injection
Published on: May 10, 2024
Early prediction of severe acute pancreatitis by urinary trypsinogen activation peptide
Zhi-Su Liu1, Cong-Qing Jiang, Qun Qian
1Department of General Surgery, Zhongnan Hospital, Wuhan University, Wuhan 430071, China. chqjiang@hotmail.com

Objective:
To investigate the value of urinary trypsinogen activation peptide (TAP) in the early prediction of severe acute pancreatitis and to compare it with acute physiology and chronic health evaluation II (APACHE II).
Methods:
We assessed the predictive value of urinary TAP concentrations measured by a competitive enzyme-linked immunosorbent assay. Urine samples were collected for detecting TAP concentrations at admission, and 24, 48, and 72 h from 41 patients with acute pancreatitis (12 with severe disease, 29 with mild disease) who presented within 48 h the onset of symptoms and from 11 control patients, while APACHE II scores were recorded at 48 h after admission.
Results:
The peak median urinary TAP concentration was seen at admission. The median urinary TAP concentration at admission for severe pancreatitis (95 nmol/L) was significantly higher than the median for patients with mild pancreatitis (20 nmol/L, P<0.005) and controls (15 nmol/L, P<0.005). TAP concentrations were significantly higher in patients with severe acute pancreatitis than the median in patients with mild pancreatitis (P<0.05) and controls (P<0.05) on days 2 to 3. The median APACHE II scores of severe patients were significantly different from those of mild patients (10.5 vs 6.0, P<0.01). The sensitivity, specificity, positive predictive, and negative predictive values of an admission urinary TAP>/=35 nmol/L for severe pancreatitis were 91.7%, 89.7%, 78.6% and 96.3%, whereas 48 h after admission the values for APACHE II scores (>/=9) were 75.0%, 72.7%, 52.9% and 87.5%. In prediction of disease severity, the urine TAP concentration was much better than APACHE II at 48 h.
Conclusions:
Urinary TAP obtained at the first 48 h of the onset of symptoms can predict severe acute pancreatitis. In prediction of disease severity, the urinary TAP is much better than APACHE II score.

Related Concept Videos
 01:21
Acute Pancreatitis II: Pathophysiology
 01:25
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
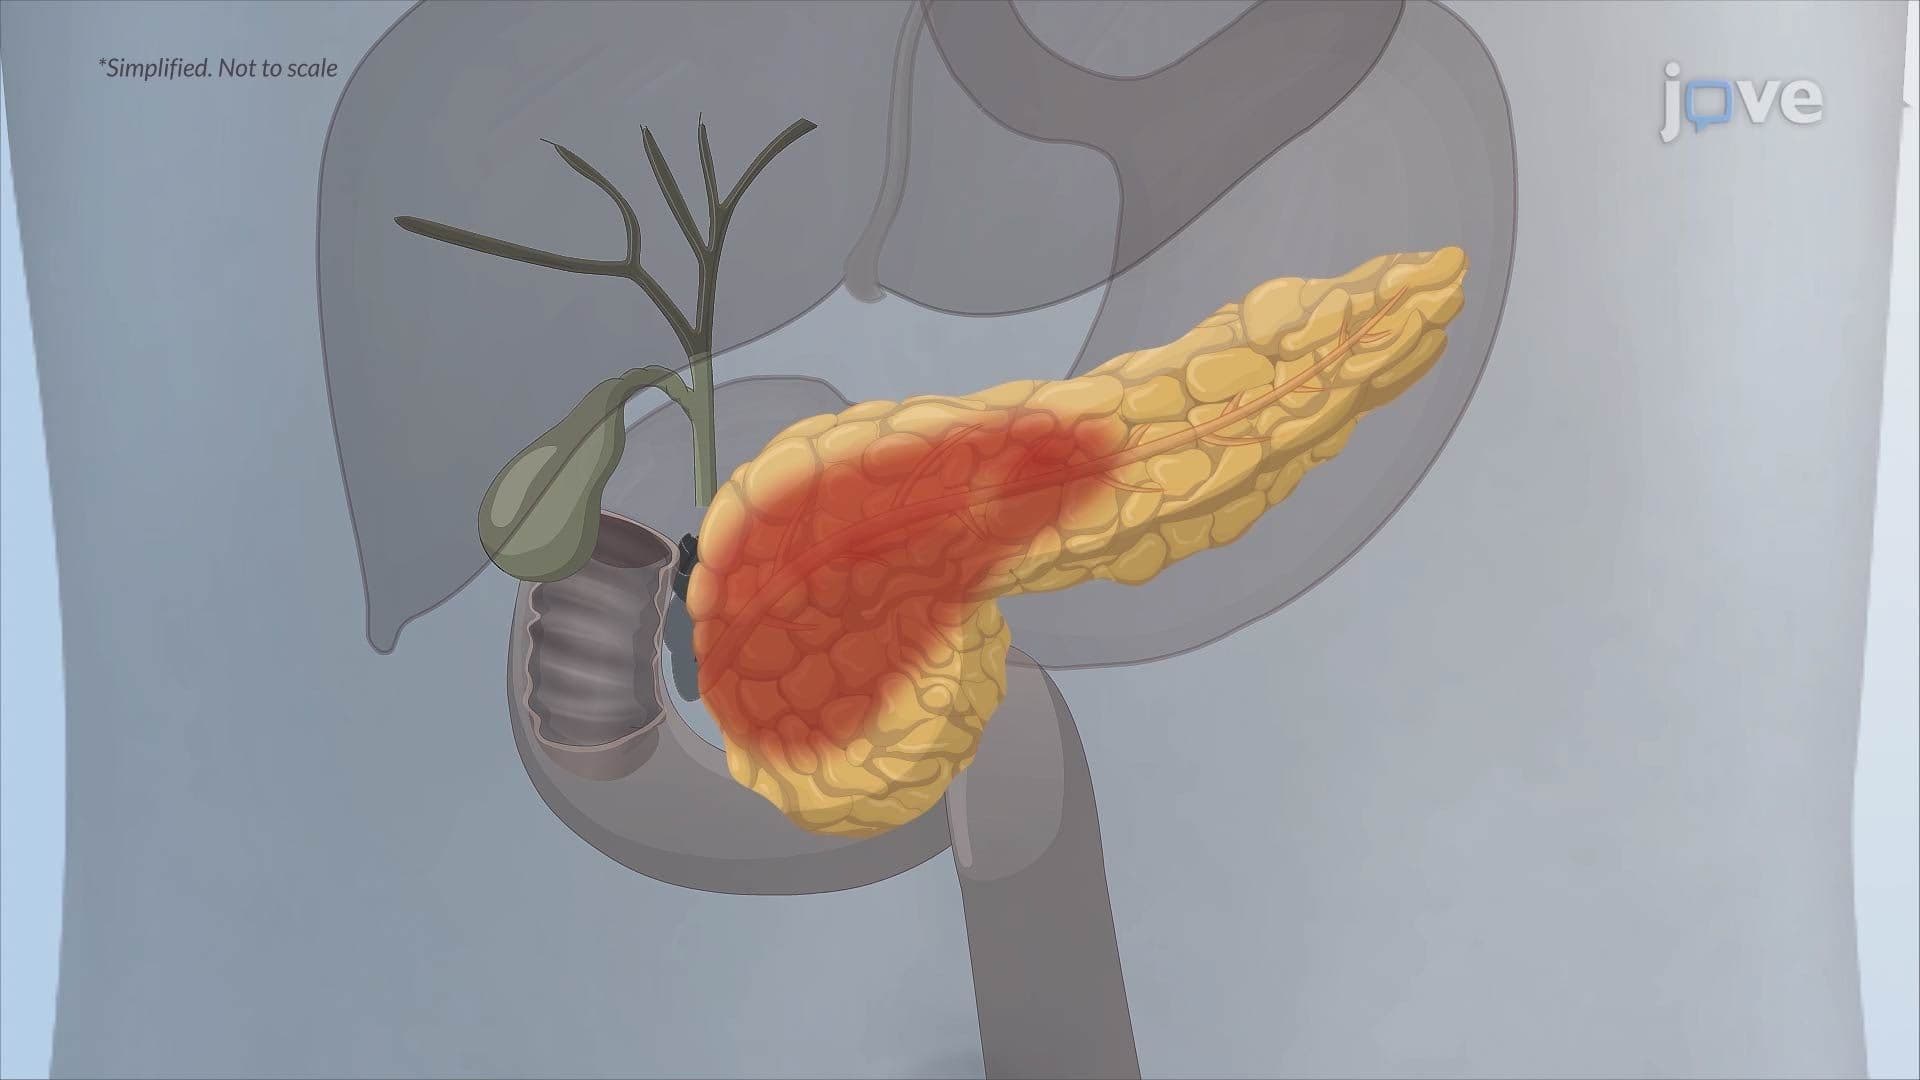
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:25
Chronic Pancreatitis I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...