Related Experiment Video
Updated: Aug 8, 2026


Anogenital Distance and Perineal Measurements of the Pelvic Organ Prolapse (POP) Quantification System
Published on: September 20, 2018
On the pathogenesis of rectocele: the concept of the rectovaginal pressure gradient
Ahmed Shafik1, Olfat El-Sibai, Ali A Shafik
1Department of Surgery and Experimental Research, Faculty of Medicine, Cairo University, 2 Talaat Harb Street, 11121 Cairo, Egypt. shafik@ahmed-shafik.org

Abstract:
Coughing or straining evokes reflex bulbocavernosus (BCM) and puborectalis (PRM) muscle contraction, which apparently transforms the vagina into a closed high-pressure cavity. This elevated vaginal pressure counteracts the increased intra-abdominal pressure and the tendency of the uterus to prolapse, and also supports the rectovaginal septum against the high straining-induced intrarectal pressure and possible consequent rectocele (posterior vaginal prolapse) formation. We investigated the hypothesis that a weak BCM and PRM share in the genesis of rectocele by changing the rectovaginal pressure gradient. Twenty-three women with rectocele (mean age 43.2+/-6.6 years) and 12 healthy women volunteers (mean age 41.6+/-6.2 years) were studied. The response of the intrarectal (intra-abdominal) and intravaginal pressure, as well as the EMG activity of the BCM and PRM to straining or coughing, was recorded. In the healthy volunteers the rectal and vaginal pressures showed a significant increase on coughing or straining, with no significant difference between the rectal or vaginal pressures. Also, the BCM and PRM EMG activity exhibited a significant increase. Rectocele patients showed a significantly low resting vaginal pressure. The increase in rectal and vaginal pressure, as well as of the EMG activity of the BCM and PRM on straining or coughing, was significantly lower and the latency of the EMG response was significantly longer than those of the healthy volunteers. A difference in the rectovaginal pressure gradient showing a significant increase in the rectal against the vaginal pressure, particularly on coughing or straining, is suggested to be the basic factor in the genesis of rectocele. This pressure difference appears to be caused by diminished BCM and PRM contractile activity. A disrupted rectovaginal septum is not a prerequisite for rectocele formation, as the septum appears normal in obstructed defecation despite the common occurrence of rectocele. A histopathologic study of the septum in rectocele seems necessary.


Related Concept Videos
 01:26
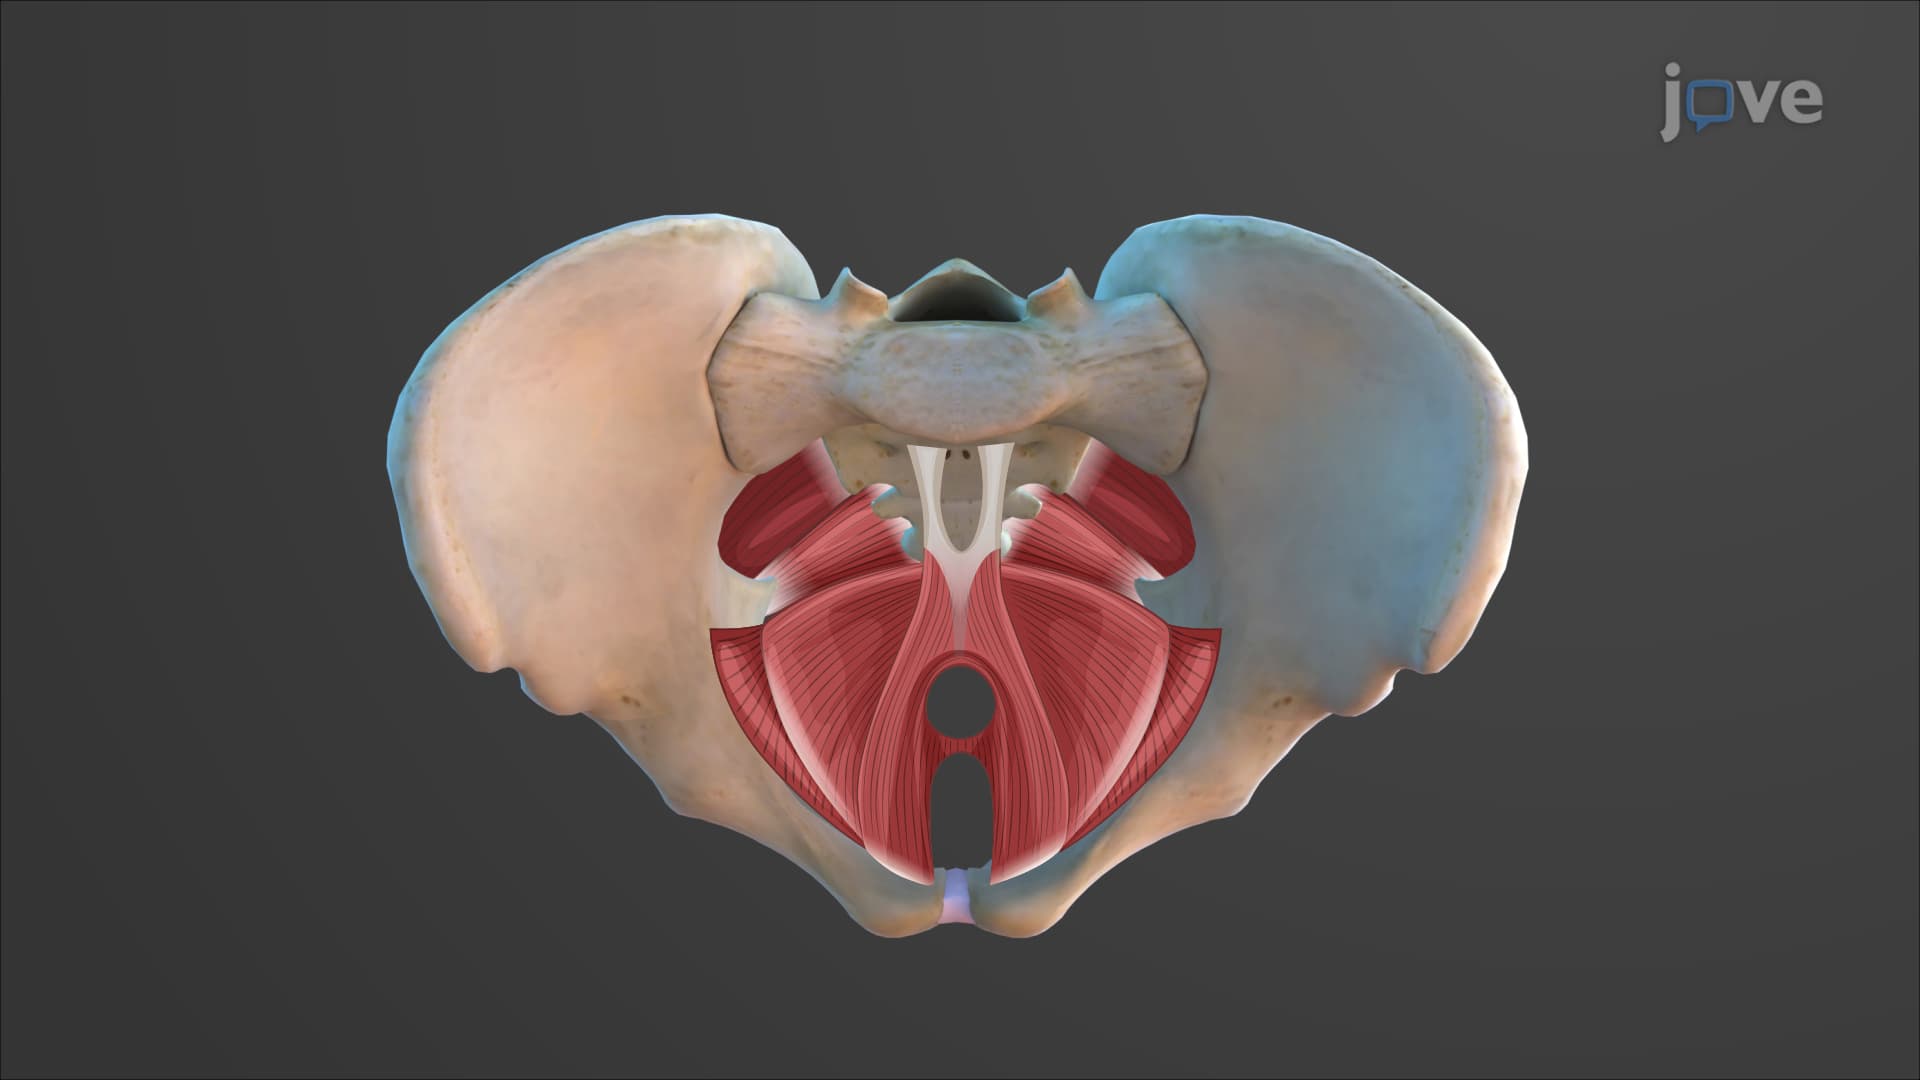
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:24
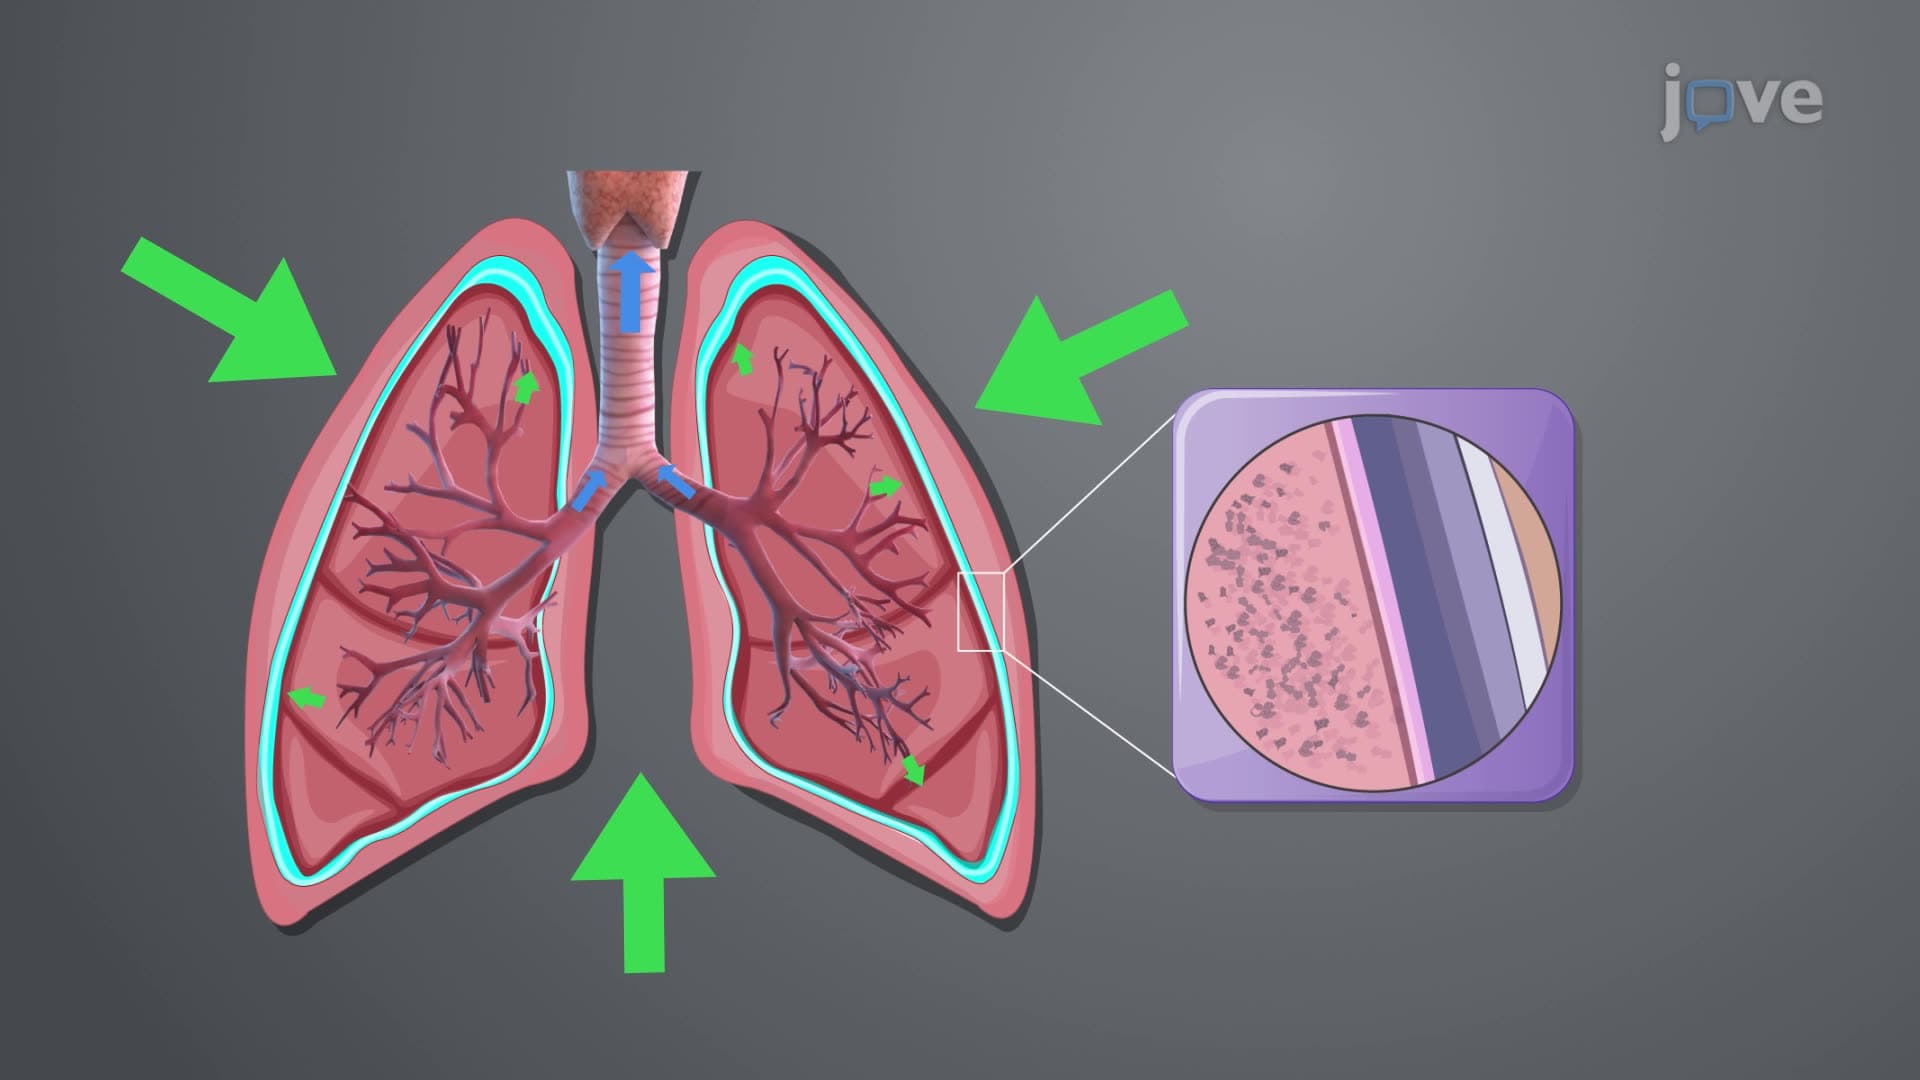
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs during...
 01:27
Mitral Valve Prolapse I: Introduction
 01:23
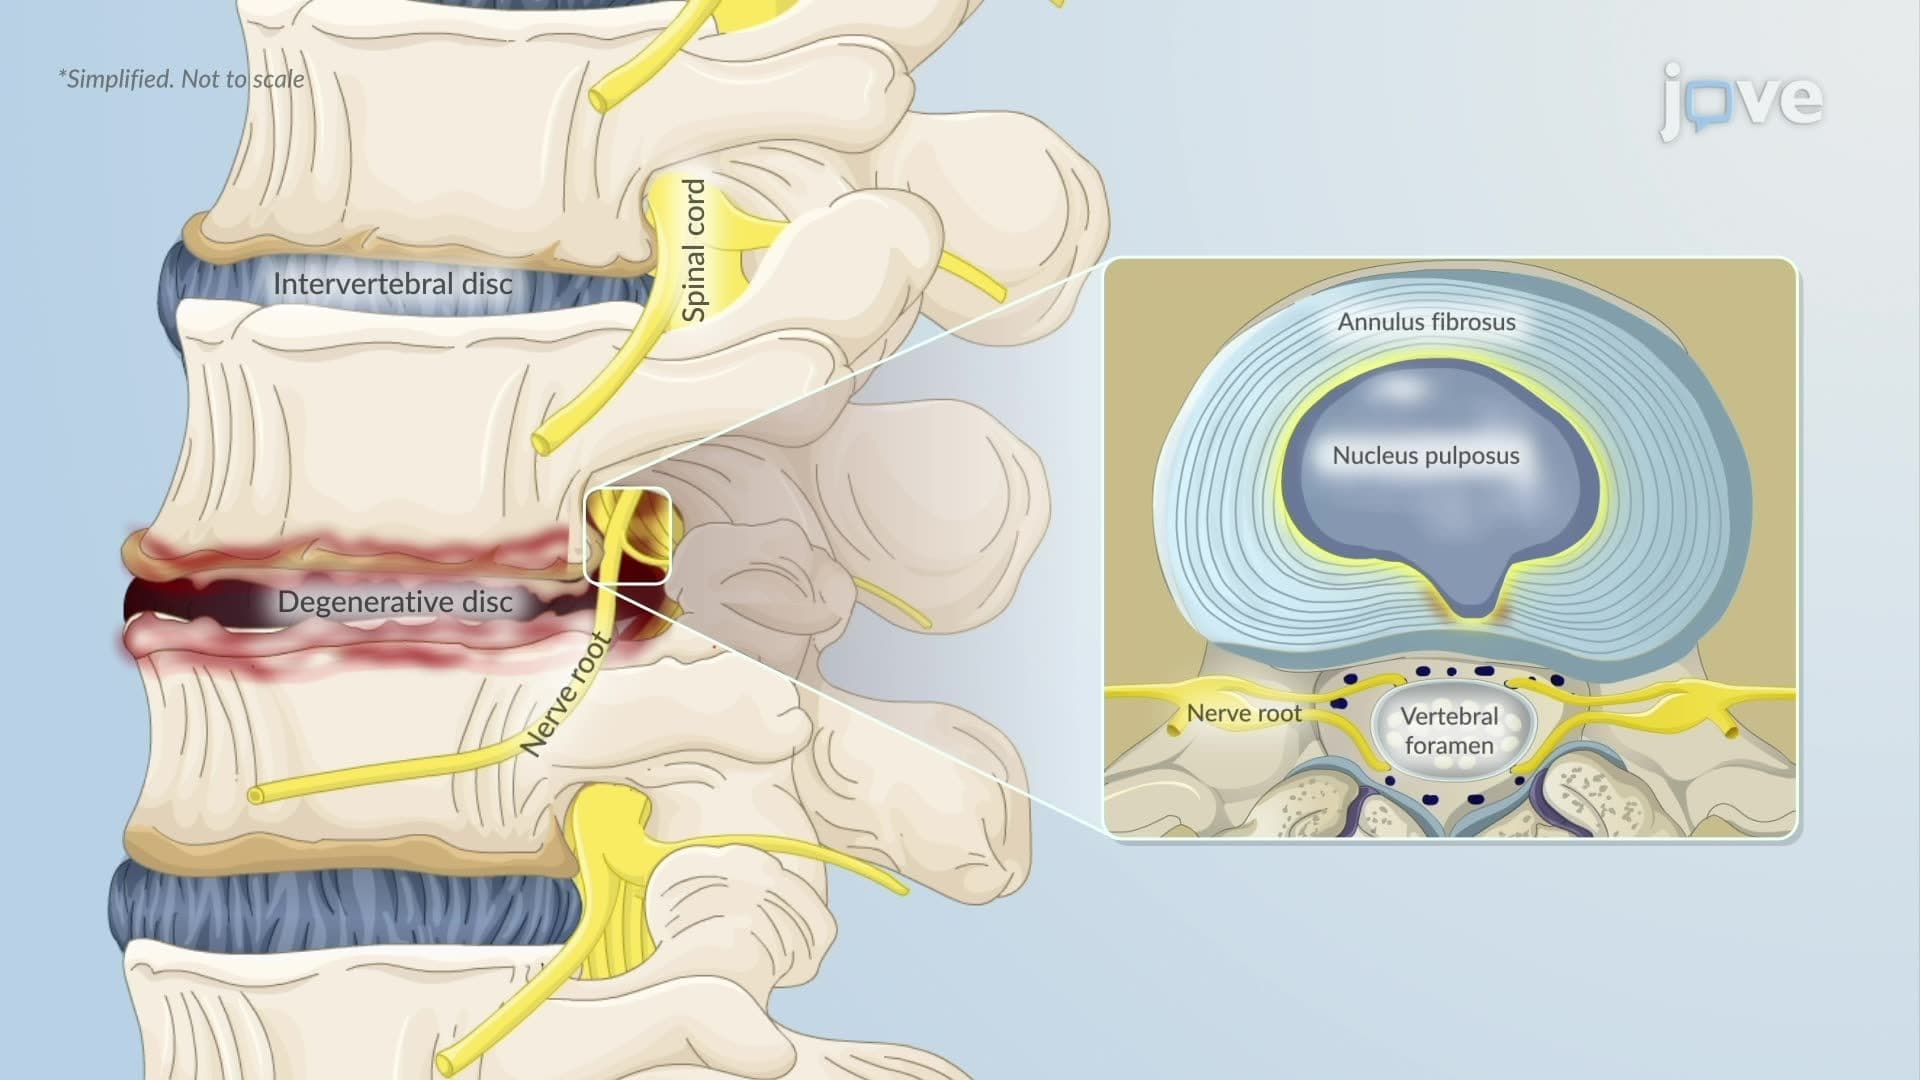
Degenerative Disc Disease ll: Pathophysiology
 01:07
Intestinal Obstruction II: Pathophysiology
 01:27
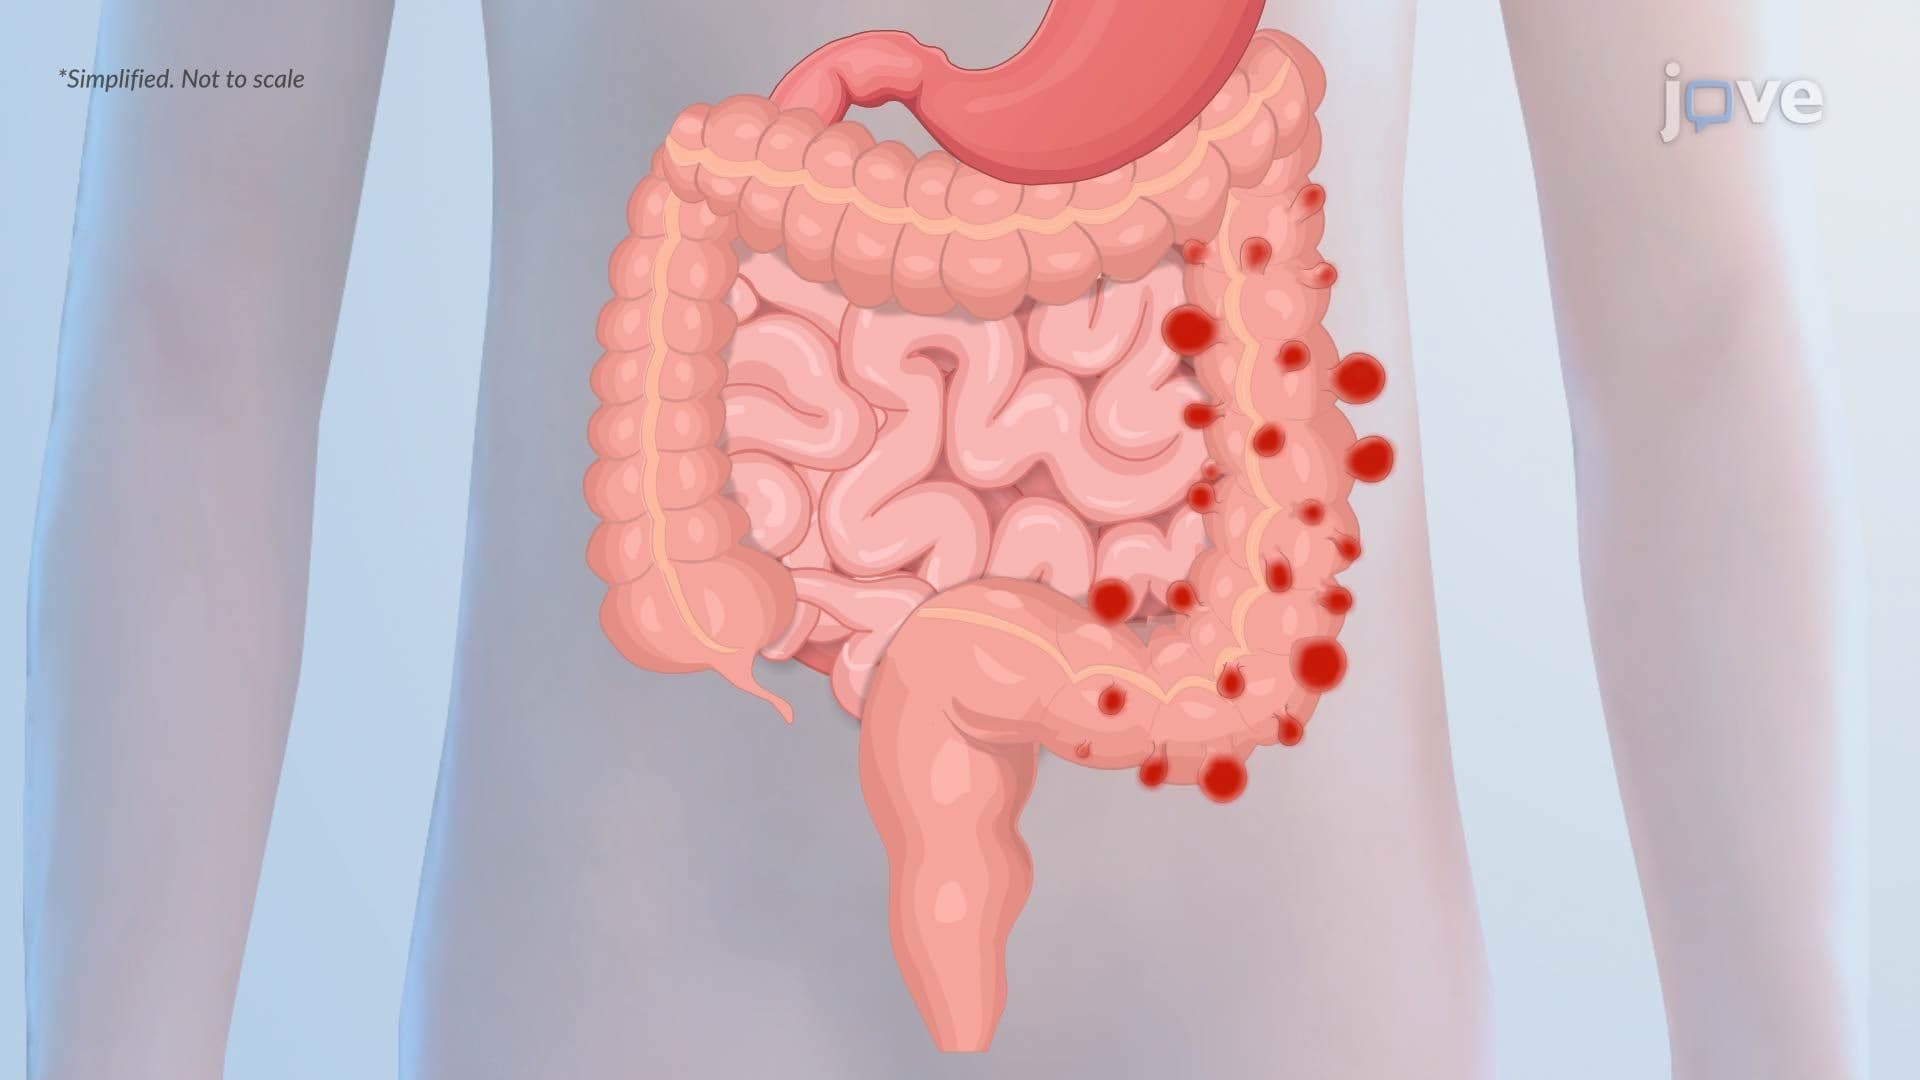
Diverticular Disease of the Colon