Related Experiment Video
Updated: Aug 30, 2026


Development of a Neonatal Piglet Acute Lung Injury Model Recreating the Early Environment of Preterm Infant Lungs
Published on: October 31, 2025
Acinar arterial changes with chronic lung disease of prematurity in the surfactant era
Donald W Thibeault1, William E Truog, Ikechukwu I Ekekezie
1Department of Pediatrics, Children's Mercy Hospital, Kansas City, Missouri 64108, USA. dthibeault@cmh.edu

Insights
Infants with severe chronic lung disease (CLD) show arterial wall changes suggesting pulmonary hypertension (PH). These findings indicate PH is likely in severe CLD cases and may guide oxygen therapy decisions.
Area of Science:
- Neonatal Medicine
- Pediatric Cardiology
- Pulmonary Medicine
Background:
- Echocardiographic studies suggest pulmonary hypertension (PH) may worsen chronic lung disease (CLD) severity in infants.
- Understanding arterial wall remodeling in CLD is crucial for managing potential PH.
Purpose of the Study:
- To investigate acinar arterial wall characteristics in infants with varying degrees of CLD.
- To determine if arterial wall changes correlate with CLD severity and suggest PH.
Main Methods:
- Analysis of lung tissue from control infants and infants with mild, moderate, and severe CLD, including those with prolonged rupture of fetal membranes (PROM) and persistent pulmonary hypertension (PPHN).
- Vessels were stained for elastic tissue and smooth muscle actin.
- Assessment of percent arterial wall thickness (%AWT), smooth muscle, and elastic laminae extent at different airway levels.
Main Results:
- Infants with mild CLD showed less %AWT at alveolar ductal and saccular levels compared to controls and severe CLD, suggesting delayed postnatal thinning or remodeling.
- Severe CLD infants exhibited higher circumferential actin and increased elastic laminae extent compared to controls and mild CLD.
- Arterial wall changes were more pronounced in PROM and PPHN infants than in severe CLD infants.
Conclusions:
- Pulmonary hypertension (PH) is a significant concern in infants with severe chronic lung disease (CLD) before discharge at 36 weeks.
- Assessing CLD severity and utilizing echocardiography can inform subsequent oxygen therapy strategies.
Abstract:
Because echocardiographic studies on infants with chronic lung disease (CLD) suggest that pulmonary hypertension (PH) may contribute to its severity, we studied acinar arterial walls in the following surfactant-era infants: controls (n=38): 22-41 weeks of gestational age (GA), exposed briefly to oxygen and positive pressure ventilation, died within 48 hr of birth; prolonged rupture of fetal membranes (PROM) and persistent pulmonary hypertension (PPHN) (n=17); and SCORE (integrated area under curve of average daily FiO2 x average daily MAP) groups (<20, 20-69, and 70-500; mild, moderate, and severe clinical lung disease, respectively, n=35): 23-30 weeks GA, lived 7-79 days. Lungs were stained for elastic tissue and smooth muscle actin. Vessels were assessed for percent of vessel circumference with smooth muscle, extent of elastic laminae in the walls, and percent arterial wall thickness (%AWT) at three levels: terminal to respiratory bronchiole transition (TRB), alveolar duct, and saccule. At the alveolar ductal and saccular levels, percent arterial wall thickness (%AWT) in mild CLD (SCORE < 20) was less than controls (P < 0.05) and those with more severe CLD (SCORE 70-500), indicating that normal postnatal arterial wall thinning may be delayed, or there is remodeling associated with increased %AWT. Severe CLD infants also had a significantly higher percent of circumferential actin than those with milder disease (SCORE < or = 69) and controls. In moderate and severe CLD, there was an increase in extent of the elastic laminae compared to controls and mild CLD. These changes were also significantly greater in PROM and PPHN infants compared to even severe CLD. We conclude that PH is a real possibility in severe CLD infants after discharge at 36 weeks. Grading the severity of CLD at discharge, and echocardiographic studies, may guide subsequent oxygen therapy.
Related Concept Videos
 01:05
Breathing
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:23
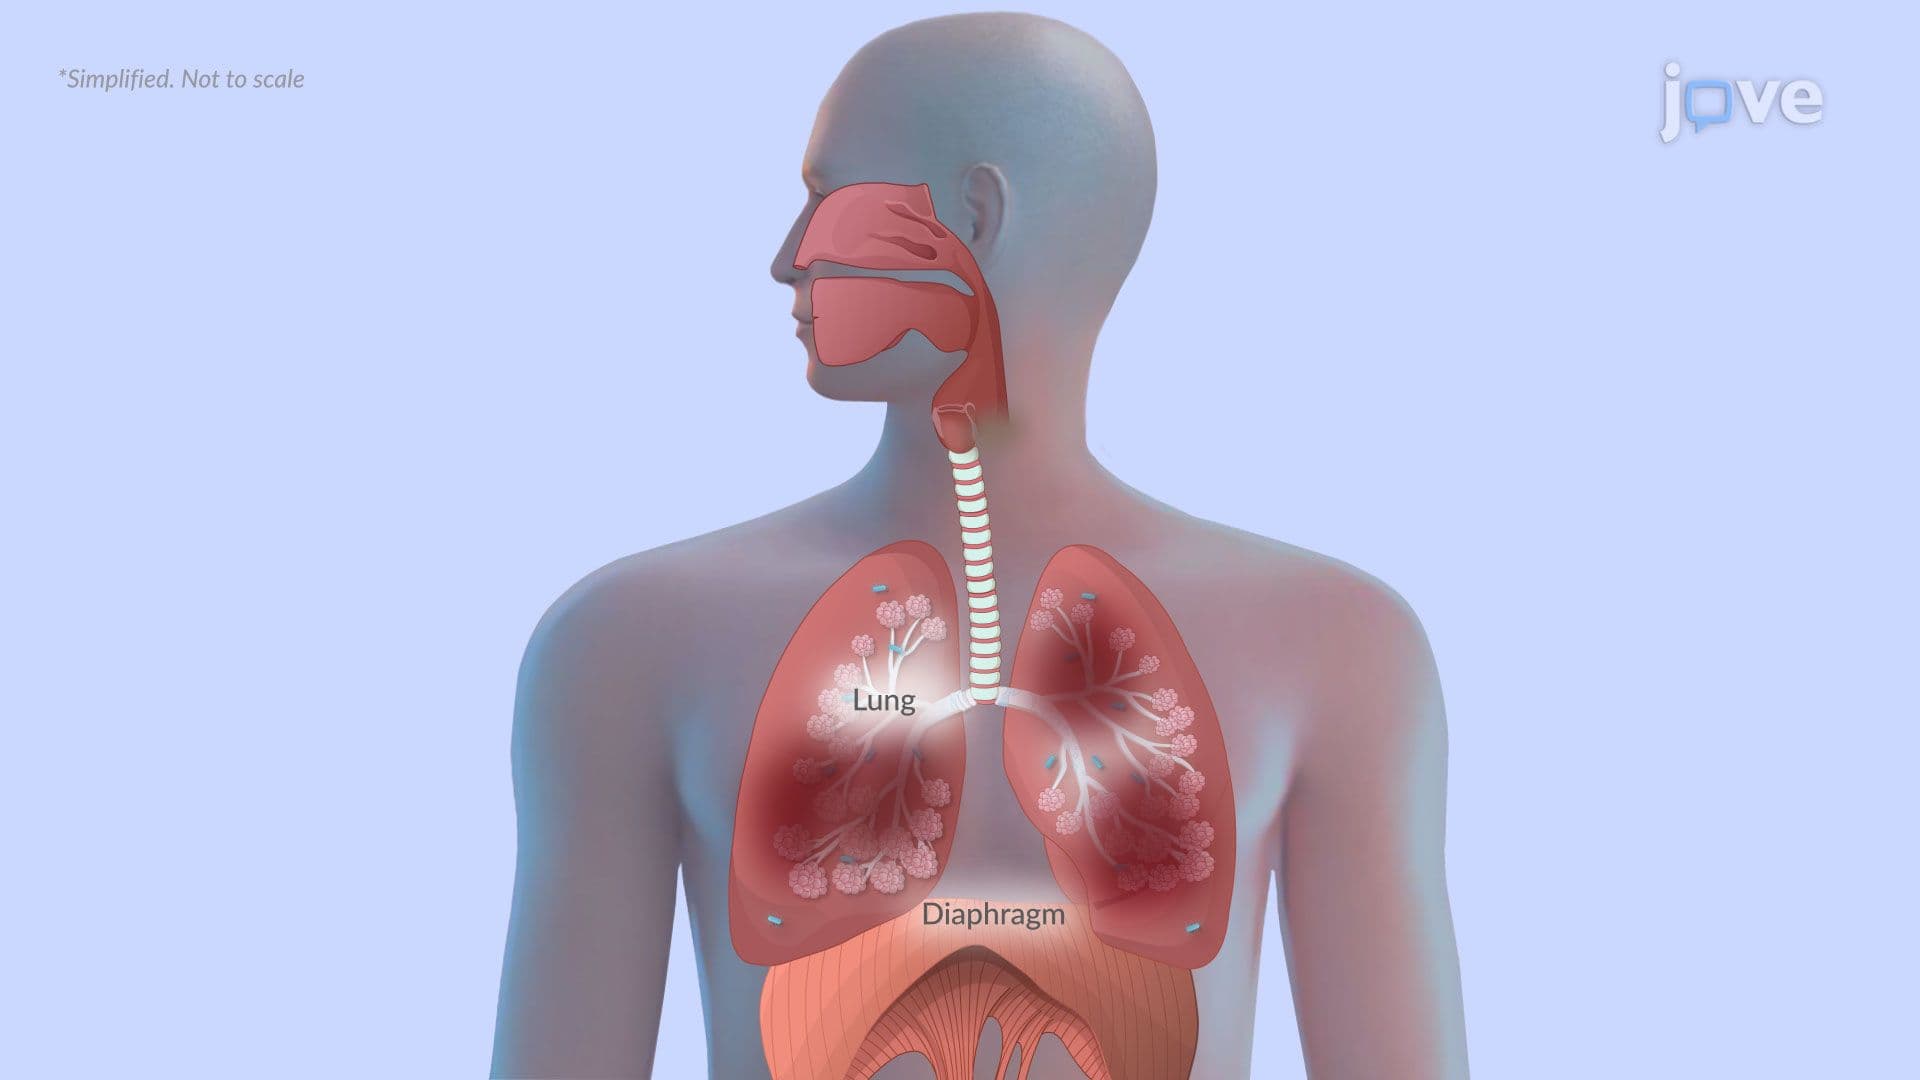
Chronic Obstructive Pulmonary Disease I: Introduction
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...