Related Experiment Video
Updated: Aug 29, 2026


A Novel Method: Super-selective Adrenal Venous Sampling
Published on: September 15, 2017
Plasma cortisol and cortisone concentrations in normal subjects and patients with adrenocortical disorders
Hiroyuki Morita1, Yukinori Isomura, Tomoatsu Mune
1Department of General Medicine, Gifu University School of Medicine, Tsukasamachi, Japan.

Abstract:
Two isozymes of the 11beta-hydroxysteroid dehydrogenase (11-HSD) are responsible for the interconversion of cortisol (F) and cortisone (E). The type 1 isozyme, 11-HSD1, acts mainly as a reductase in vivo, activating E to F, whereas the type 2, 11-HSD2, acts as a dehydrogenase, inactivating F to E. 11-HSD1 is the most abundant in the liver and 11-HSD2 in the kidney. In this study, we attempted to determine which isozyme and organs primarily contribute to equilibrium of plasma F and E concentrations in the peripheral circulation and to clarify differences in 11-HSD activities among adrenocortical disorders. Upon selective catheterizations for adrenocortical and renovascular disorders, plasma F and E concentrations in the femoral vein were closer to those in the renal vein than those in the hepatic vein. Values for mean plasma F/E ratios in the peripheral vein were in-between those of the adrenal and renal veins. A double reciprocal plot between peripheral plasma F and E concentrations in patients with various adrenocortical tumors was almost identical to that in normal subjects. Mean plasma F/E ratio in peripheral blood was higher in patients with Cushing's syndrome and was lower in patients with primary aldosteronism and nonfunctioning adrenocortical adenoma than that in normal subjects. These results suggest that renal 11-HSD2 is a main factor controlling the equilibrium of plasma F and E concentrations in the periphery and that cortisol and aldosterone excess do not change the equilibrium of plasma F and E concentrations in the peripheral circulation, but may alter expression of 11-HSD2. Alternation of 11-HSD2 activities as well as corticosteroid levels may be important in the pathophysiology of adrenocortical disorders.


Related Concept Videos
 01:27
Adrenal Gland Disorders
Adrenal insufficiency, characterized by insufficient cortisol and aldosterone production, leads to conditions like Addison's disease. This disorder, affecting the adrenal cortex, exhibits symptoms such as skin bronzing, dehydration, low blood pressure, fatigue, and weight loss. Congenital adrenal hyperplasia, a genetic ailment causing...
 01:19
Cushing Syndrome II: Pathophysiology
 01:26
Cushing Syndrome I: Introduction
 01:31
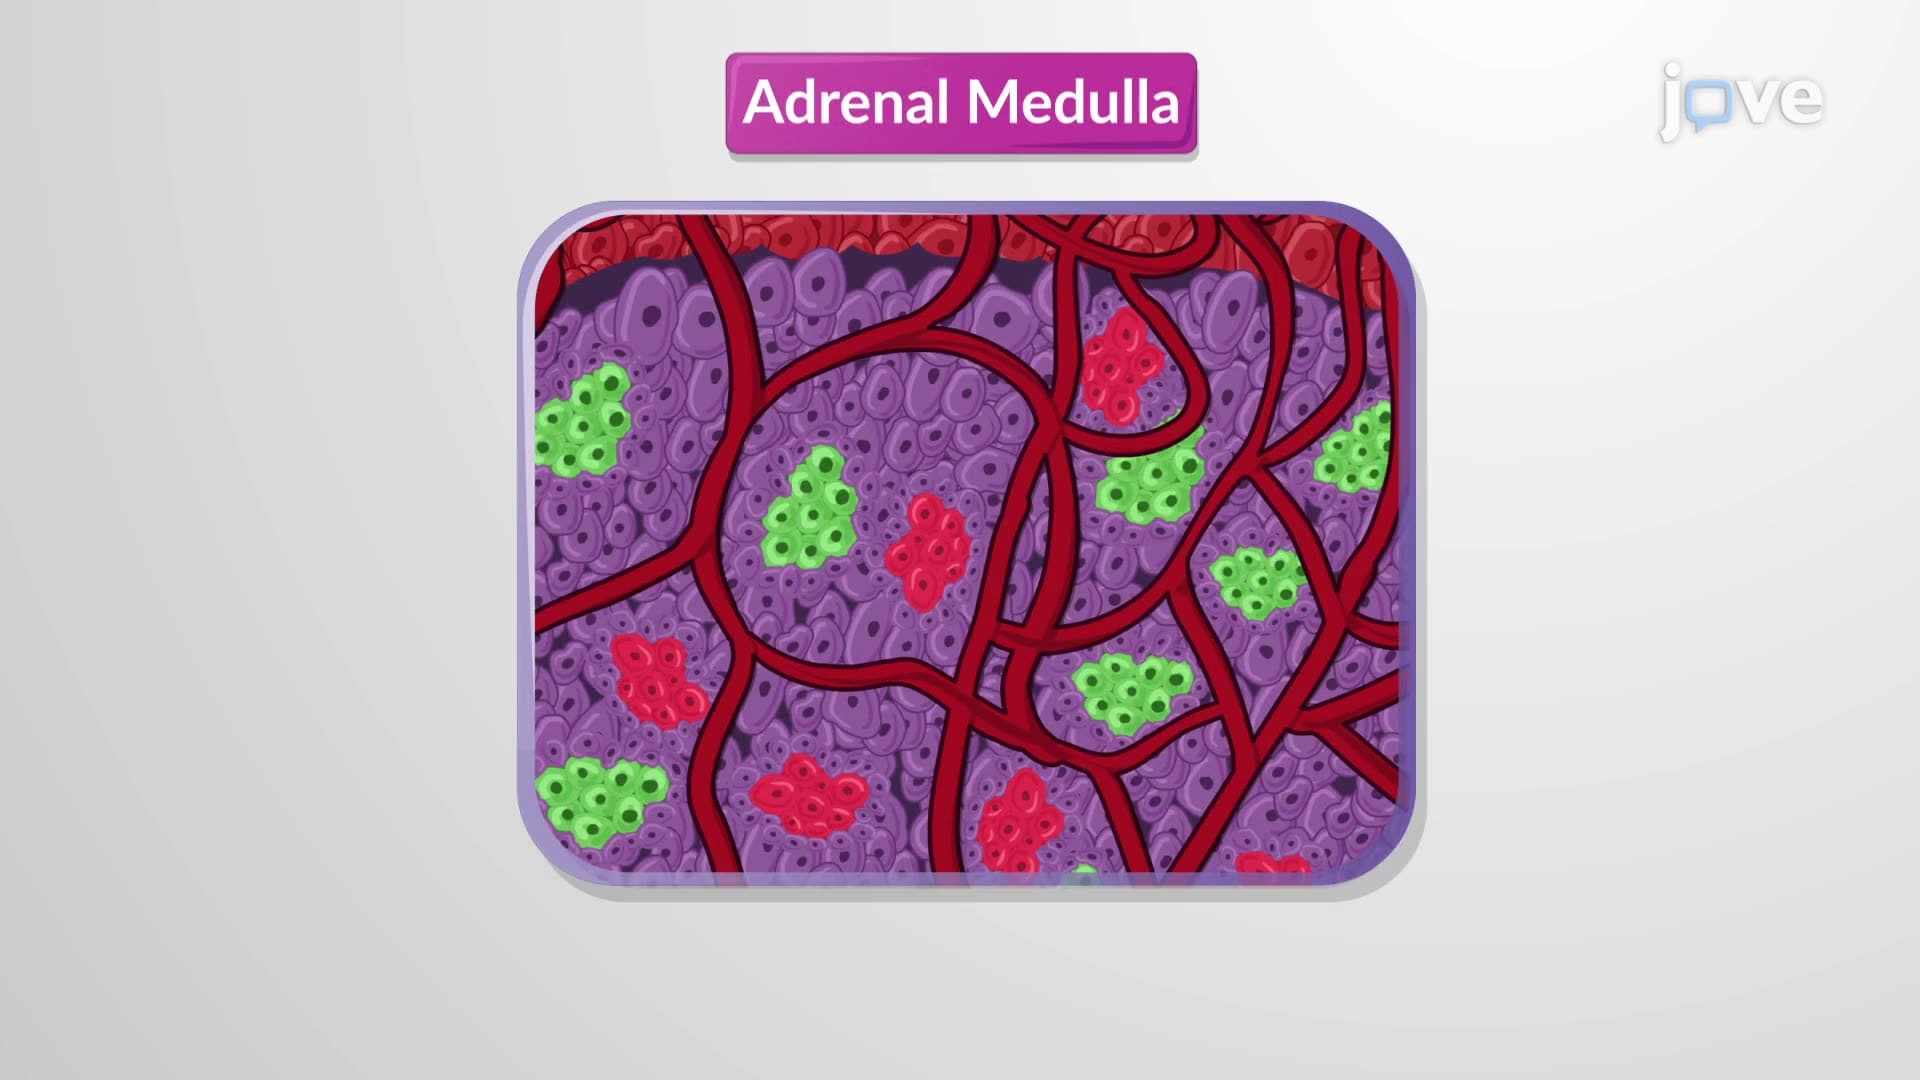
Hormones of the Adrenal Glands
The adrenal cortex, a powerhouse of hormone synthesis, generates over two dozen corticosteroid hormones. The zona glomerulosa produces mineralocorticoids, exemplified by aldosterone, influencing the electrolyte composition of body fluids. The synthesis of glucocorticoids such as cortisol and corticosterone...
 01:37
Hypothalamic-Pituitary Axis
 01:17
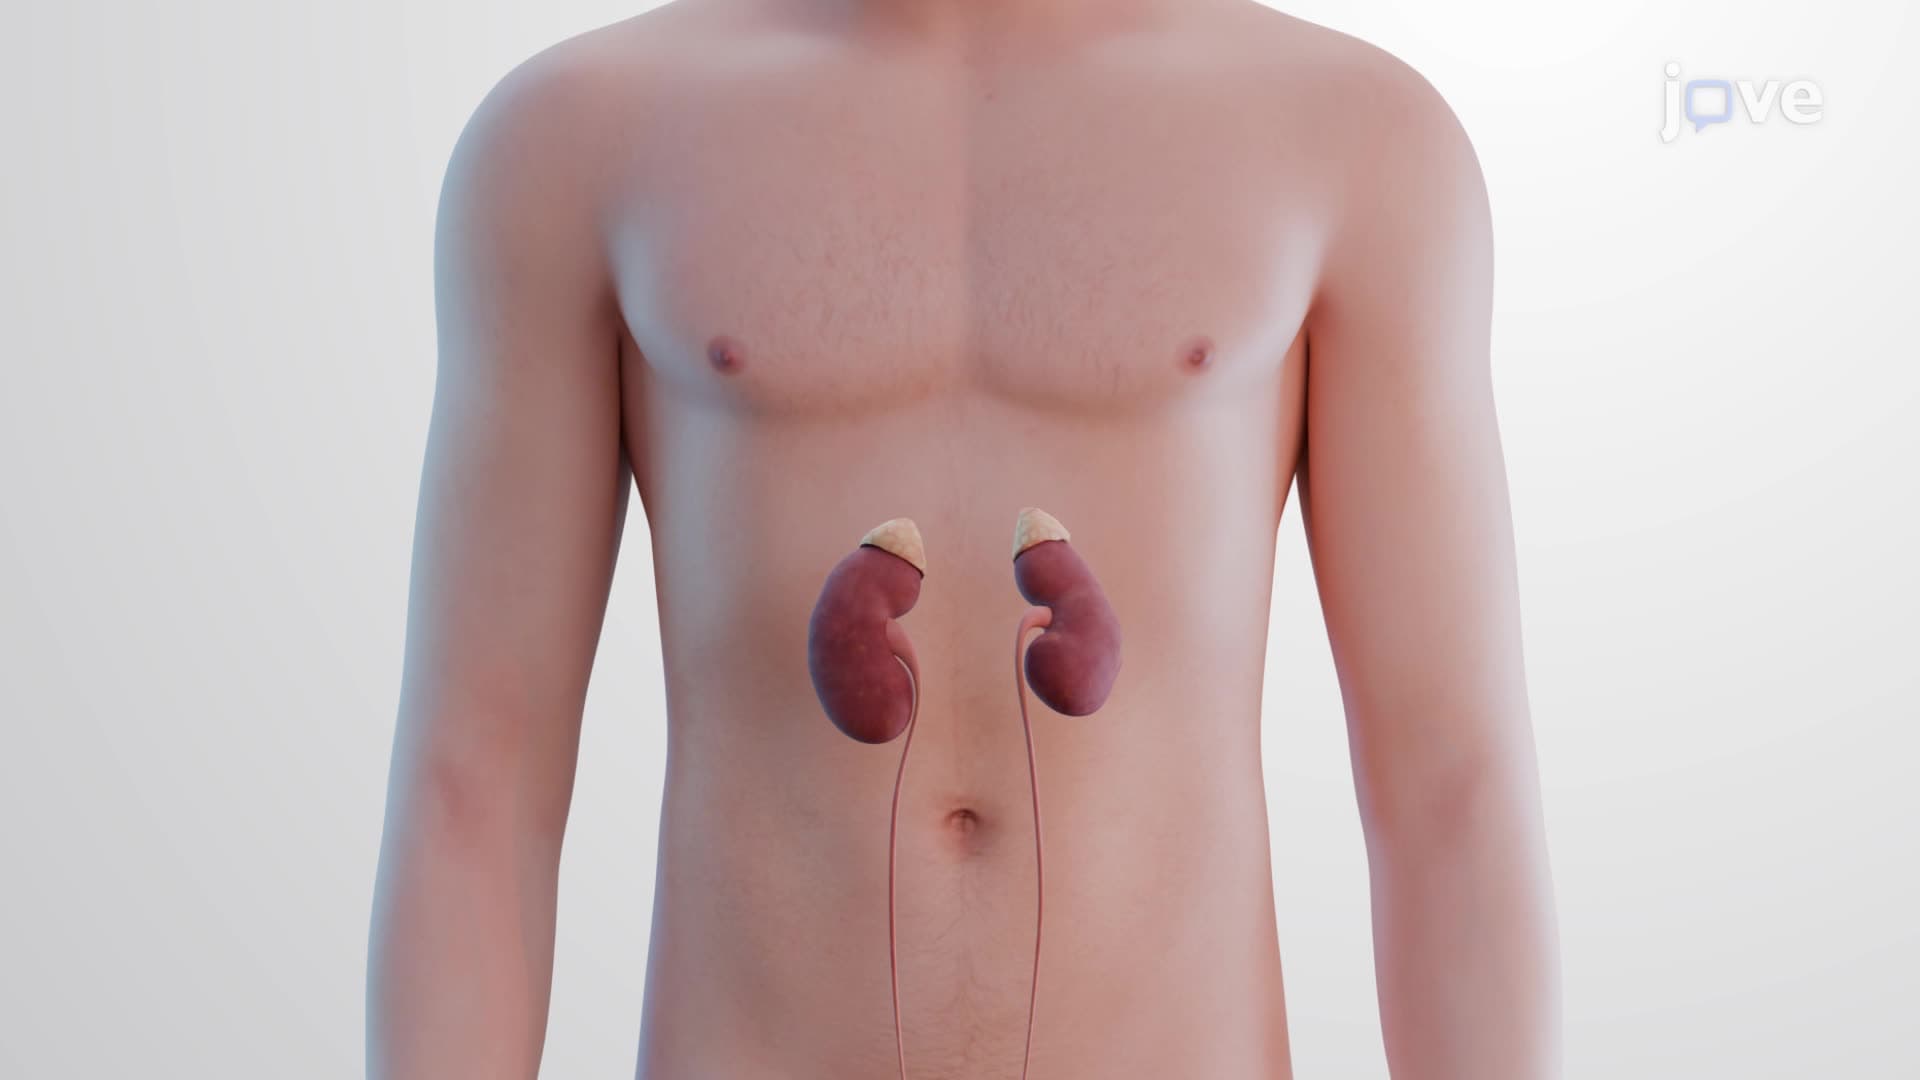
Anatomy of the Adrenal Glands
These glands possess a distinctive yellow tinge due to the stored cholesterol and fatty acids required for hormone synthesis. They are encased in a fibrous capsule and cushioned by fat.
The adrenal gland comprises two distinct regions...