Related Experiment Video
Updated: Aug 29, 2026
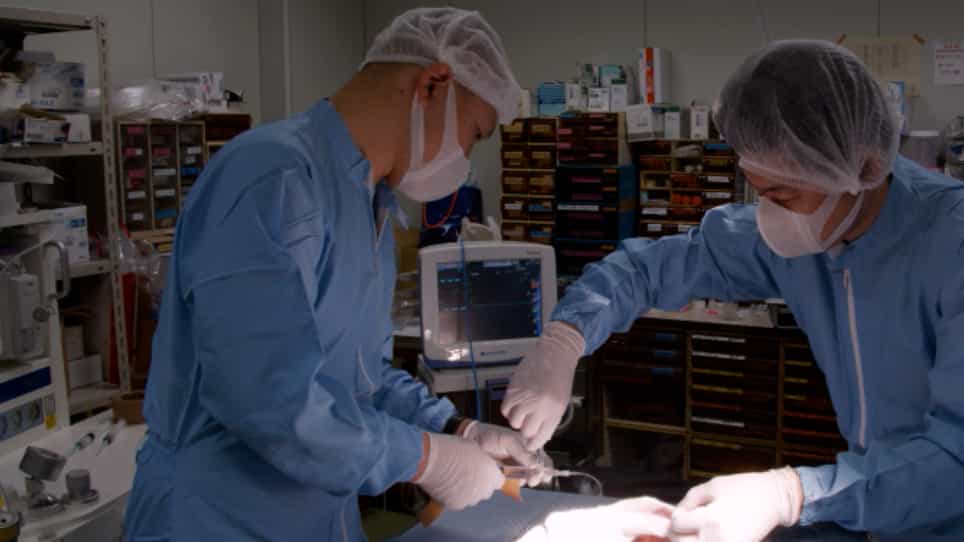
A Rabbit Venous Interposition Model Mimicking Revascularization Surgery using Vein Grafts to Assess Intimal Hyperplasia under Arterial Blood Pressure
Published on: May 15, 2020
Intimal hyperplasia and hemodynamic factors in arterial bypass and arteriovenous grafts: a review
Hiroaki Haruguchi1, Satoshi Teraoka
1Department of Surgery, Kidney Center, Tokyo Women's Medical University, 8-1 Kawada-cho, Shinjuku-ku, 162-8666, Tokyo, Japan. hharu@kc.twmu.ac.jp

Insights
Intimal hyperplasia (IH) causes vascular access graft failure. Hemodynamic factors, including shear stress and turbulence, influence IH development differently in arterial bypass grafts versus arteriovenous grafts, necessitating distinct design strategies.
Area of Science:
- Biomedical Engineering
- Vascular Surgery
- Hemodynamics
Background:
- Intimal hyperplasia (IH) at the graft-vein junction is a primary cause of vascular access graft failure in hemodialysis.
- Hemodynamic factors are strongly linked to IH formation, with distinct patterns observed in arterial bypass grafts (ABGs) and arteriovenous grafts (AVGs).
Purpose of the Study:
- To investigate the relationship between hemodynamic factors and intimal hyperplasia (IH) in vascular access grafts.
- To differentiate the mechanisms of IH development in arterial bypass grafts (ABGs) and arteriovenous grafts (AVGs).
- To evaluate the efficacy of current anastomotic designs in mitigating IH and improving graft patency.
Main Methods:
- Analysis of hemodynamic patterns, including wall shear stress (WSS) and flow turbulence, at graft-vein junctions.
- Comparison of IH development in ABGs and AVGs under varying flow conditions.
- Review of existing anastomotic designs (e.g., venous cuffs, patches) and their impact on graft performance.
Main Results:
- In ABGs, low shear stress, oscillating shear forces, and high WSS gradients contribute to IH at specific anastomosis locations.
- High flow rates in AVGs induce turbulence and endothelial injury, leading to IH.
- While some anastomotic designs reduce IH in ABGs, they have not consistently improved patency in high-flow AVGs.
Conclusions:
- Hemodynamic forces play a critical role in intimal hyperplasia (IH) development in vascular access grafts.
- Distinct hemodynamic environments in ABGs and AVGs require tailored approaches to prevent IH.
- Novel anastomotic designs are needed for high-flow AVGs to improve long-term patency.
Abstract:
Stenosis at the graft-vein junction caused by intimal hyperplasia (IH) is the major cause of failure of vascular access grafts used for hemodialysis. There is a strong relationship between hemodynamic factors and formation of IH. The hemodynamic pattern and the location of IH are different in arterial bypass grafts (ABGs) compared with arteriovenous grafts (AVGs). In an ABG, end-to-side anastomosis of the expanded polytetrafluoroethylene graft and artery produces hemodynamic changes around the junction. IH develops at the arterial floor and the toe and heel of the distal anastomosis. Low shear stress and oscillating shear forces at the arterial floor and the heel plus a high wall sheer stress (WSS) gradient at the toe probably promote IH development. Compliance mismatch between the graft and artery causes turbulence that may contribute to IH formation. The blood flow rate in AVGs is 5-10 times greater than that in ABGs. High flow causes turbulence that injures endothelial cells and eventually results in IH. The peak WSS in AVGs is about 6 N/m(2), much higher than that in ABGs. Excessively high WSS may effect IH formation in AVGs. Several venous cuff or patch anastomotic designs have been used in attempts to regulate hemodynamic factors in grafts. In ABGs, these designs appear to help decrease IH formation. In AVGs, however, they generally have not improved patency rates. In a high-flow system such as an AVG, more drastic changes in anastomotic design may be required.
Related Concept Videos
 01:25
Hemodialysis I: Introduction
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:26
Aneurysm III: Interprofessional Care