Related Experiment Video
Updated: Aug 29, 2026


A Retrograde Implantation Approach for Peritoneal Dialysis Catheter Placement in Mice
Published on: July 20, 2022
The peritoneal membrane: a dynamic dialysis membrane in children
Michel Fischbach1, Börje Haraldsson, Pauline Helms
1Dialysis Children's Unit, CHU Hautepierre, Strasbourg, France.

Insights
Peritoneal dialysis in children requires individualized prescriptions considering the dynamic peritoneal membrane. Optimizing fill volume based on body surface area is crucial for effective dialysis exchange.
Area of Science:
- Pediatric Nephrology
- Renal Replacement Therapy
- Dialysis Membrane Physiology
Background:
- Peritoneal dialysis (PD) prescriptions in children necessitate personalized approaches beyond standard numerical targets like Kt/Vurea and Kcreat.
- The peritoneal membrane, a critical component in PD, functions as a dynamic interface with multiple surface area characteristics.
Purpose of the Study:
- To emphasize the importance of considering the peritoneal membrane's complex surface area dynamics in pediatric PD prescription.
- To highlight the need for individualized PD dosing that accounts for anatomic, contact, and exchange areas of the peritoneum.
Main Methods:
- Analysis of peritoneal membrane surface area characteristics, including anatomic, contact, and exchange areas.
- Evaluation of factors influencing these areas, such as body size (weight vs. body surface area), posture, fill volume, dialysate composition, and inflammatory agents.
Main Results:
- Peritoneal membrane area per kilogram of body weight is larger in infants than adults, necessitating body surface area scaling for intraperitoneal fill volume.
- Intraperitoneal fill volume scaling by body surface area is essential to prevent a low intraperitoneal fill volume/area ratio, which can lead to functionally hyperpermeable exchange.
- Contact area represents 30%-60% of the anatomic area and is influenced by posture and fill volume; exchange area is primarily governed by peritoneal vascular perfusion.
Conclusions:
- Individualizing pediatric peritoneal dialysis prescriptions requires a comprehensive understanding of the peritoneal membrane's triple entity surface area.
- Body surface area scaling of intraperitoneal fill volume is a key factor in optimizing peritoneal dialysis efficacy in children.
- Dynamic factors affecting peritoneal membrane contact and exchange areas must be considered for effective PD management in pediatric patients.
Abstract:
Peritoneal dialysis prescription in children should be individualized--based not only on numerical targets (Kt/Vurea, Kcreat), but also on consideration of the peritoneal membrane, a dynamic dialysis membrane. In fact, the effective peritoneal surface area is at least a triple entity: an anatomic area, a contact area, and an exchange area. The anatomic area appears to be twice as large in infants as in adults if expressed per kilogram of body weight (BW), although the area is independent of age if expressed per square meter of body surface area (BSA). Therefore, scaling of the intraperitoneal fill volume (IPV) by BSA in square meters is necessary to avoid a low IPV/area ratio, which results in a functionally "hyperpermeable" peritoneal exchange. The contact area (the wetted membrane) is only a fraction of the anatomic area--that is, 30%-60% in humans (by computed tomography). Contact area depends on a variety of factors, such as posture and fill volume, that affect the degree of recruitment of membrane contact area. The exchange area is influenced by both the anatomic are and the contact area. However, it is mainly governed by the specific vascular area as determined by the peritoneal vascular perfusion and the capillaries available for exchange. Vascular area is dynamically affected by a variety of factors, such as the composition of the peritoneal dialysis fluid, the fill volume, and possible inflammatory agents.

Related Concept Videos
 01:30
Peritoneal Dialysis I: Introduction and Procedure
 01:15
Dialysis
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
 01:25
Peritoneal Dialysis II: Peritoneal Dialysis Systems and Complications
 01:21
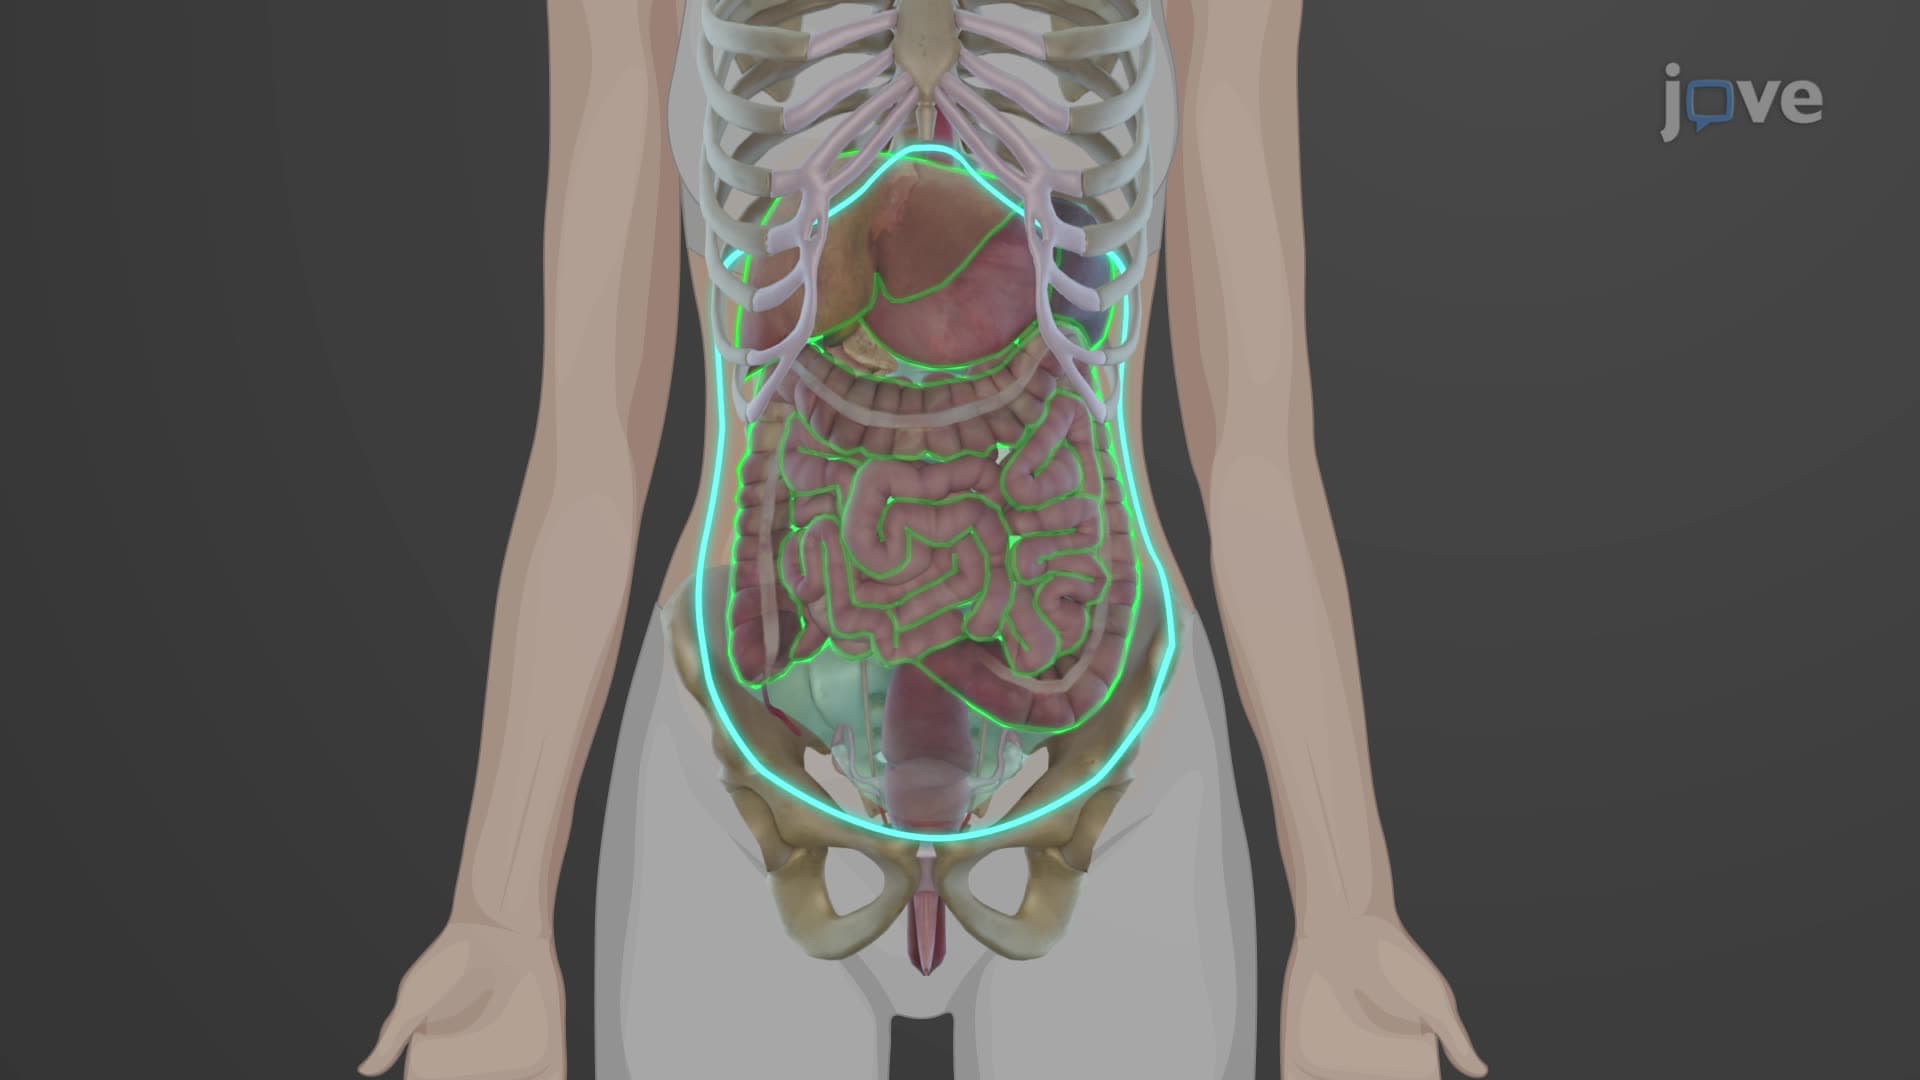
Peritoneum
Anatomy of the Peritoneum
The peritoneum is divided into two layers: the parietal peritoneum and the visceral...
 01:25
Hemodialysis I: Introduction