Related Experiment Video
Updated: Aug 15, 2026

Surgical Placement of Catheters for Long-term Cardiovascular Exercise Testing in Swine
Published on: February 9, 2016
Ventilatory dynamics and control of blood gases after maximal exercise in the Thoroughbred horse
Danielle J Padilla1, Paul McDonough, Casey A Kindig
1Department of Anatomy and Physiology, 228 Coles Hall, Kansas State University, Manhattan, KS 66506, USA.

Abstract:
Despite enormous rates of minute ventilation (Ve) in the galloping Thoroughbred (TB) horse, the energetic demands of exercise conspire to raise arterial Pco(2) (i.e., induce hypercapnia). If locomotory-respiratory coupling (LRC) is an obligatory facilitator of high Ve in the horse such as those found during galloping (Bramble and Carrier. Science 219: 251-256, 1983), Ve should drop precipitously when LRC ceases at the galloptrot transition, thus exacerbating the hypercapnia. TB horses (n = 5) were run to volitional fatigue on a motor-driven treadmill (1 m/s increments; 14-15 m/s) to study the dynamic control of breath-by-breath Ve, O(2) uptake, and CO(2) output at the transition from maximal exercise to active recovery (i.e., trotting at 3 m/s for 800 m). At the transition from the gallop to the trot, Ve did not drop instantaneously. Rather, Ve remained at the peak exercising levels (1,391 +/- 88 l/min) for approximately 13 s via the combination of an increased tidal volume (12.6 +/- 1.2 liters at gallop; 13.9 +/- 1.6 liters over 13 s of trotting recovery; P < 0.05) and a reduced breathing frequency [113.8 +/- 5.2 breaths/min (at gallop); 97.7 +/- 5.9 breaths/min over 13 s of trotting recovery (P < 0.05)]. Subsequently, Ve declined in a biphasic fashion with a slower mean response time (85.4 +/- 9.0 s) than that of the monoexponential decline of CO(2) output (39.9 +/- 4.7 s; P < 0.05), which rapidly reversed the postexercise arterial hypercapnia (arterial Pco(2) at gallop: 52.8 +/- 3.2 Torr; at 2 min of recovery: 25.0 +/- 1.4 Torr; P < 0.05). We conclude that LRC is not a prerequisite for achievement of Ve commensurate with maximal exercise or the pronounced hyperventilation during recovery.

Related Concept Videos
 01:23
Physiological Control of Respiration
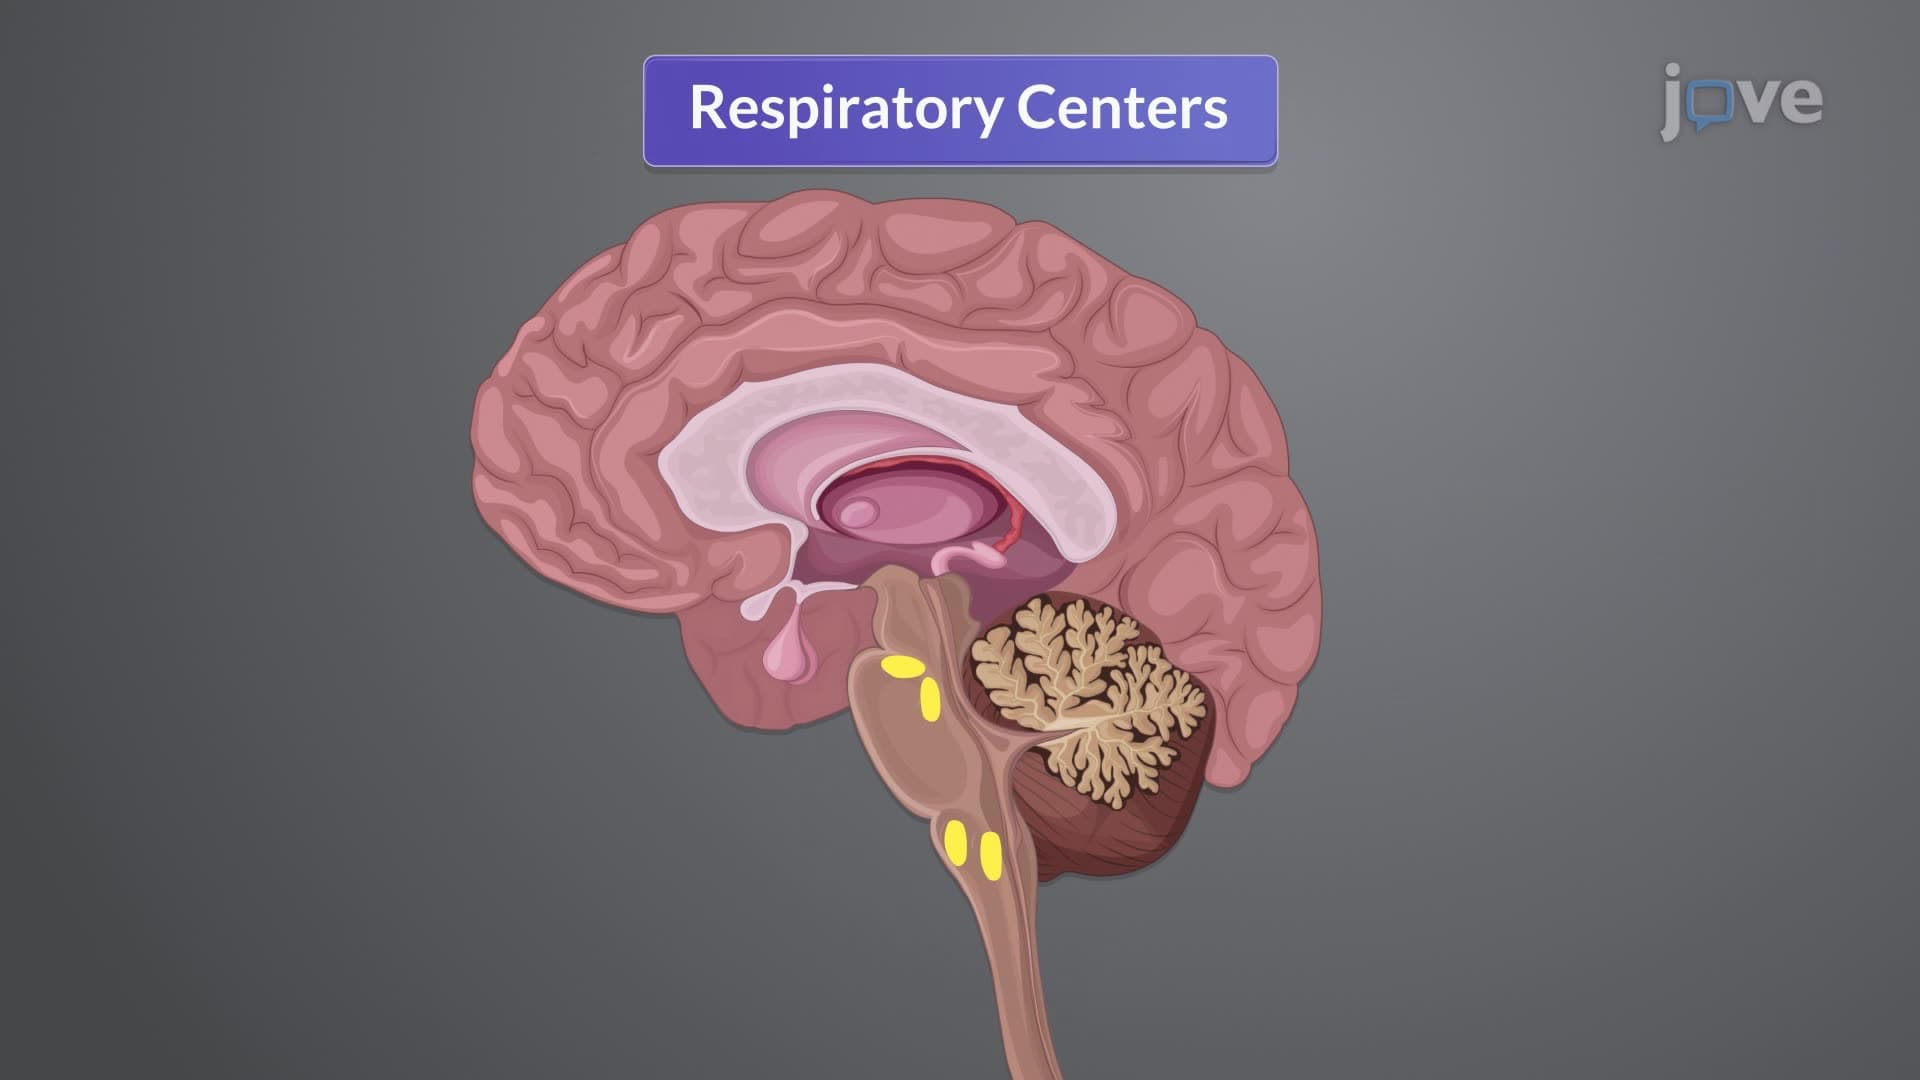
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:20
Respiration and Gaseous Exchange
Respiration involves the exchange of gases, especially oxygen (O2) and carbon dioxide (CO2), between the alveoli and body cells, a process facilitated by blood circulation. As a result, the cardiovascular system, which involves the...
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:25
Hyperpnea and Hyperventilation
 01:22
Physiology of Respiration II: Neurogenic Control of Respiration
Central Control
The brainstem is the primary site of central control, hosting respiratory centers: