Related Experiment Video
Updated: Aug 27, 2026

Preliminary Study on Acupuncture Combined with Grain-sized Moxibustion for Treating Rheumatoid Arthritis with Finger Joint Pain
Published on: May 16, 2025
Dose escalation of parenteral methotrexate in active rheumatoid arthritis that has been unresponsive to conventional
C Michael Lambert1, Sharron Sandhu, Alison Lochhead
1University of Edinburgh, Edinburgh, UK. michael.lambert@luht.scot.nhs.uk

Objective:
To examine whether dose escalation of intramuscular (IM) methotrexate (MTX) up to 45 mg/week improves disease control in patients who have active rheumatoid arthritis (RA) despite receiving conventional doses (15 mg/week) of IM MTX, and to obtain preliminary data on patient tolerability and adverse effects of higher doses of IM MTX.
Methods:
Patients >18 years of age who had active RA, defined as a European League Against Rheumatism (EULAR) Disease Activity Score in 28 joints (DAS28) of >3.2, and who had received 15-20 mg/week of oral MTX for at least 2 months were switched (week 0) to 15 mg/week of IM MTX for 6 weeks. Patients whose DAS28 remained >3.2 at both week 4 and week 6 were randomized, in a double-blind manner, either to continue to receive 15 mg/week IM MTX with monthly placebo escalation or to receive escalating doses of IM MTX monthly up to 45 mg/week. The dose of MTX or placebo was escalated every 4 weeks if the DAS28 was >2.5. Safety assessments and determination of the DAS28 were performed every 2 weeks and monthly, respectively. Disease activity parameters from the American College of Rheumatology (ACR) core disease activity set and health status as recorded on the Medical Outcomes Study Short-Form 12 were determined at baseline (week 0) and final assessment (week 22). The primary outcome was the percentage of patients in each group achieving a target DAS28 of <3.2. Secondary outcomes comprised the percentage of patients whose DAS28 improved by >1.2, the percentage of patients achieving a 20% improvement in the ACR core disease activity measures (ACR20), and the percentage of patients achieving a good response, a moderate response, or no response in accordance with the EULAR response criteria.
Results:
Sixty-four patients were eligible for entry and were switched from oral MTX to 15 mg/week IM MTX. At baseline, the mean +/- SD DAS28 was 5.6 +/- 0.88; after 6 weeks of IM MTX, the DAS28 had improved by a mean of 0.42 (95% confidence interval [95% CI] 0.15-0.69). At 6 weeks, 54 patients still had a DAS28 of >3.2 and were therefore eligible for randomization. By 22 weeks, 1 patient (3.7%) in each group achieved the primary outcome of a DAS28 <3.2 (95% CI for the difference between the groups -15% to +15%). Five patients (18.5%) in each group showed an improvement of >1.2 in the DAS28 (95% CI for the difference between the groups -18% to +18%). One patient (3.7%) in each group achieved an ACR20 response, but none achieved a good response as defined by the EULAR response criteria. One patient in each group had a serious adverse reaction; minor adverse reactions were more frequently reported in the dose escalation group.
Conclusion:
Switching from oral to parenteral MTX 15 mg/week results in a minor improvement in disease control. For patients with active RA receiving 15 mg/week IM MTX, increasing the dose up to 45 mg/week does not improve disease control. Higher doses of IM MTX were generally well tolerated and not associated with an increase in serious adverse reactions to the drug.
Insights
Switching to injectable methotrexate (MTX) offers minor rheumatoid arthritis (RA) control improvement. Escalating doses up to 45 mg/week did not enhance disease control but was generally well-tolerated.
Area of Science:
- Rheumatology
- Pharmacology
- Clinical Trials
Background:
- Conventional oral methotrexate (MTX) may be insufficient for active rheumatoid arthritis (RA).
- Intramuscular (IM) MTX is an alternative administration route for RA management.
- Assessing higher IM MTX doses is crucial for optimizing RA treatment.
Purpose of the Study:
- To evaluate if escalating IM MTX doses (up to 45 mg/week) improve disease control in RA patients with active disease on 15 mg/week IM MTX.
- To assess the tolerability and adverse effects of higher IM MTX doses.
Main Methods:
- Patients with active RA (DAS28 >3.2) on oral MTX were switched to 15 mg/week IM MTX.
- Non-responders (DAS28 >3.2) were randomized to continue 15 mg/week IM MTX or escalate to 45 mg/week IM MTX.
- Disease activity (DAS28, ACR criteria) and safety were monitored over 22 weeks.
Main Results:
- Switching to 15 mg/week IM MTX showed a minor improvement in DAS28.
- No significant difference in achieving DAS28 <3.2 or DAS28 improvement >1.2 between groups.
- ACR20 response was low in both groups; no good EULAR responses were observed.
- Minor adverse events were more frequent in the dose escalation group; serious adverse reactions were similar.
Conclusions:
- Parenteral administration of 15 mg/week IM MTX provides a modest benefit for RA disease control.
- Dose escalation of IM MTX to 45 mg/week does not improve disease control in active RA.
- Higher doses of IM MTX were generally safe and well-tolerated, without increased serious adverse reactions.
Related Concept Videos
 01:29
Drugs for Treatment of Crohn's Disease in IBD Using Immunomodulatory Agents
 01:29
Therapeutic Drug Monitoring: Affecting Factors
 01:24
Rational Dosage Regimen: Maintenance Dose and Loading Dose
In most cases, drugs are administered repetitively or infused continuously to maintain a steady-state concentration in the body. At a steady state,...
 01:28
Dosage Regimens: Designs and Approaches
 01:01
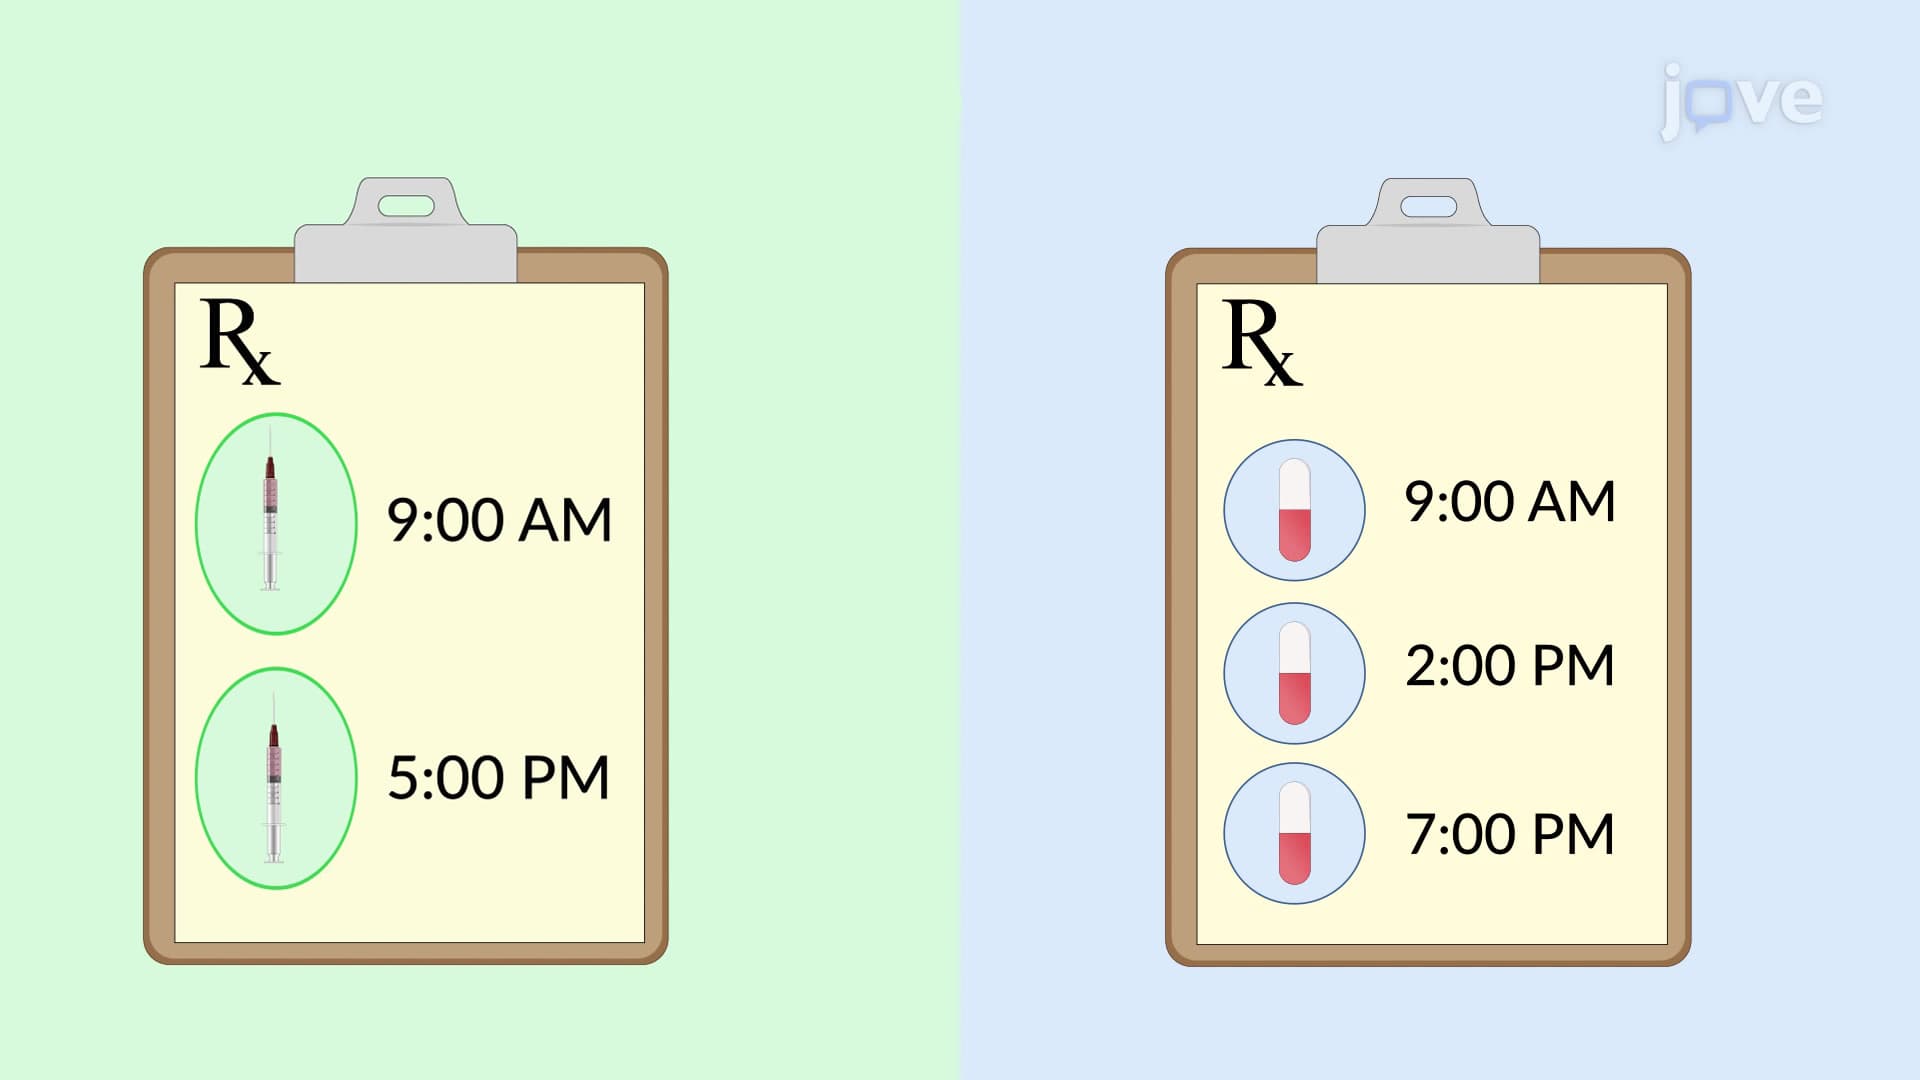
Dosage Regimen: Fixed Dose
Fixed-dose regimens can be used for various routes of administration, including intravenous (IV) injections and oral medications. For IV administration, a predetermined amount of the drug is...
 01:21
Drug Accumulation During Multiple Dosing: Repetitive IV Injections