Related Experiment Video
Updated: Aug 17, 2026

Measuring Neuromuscular Junction Functionality
Published on: August 6, 2017
Prolonged neuromuscular blockade as a result of malnutrition-induced pseudocholinesterase deficiency
Ahtsham Niazi1, Irene E Leonard, Breda O'Kelly
1Department of Anaesthesia and Intensive Care, St. Vincent's University Hospital, Dublin, Ireland. Ahtshamniazi@hotmail.com

Abstract:
Mivacurium is a short-acting neuromuscular blocking drug, ideal for short surgical procedures. The brief duration of action depends on rapid hydrolysis by plasma cholinesterase. An inherited or acquired deficiency of plasma cholinesterase can prolong the effect of mivacurium. We present an unusual case of unanticipated postoperative apnea following mivacurium administration, as a result of acquired plasma cholinesterase deficiency, in a patient with previous uneventful exposure to both mivacurium and suxamethonium (succinylcholine).
Insights
Acquired plasma cholinesterase deficiency can unexpectedly prolong mivacurium's effects, leading to postoperative apnea. This case highlights the importance of considering enzyme deficiencies even after prior uneventful exposures.
Area of Science:
- Anesthesiology
- Pharmacology
- Biochemistry
Background:
- Mivacurium is a short-acting neuromuscular blocker used in surgery.
- Its action is terminated by plasma cholinesterase hydrolysis.
- Deficiencies in this enzyme can extend its effects.
Observation:
- A patient experienced prolonged apnea post-surgery after mivacurium administration.
- This occurred despite previous uneventful exposures to mivacurium and suxamethonium.
- The patient had an acquired deficiency in plasma cholinesterase.
Findings:
- Acquired plasma cholinesterase deficiency was identified as the cause of prolonged neuromuscular blockade.
- This led to unanticipated postoperative apnea.
- The patient's history of uneventful exposure masked the underlying deficiency.
Implications:
- Clinicians must consider acquired plasma cholinesterase deficiency in prolonged neuromuscular blockade, even with prior tolerance.
- This case underscores the need for vigilant monitoring in patients receiving neuromuscular blocking agents.
- Awareness of enzyme deficiencies is crucial for managing anesthetic complications.


Related Concept Videos
 01:26
Anticholinesterase Agents: Poisoning and Treatment
Irreversible agents form a strong bond with the cholinesterase enzyme, making it inactive. The breakdown of the phosphorylated enzyme is slower than the...
 01:17
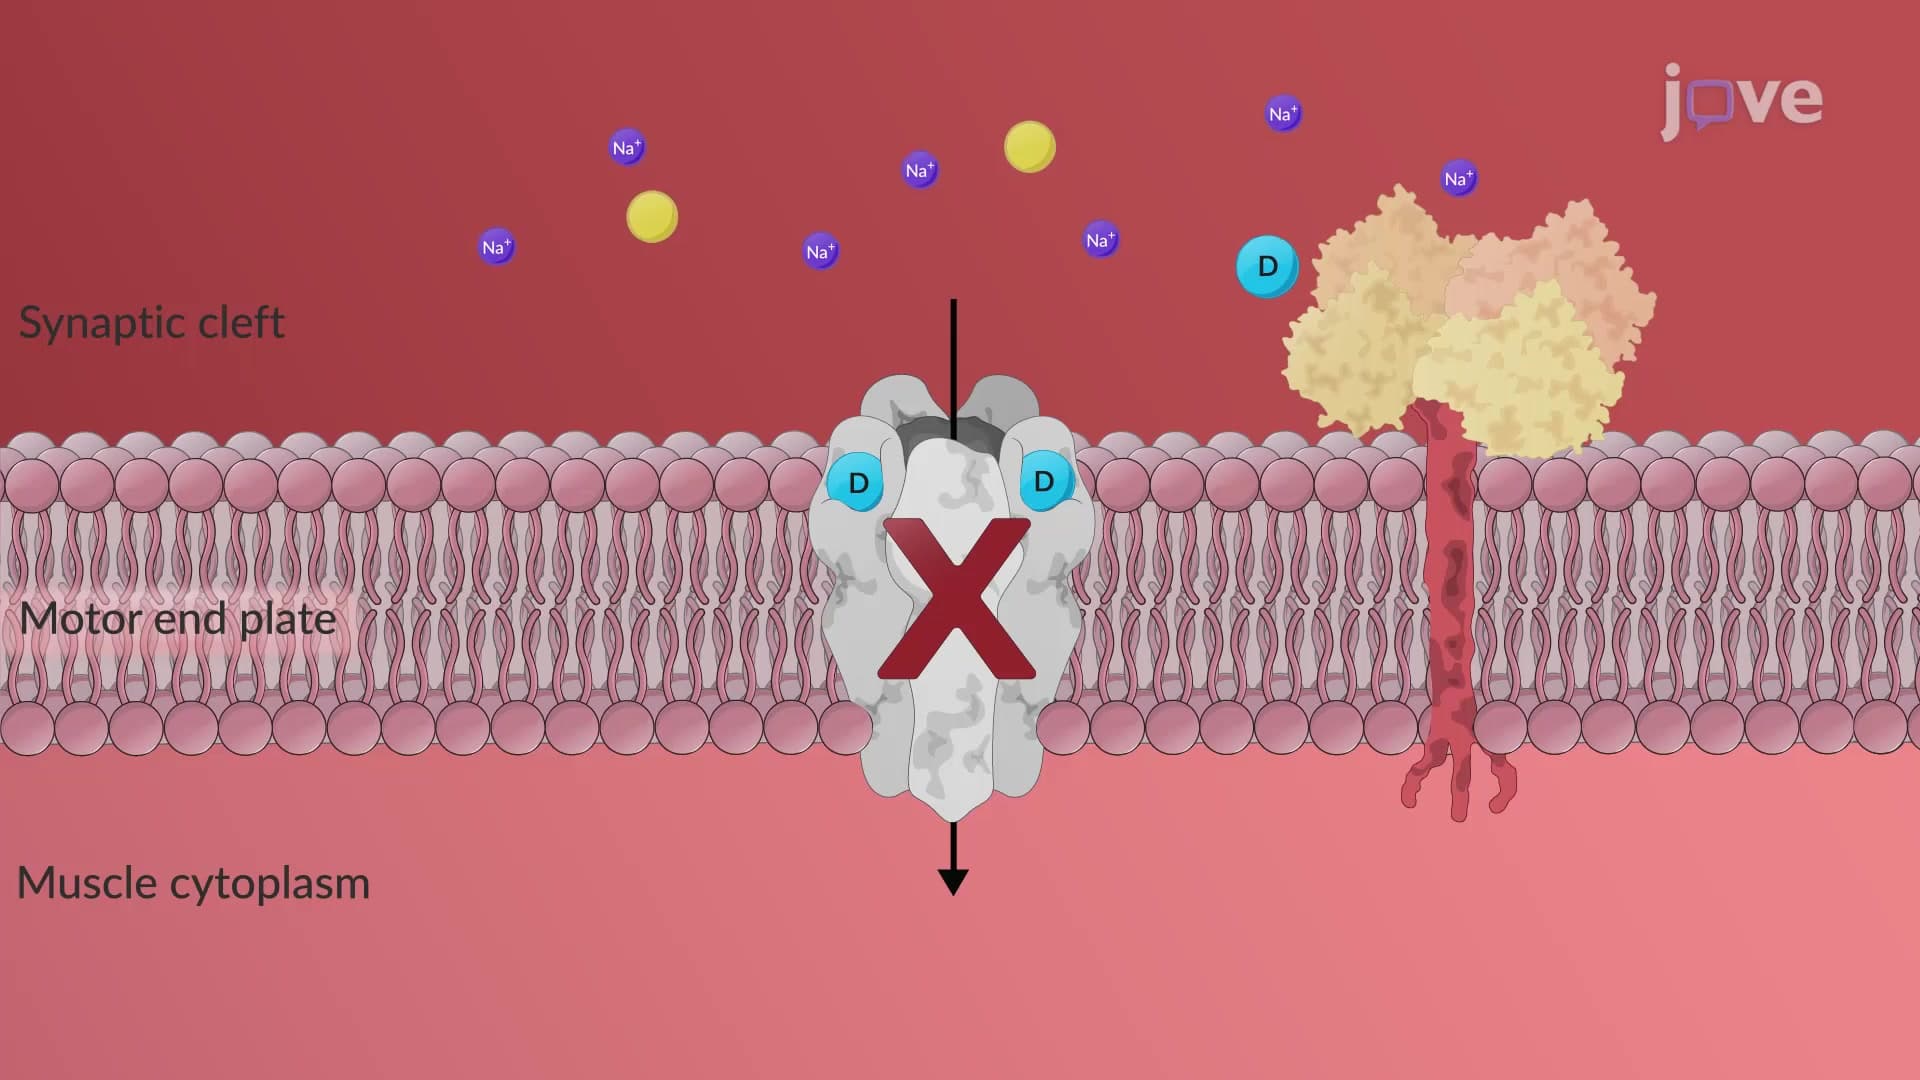
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:11
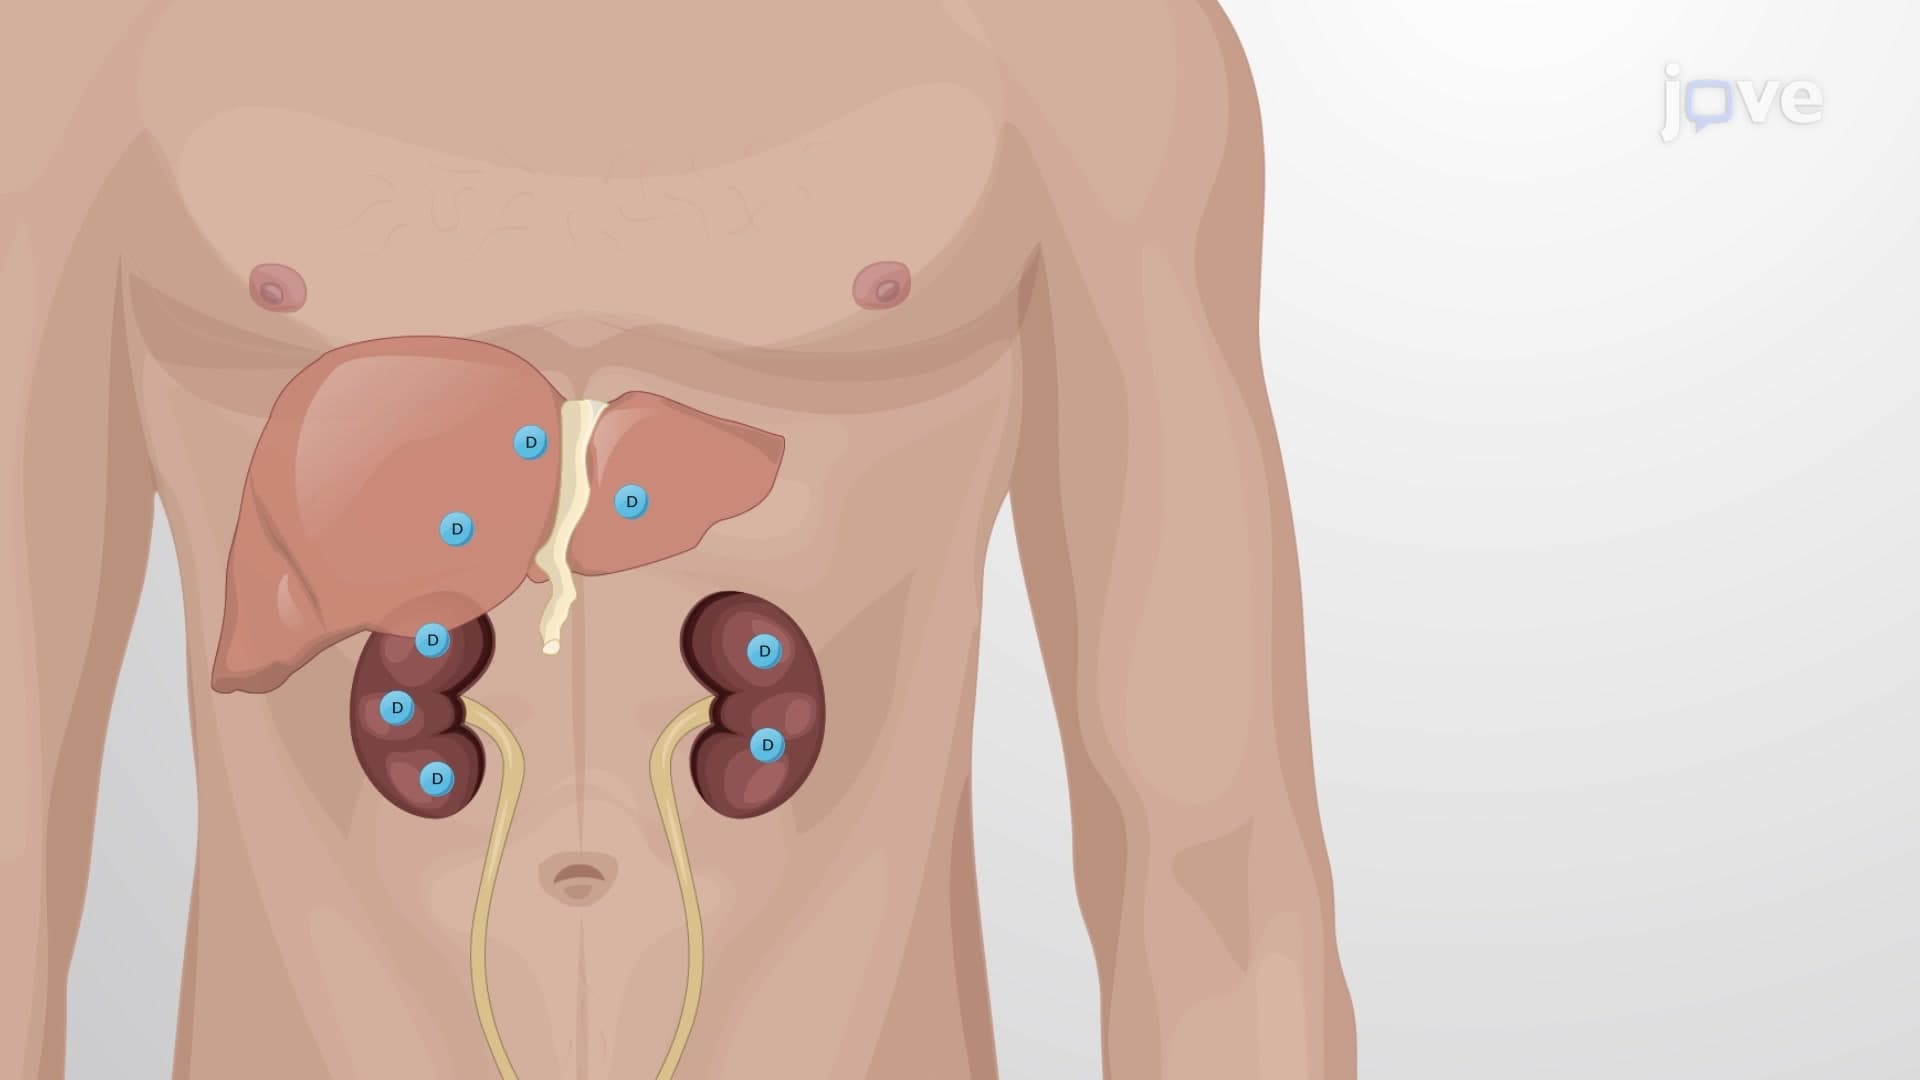
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
 01:28
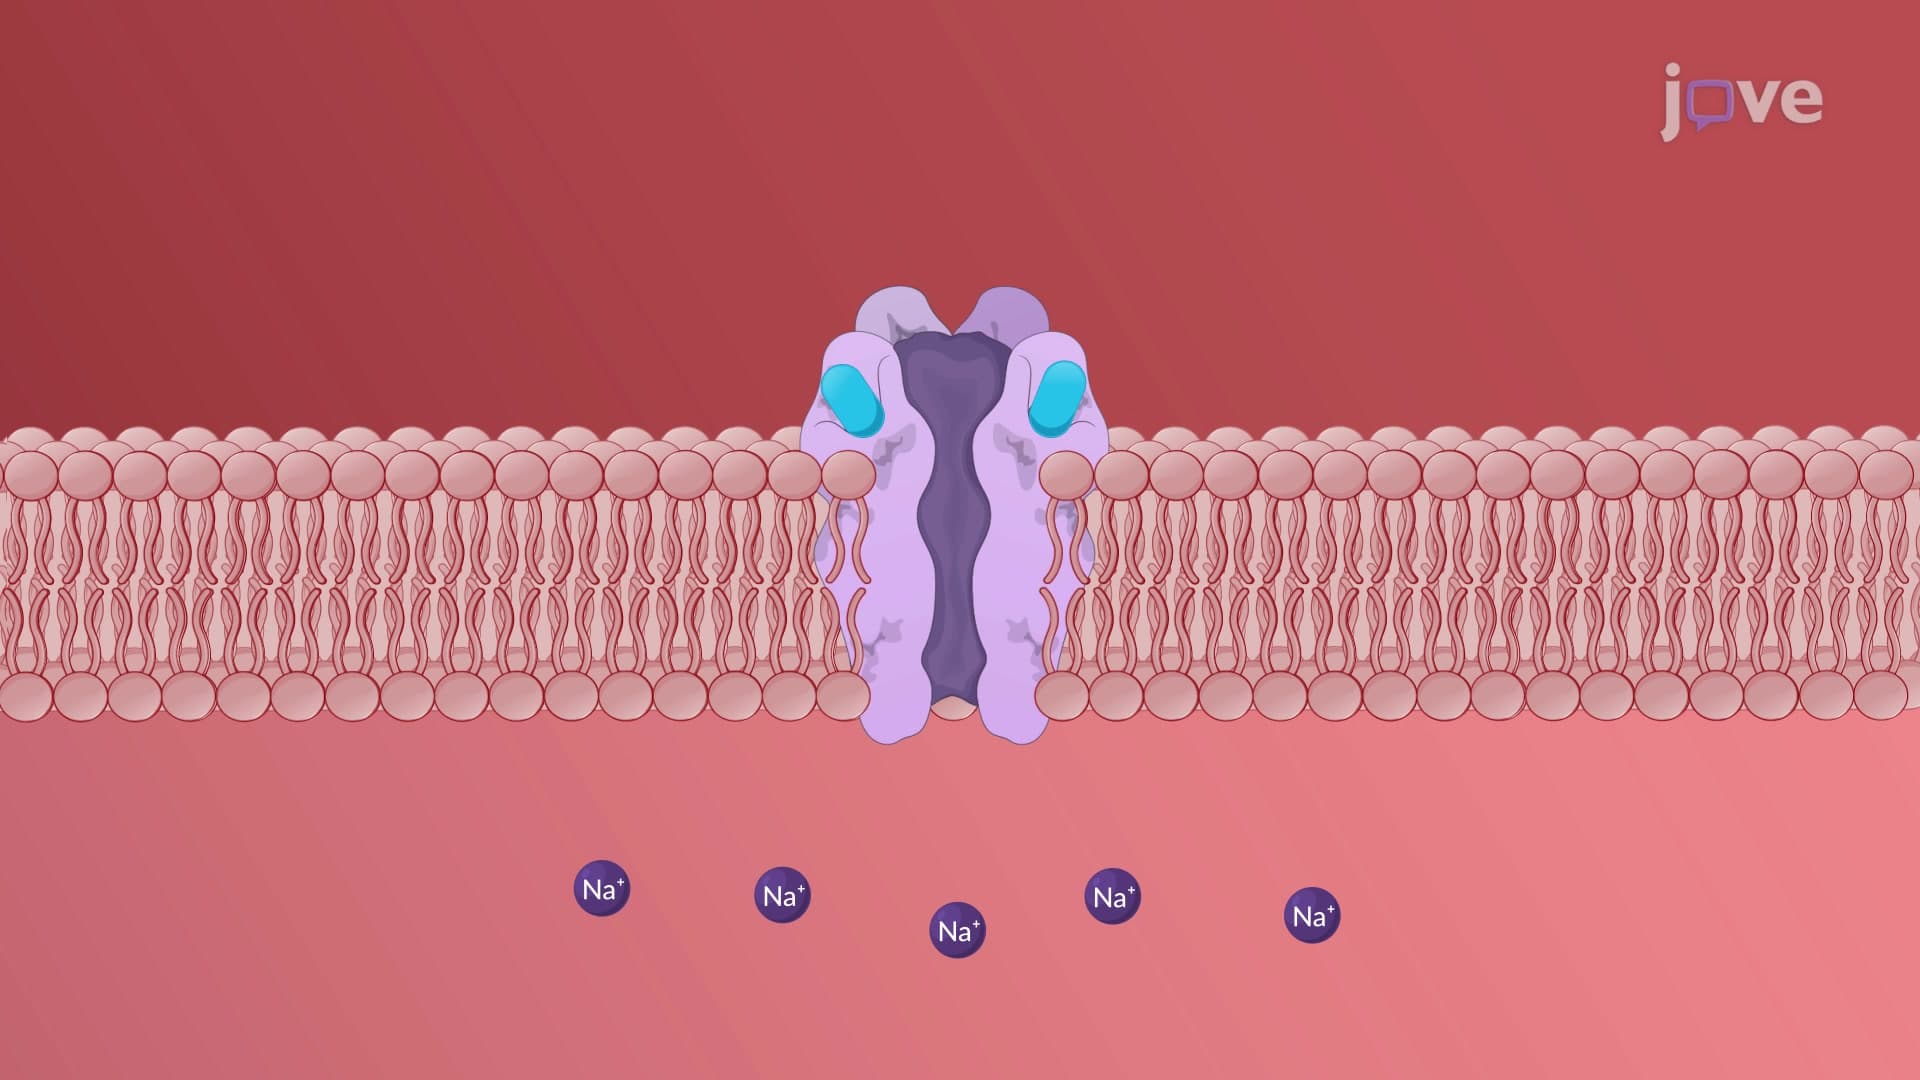
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because succinylcholine...
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...