Related Experiment Video
Updated: Aug 24, 2026
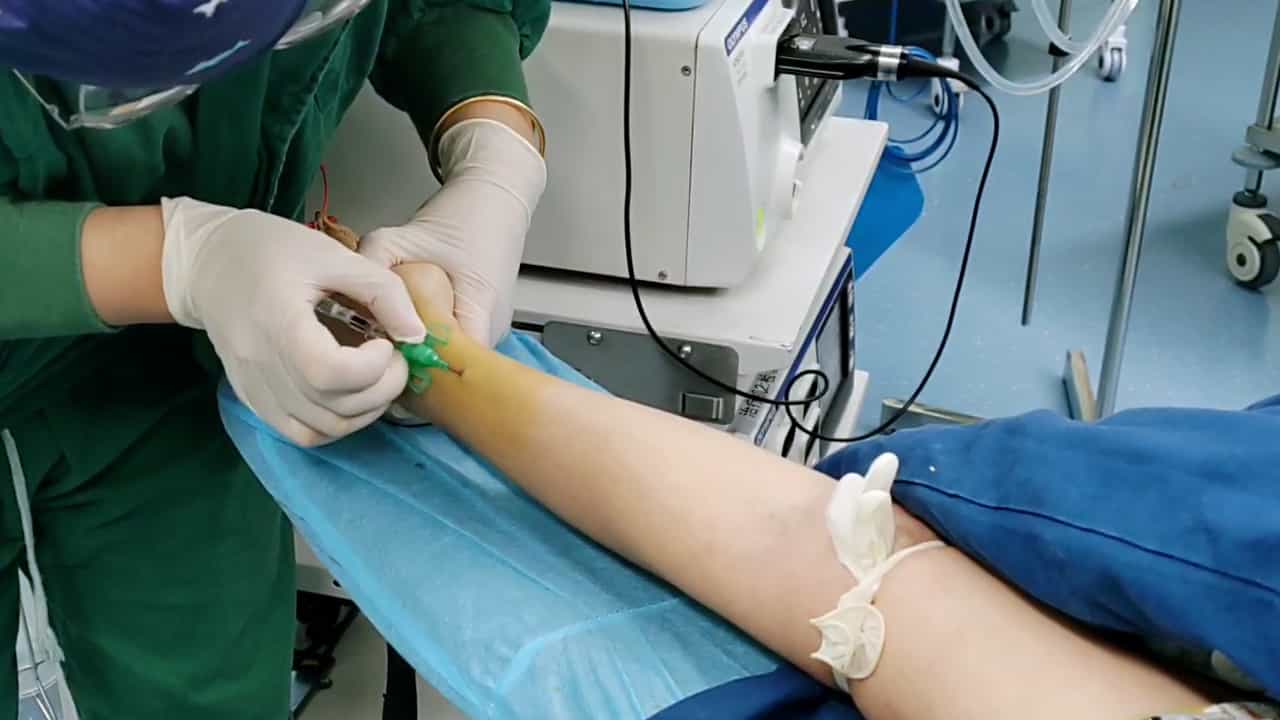

Improved Hysteroscopic Resection of Endometrial Polyps Using 6-Fr Micro-Scissors and Forceps
Published on: August 2, 2024
Endometrial hyperplasia: a review
Ben E Montgomery1, Gary S Daum, Charles J Dunton
1Department of Obstetrics & Gynecology, The Lankenau Hospital, Wynnewood, Pennsylvania, USA. benandtahyia@aol.com

Unlabelled:
Endometrial hyperplasia is a precursor to the most common gynecologic cancer diagnosed in women: endometrial cancer of endometrioid histology. It is most often diagnosed in postmenopausal women, but women at any age with unopposed estrogen from any source are at an increased risk for developing endometrial hyperplasia. Hyperplasia with cytologic atypia represents the greatest risk for progression to endometrial carcinoma and the presence of concomitant carcinoma in women with endometrial hyperplasia. Abnormal uterine bleeding is the most common presenting symptom of endometrial hyperplasia. Specific Pap smear findings and endometrial thickness per ultrasound could also suggest the diagnosis. Unopposed estrogen in women taking hormone replacement therapy increases the risk of endometrial hyperplasia. Tamoxifen has demonstrated its efficacy in treating women at risk for breast cancer, but it increases the risk of endometrial hyperplasia. The choice of treatment for endometrial hyperplasia is dependent on patient age, the presence of cytologic atypia, the desire for future childbearing, and surgical risk. Endometrial hyperplasia without atypia responds well to progestins. However, women with atypical hyperplasia should be treated with hysterectomy unless other factors preclude surgery.
Target Audience:
Obstetricians & Gynecologists, Family Physicians.
Learning Objectives:
After completion of this article, the reader should be able to describe the definition and classification of endometrial hyperplasia, to outline the clinical features of a patient with endometrial hyperplasia, to point out the natural history of endometrial hyperplasia, and to summarize the diagnostic options for patients with endometrial hyperplasia.

Related Concept Videos
 01:26
Cellular Adaptation III: Hyperplasia
 01:24
Cellular Adaptation IV: Dysplasia and Metaplasia
 01:20
Proliferative Phase
Notably, the stratum basale, the basal layer of the endometrium, including the basal parts of the uterine glands, remains unaffected by menstruation. Stem cells in this layer undergo mitosis, regenerating the stratum functionalis and thickening the...
 01:19
Histology of the Uterus
The endometrium is the...
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 02:07
Oogenesis