Related Experiment Video
Updated: Aug 24, 2026
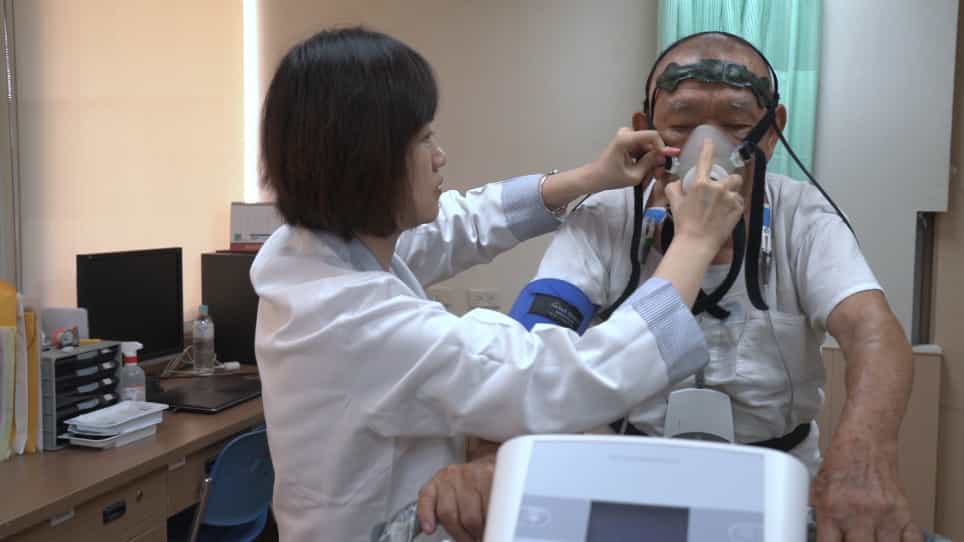

Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Cerebral oxygen extraction and autoregulation during extracorporeal whole body hyperthermia in humans
Olaf L Cremer1, Jan C Diephuis, Hanneke van Soest
1University Medical Center Utrecht E03.511, P. O. Box 85500, 3508 GA Utrecht, The Netherlands. o.l.cremer@azu.nl

Background:
The effects of hyperthermia on the human brain are incompletely understood. This study assessed the effects of whole body hyperthermia on cerebral oxygen extraction and autoregulation in humans.
Methods:
Nineteen patients with chronic hepatitis C virus infection, not responding to interferon treatment, were subjected to experimental therapy with extracorporeal whole body hyperthermia at 41.8 degrees C for 120 min under propofol anesthesia (23 sessions total). During treatment series A (13 sessions), end-tidal carbon dioxide was allowed to increase during heating. During series B (10 sessions), end-tidal carbon dioxide was maintained approximately constant. Cerebral oxygen extraction (arterial to jugular venous difference of oxygen content) and middle cerebral artery blood flow velocity were continuously measured. Cerebral pressure-flow autoregulation was assessed by static tests using phenylephrine infusion and by assessing the transient hyperemic response to carotid compression and release.
Results:
For treatment series A, cerebral oxygen extraction decreased 2.2-fold and cerebral blood flow velocity increased 2.0-fold during heating. For series B, oxygen extraction decreased 1.6-fold and flow velocity increased 1.5-fold. Jugular venous oxygen saturation and lactate measurements did not indicate cerebral ischemia at any temperature. Static autoregulation test results indicated loss of cerebrovascular reactivity during hyperthermia for both series A and series B. The transient hyperemic response ratio did not decrease until the temperature reached approximately 40 degrees C. Per degree Celsius temperature increase, the transient hyperemic response ratio decreased 0.07 (95% confidence interval, 0.05-0.09; P = 0.000). This association remained after adjustment for variations in arterial partial pressure of carbon dioxide, mean arterial pressure, and propofol blood concentration.
Conclusion:
Profound hyperthermia during propofol anesthesia is associated with decreased cerebral oxygen extraction, increased cerebral blood flow velocity, and impaired pressure-flow autoregulation, indicating transient partial vasoparalysis.

Related Concept Videos
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:27
Oxygen Transport in the Blood