Differentiation of posterior myocardial infarction from right ventricular hypertrophy and normal anterior loop by

Insights
Echocardiography effectively differentiates posterobasal myocardial infarction (PMI) from right ventricular hypertrophy (RVH) and normal subjects, outperforming electrocardiography (ECG) and vectorcardiography (VCG). This cardiac imaging method offers practical clinical value for diagnosis.
Area of Science:
- Cardiology
- Medical Imaging
Background:
- Differentiating posterobasal myocardial infarction (PMI) from right ventricular hypertrophy (RVH) or normal anterior loop (AL) subjects is challenging using electrocardiography (ECG) or vectorcardiography (VCG).
- M-mode echocardiography (echo) has shown potential in assessing cardiac chamber size and wall motion abnormalities.
Purpose of the Study:
- To evaluate the efficacy of echocardiography in distinguishing PMI from RVH and AL, comparing its diagnostic accuracy against ECG and VCG.
- To determine if echocardiography provides a more direct and accurate method for differentiating these cardiac conditions.
Main Methods:
- Comparison of ECG, VCG, and M-mode echocardiography (anterior and subxiphoid approaches) in differentiating PMI, RVH, and AL groups.
- Analysis of cardiac chamber dimensions, wall thickness, and systolic thickening response using echocardiography.
- Assessment of posterior wall motion specificity using the subxiphoid echocardiographic view.
Main Results:
- ECG and VCG failed to effectively distinguish between the three cardiac conditions.
- Echocardiography revealed distinct characteristics: RVH showed increased right ventricular dimensions and wall thickness; AL subjects had normal echo findings; PMI demonstrated reduced posterior left ventricular systolic thickening and ejection indices via the subxiphoid method.
- The subxiphoid echocardiographic view targets a superior posterobasal left ventricular segment, aiding in PMI differentiation.
Conclusions:
- Echocardiography, particularly the subxiphoid approach, offers a more direct and clinically significant method for differentiating PMI from RVH and AL compared to ECG or VCG.
- This imaging technique enhances diagnostic capabilities in complex cardiac cases involving myocardial infarction and hypertrophy.
Abstract:
The differentiation of posterobasal myocardial infarction (PMI) from either right ventricular hypertrophy (RVH) or normal subjects displaying an anterior loop (AL) by electrocardiography (ECG) or vectorcardiography (VCG) is difficult. M-mode echocardiography (echo) via the anterior and subxiphoid methods has been helpful in defining cardiac chamber size and wall motion abnormalities. We tested whether this relatively more direct method would better separate these entities compared with the other two techniques. ECG and VCG using established criteria failed to distinguish the three conditions effectively. By echo, distinguishing characteristics were observed in each of the groups. Thus, right ventricular diastolic dimension and wall thickness were significantly increased only in the RVH group, echo dimensions and wall motion were normal in the AL group and the posterior left ventricular systolic thickening response and ejection phase indices were significantly reduced only by the subxiphoid method in the PMI group. To test the specificity of the latter finding, posterior wall motion in three infarction groups (posterior, combined posteroinferior and inferior) were examined and suggested that the target of the subxiphoid beam focuses on a more superior posterobasal left ventricular segment than the anteriorly placed transducer. Echocardiography can differentiate PMI from either RVH or AL more directly than ECG or VCG, and may be of practical clinical importance.


Related Concept Videos
 01:13
The Cardiac Cycle
The Process
Electrical signals—sent from the sinoatrial (SA) node in the right atrial wall to the atrioventricular (AV) node between the right atrium and right ventricle—cause both atria to simultaneously contract. When the signal reaches the AV node, it pauses for approximately a tenth of a second, allowing the atria to contract and empty blood into the...
 01:16
Chambers of the Heart
Deoxygenated blood from the body is received in the right...
 01:16
Heart Valves
The AV valves prevent the backflow of blood from the ventricles to the atria during ventricular contraction. These valves function with the assistance of the chordae tendineae and papillary muscles. When the ventricles are relaxed, the chordae tendineae are slack, allowing blood to flow from the atria into the...
 01:15
Heart Sounds
Auscultation is the process of listening to these internal body sounds using a stethoscope. The heart produces four types of sounds, but only two—S1 and S2—can usually be heard with a stethoscope.
S1, also known as the "lub" sound, is caused by the closure of atrioventricular (A-V) valves at the...
 01:25
Assessment of the Cardiovascular System IV: Auscultation
Normal Heart Sounds
S1 (First Heart Sound)-
S1 is made by the closure of the mitral and tricuspid valves (atrioventricular valves), marking the beginning of systole.
S2 (Second Heart Sound)-
S2 is made by the closure of the aortic and pulmonic valves (semilunar valves), marking the end of the systole.
 01:25
Cardiovascular System Abnormal Findings II: Auscultation
Abnormal Heart Sounds
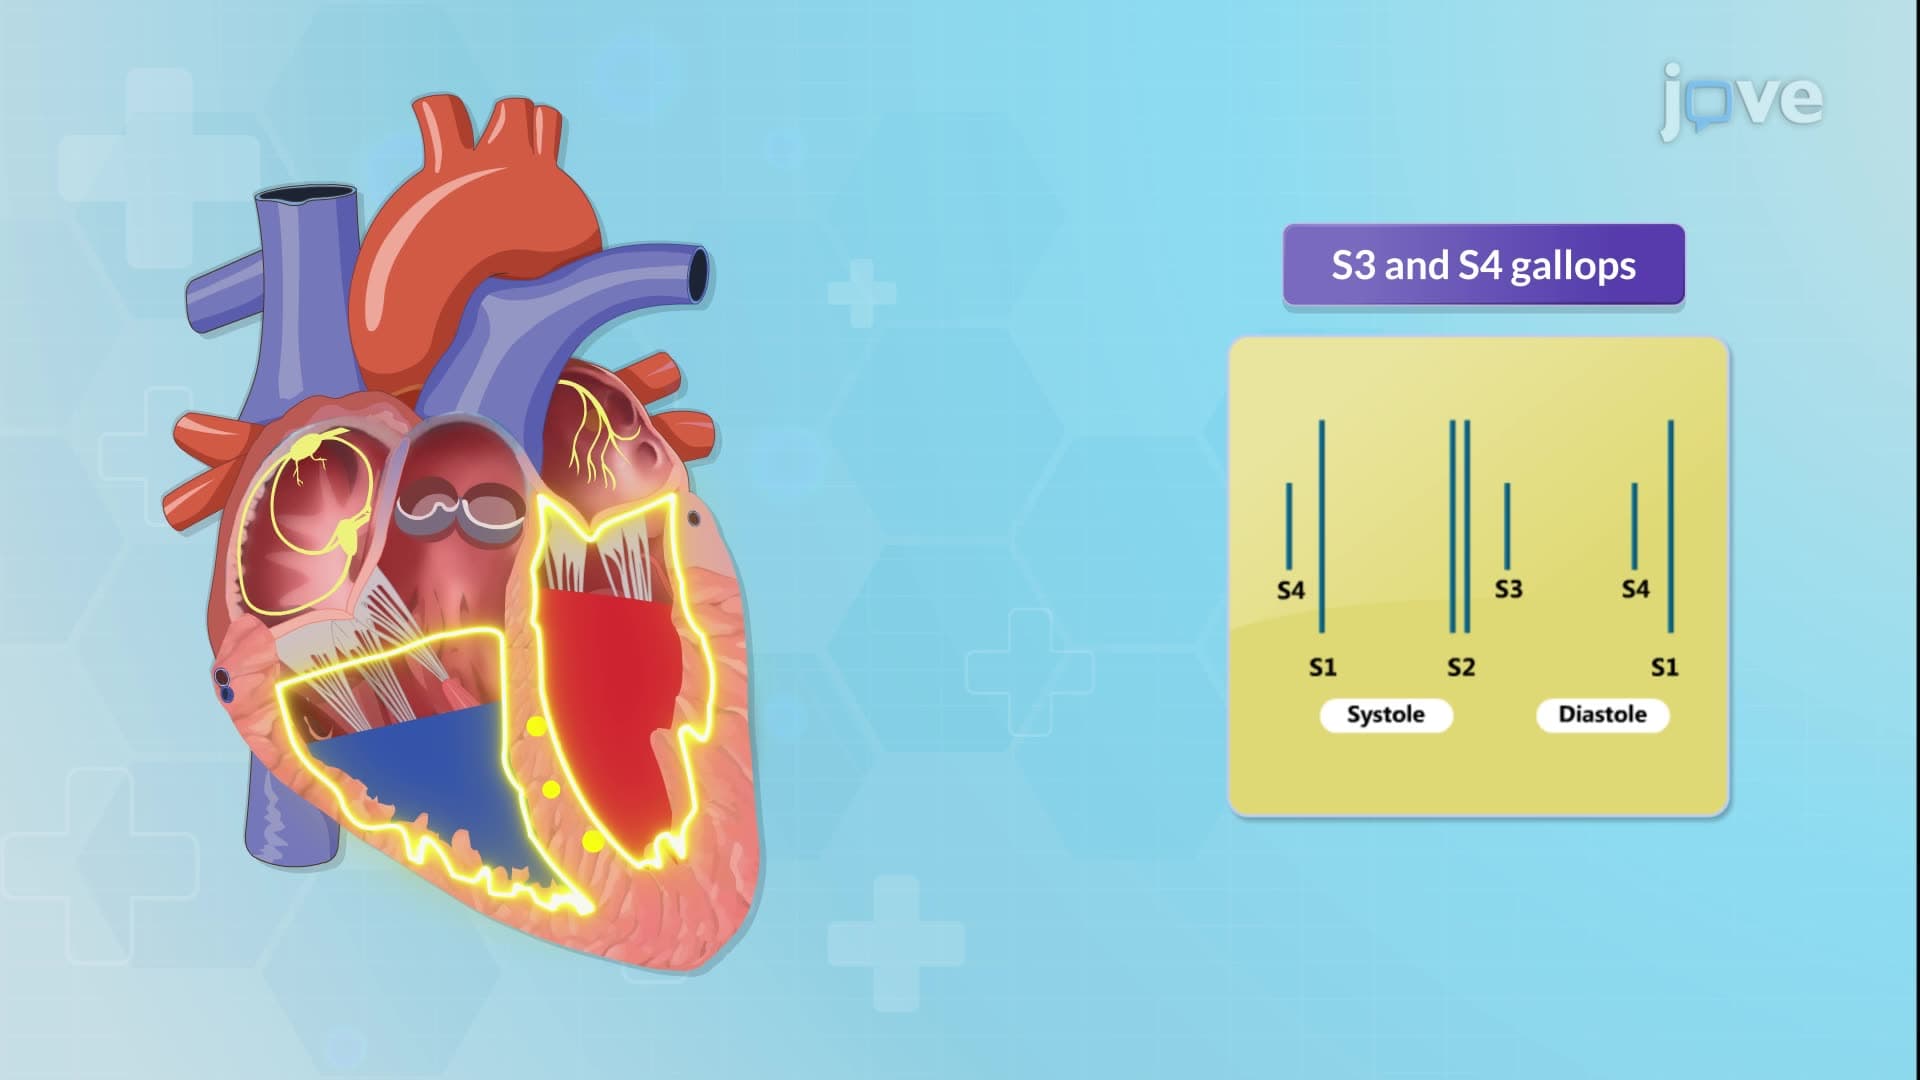
Gallops: