Related Experiment Video
Updated: Aug 23, 2026
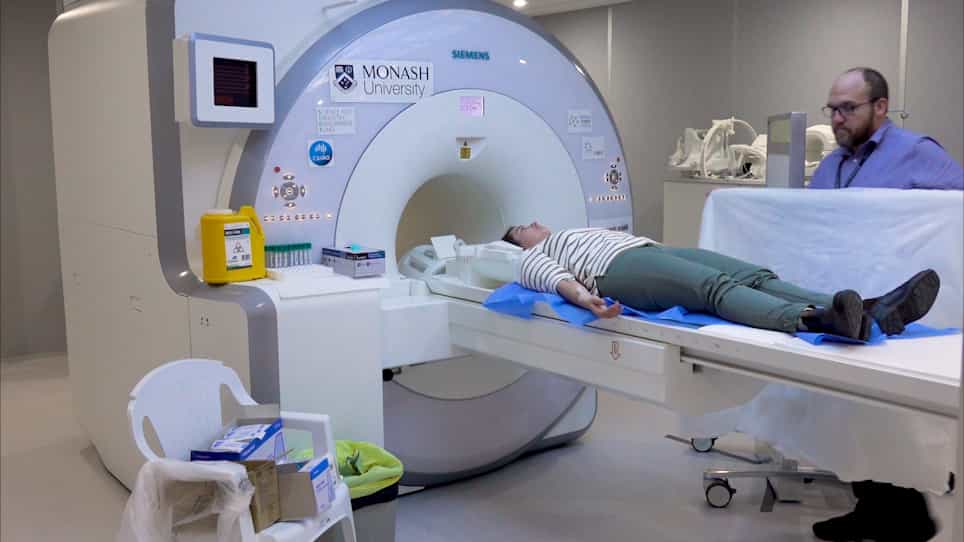

Radiotracer Administration for High Temporal Resolution Positron Emission Tomography of the Human Brain: Application to FDG-fPET
Published on: October 22, 2019
Task-specific monitoring of nuclear medicine technologists' radiation exposure
1Department of Nuclear Medicine, St George Hospital, Kogarah, NSW 2217, Australia. r.smart@unsw.edu.au

Abstract:
Many studies have demonstrated that the exposure of nuclear medicine technologists arises primarily from radioactive patients rather than from preparation of radiopharmaceuticals. However, in order to devise strategies to reduce staff exposure, it is necessary to identify the specific tasks within each procedure that result in the highest radiation doses. An ESM Eberline FH41B-10 radiation dosemeter, which records the ambient dose equivalent rate, was used to monitor the radiation exposure of a technologist and to record the dose rate in microSv per hour every 32 s throughout a working day. The technologist recorded the procedures that were being performed so that the procedures that resulted in higher doses could be identified clearly. The measured doses clearly showed that the major contributions to the technologist's dose were the following: (1) transferring incapacitated patients from the imaging table to a hospital trolley; (2) difficult injections without syringe shields; and (3) setting up patients for gated myocardial scans. The average dose to the technologist from transferring patients after a bone scan was 0.54 microSv, 40% of the total dose of 1.3 microSv for the complete bone scan procedure. The average dose received injecting 900 MBq of 99Tcm-HDP using a tungsten syringe shield was 0.57microSv, but the highest dose was 1.6 microSv, in a patient in whom the injection was difficult. A 0.5 mm lead apron was found to reduce the dose when setting up a patient for a gated stress 99Tcm-sestamibi myocardial scan by approximately a factor of 2. The average dose per patient for this task was reduced from 1.1 to 0.6 microSv. It is recommended that staff waiting for assistance with patient transfers stand away from the patient, that tungsten syringe shields be used for all radiopharmaceutical injections and that a 0.5 mm lead apron be worn when attending patients containing high activities of 99Tcm radiopharmaceuticals, such as those having myocardial imaging.
Related Concept Videos
 01:13
Radiological Investigation III: Pulmonary Angiogram and PET Scan
Pulmonary Angiogram
A Pulmonary Angiogram is an invasive procedure involving injecting a contrast medium through a catheter threaded into the pulmonary artery or the right side of the heart to visualize the pulmonary vasculature. Computed Tomography (CT) scans have mainly replaced this...
 01:25
Imaging Studies II: Positron Emission Tomography and Scintigraphy
Fundamental Principles of PET
 01:29
Positron Emission Tomography
One of the main requirements of a PET scan is a positron-emitting radioisotope, which is produced in a cyclotron and then attached to a substance used by the part of the body being...
 01:30
Radiological Investigation I: X-ray and CT
 02:59
Biological Effects of Radiation
 01:30
Radiological Investigation II: MRI and Ventilation Perfusion Scan
Magnetic Resonance Imaging (MRI) and Ventilation Perfusion Scans are two radiological investigations that offer detailed diagnostic images of the body, particularly lung structures.
MRI
MRI uses magnetic fields and radiofrequency signals to distinguish between normal and abnormal tissues. This technology provides a more detailed diagnostic image than CT scans, enabling it to characterize pulmonary nodules, stage bronchogenic carcinoma, and evaluate inflammatory activity in...