Related Experiment Video
Updated: Aug 23, 2026


Optimized Management of Endovascular Treatment for Acute Ischemic Stroke
Published on: January 18, 2018
Anticoagulants for acute ischaemic stroke

Insights
Early anticoagulant therapy for acute ischaemic stroke does not improve patient survival or reduce disability. While it may decrease recurrent strokes and blood clots like pulmonary embolism, it increases risks of bleeding, showing no overall net benefit.
Area of Science:
- Neurology
- Cardiovascular Medicine
- Pharmacology
Background:
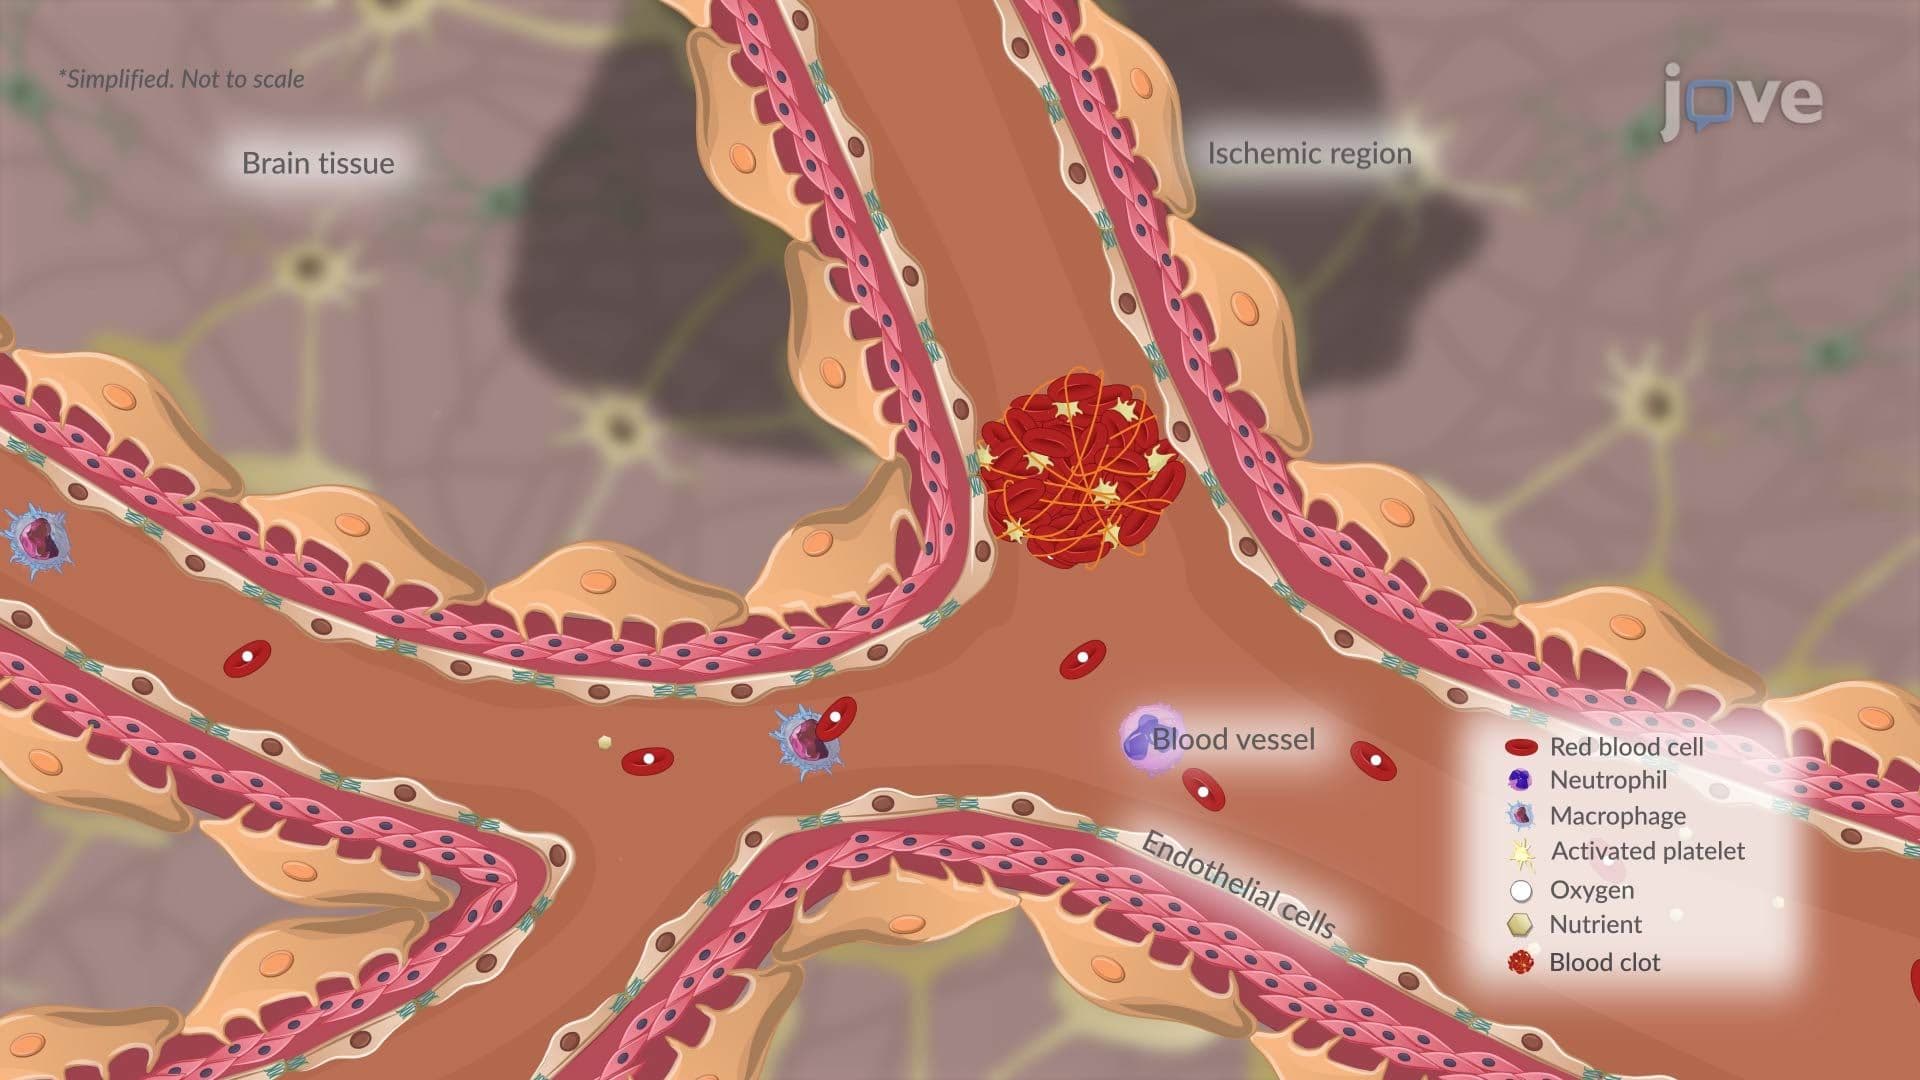
- Ischaemic strokes are primarily caused by cerebral artery blood clots.
- Anticoagulant therapy is a potential strategy for preventing clot formation, impacting stroke survival and recurrence.
Purpose of the Study:
- To evaluate the efficacy of early anticoagulant therapy versus control in acute ischaemic stroke patients.
- To assess the net benefit of anticoagulants considering both positive and negative clinical outcomes.
Main Methods:
- Systematic review of randomized controlled trials comparing early anticoagulant therapy (within two weeks of stroke onset) with control.
- Searched Cochrane Stroke Group trials register and consulted relevant databases and drug companies.
- Independent selection, quality assessment, and data extraction by two reviewers.
Main Results:
- Twenty-two trials with 23,547 patients were analyzed; trial quality varied.
- No evidence found that anticoagulants reduced all-cause mortality or death/dependency at follow-up.
- Anticoagulants reduced recurrent ischaemic strokes and pulmonary emboli but increased symptomatic intracranial and major extracranial haemorrhages, with no net benefit identified.
Conclusions:
- Early anticoagulant therapy in acute ischaemic stroke offers no significant short- or long-term net benefit.
- Current data do not support the routine use of any anticoagulant for acute ischaemic stroke.
- While anticoagulants reduce deep vein thrombosis and pulmonary embolism risk, these benefits are outweighed by increased bleeding risks and may be managed through alternative methods.
Background:
Most ischaemic strokes are caused by blood clots blocking an artery in the brain. Clot prevention with anticoagulant therapy could have a significant impact on patient survival, disability and stroke recurrence.
Objectives:
The objective of this review was to assess the effect of anticoagulant therapy versus control in the early treatment of patients with acute ischaemic stroke.
Search Strategy:
We searched the Cochrane Stroke Group trials register (last searched 30 October 2003). For previous updates of this review, we searched the register of the Antithrombotic Trialists' (ATT) Collaboration, consulted MedStrategy (1995), and contacted relevant drug companies.
Selection Criteria:
Randomised trials comparing early anticoagulant therapy (started within two weeks of stroke onset) with control in patients with acute presumed or confirmed ischaemic stroke.
Data Collection And Analysis:
Two reviewers independently selected trials for inclusion, assessed trial quality and extracted the data.
Main Results:
Twenty-two trials involving 23,547 patients were included. The quality of the trials varied considerably. The anticoagulants tested were standard unfractionated heparin, low-molecular-weight heparins, heparinoids, oral anticoagulants, and thrombin inhibitors. Based on nine trials (22,570 patients) there was no evidence that anticoagulant therapy reduced the odds of death from all causes (odds ratio (OR) = 1.05, 95% confidence interval (CI) 0.98 to 1.12) at the end of follow-up. Similarly, based on six trials (21,966 patients), there was no evidence that anticoagulants reduced the odds of being dead or dependent at the end of follow-up (OR = 0.99; 95% CI 0.93 to 1.04). Although anticoagulant therapy was associated with about 9 fewer recurrent ischaemic strokes per 1000 patients treated (OR = 0.76; 95% CI 0.65 to 0.88), it was also associated with a similar sized 9 per 1000 increase in symptomatic intracranial haemorrhages (OR = 2.52; 95% CI 1.92 to 3.30). Similarly, anticoagulants avoided about 4 pulmonary emboli per 1000 (OR = 0.60, 95% CI 0.44 to 0.81), but this benefit was offset by an extra 9 major extracranial haemorrhages per 1000 (OR = 2.99; 95% CI 2.24 to 3.99). Sensitivity analyses did not identify a particular type of anticoagulant regimen or patient characteristic associated with net benefit.
Reviewers' Conclusions:
Immediate anticoagulant therapy in patients with acute ischaemic stroke is not associated with net short- or long-term benefit. The data from this review do not support the routine use of any type of anticoagulant in acute ischaemic stroke. People treated with anticoagulants had less chance of developing deep vein thrombosis (DVT) and pulmonary embolism (PE) following their stroke, but these sorts of blood clots are not very common, and may be prevented in other ways.
Related Concept Videos
 01:18
Anticoagulant Drugs: Vitamin K Antagonists and Direct Oral Anticoagulants
Warfarin, a prominent vitamin K antagonist family member, exerts its effect by inhibiting the enzyme VKORC1 (vitamin K epoxide reductase complex 1). By hindering this enzyme, warfarin...
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:29
Venous Thrombosis III: Interprofessional Care
 01:15
Ischemic Stroke l: Introduction
 01:20
Antiplatelet Drugs: Prostaglandin Synthesis, P2Y12 and Glycoprotein IIb/IIIa Inhibitors
Prostaglandin synthesis inhibitors, exemplified by the widely known aspirin, wield their power by irreversibly acetylating...
 01:26
Transient Ischemic Attack l: Introduction