Related Experiment Video
Updated: Aug 23, 2026

Assessing Insulin Clearance in Mice via In Situ Liver Perfusion
Published on: December 13, 2024
Insulin treatment improves hepatic morphology and function through modulation of hepatic signals after severe trauma
Dagmar Klein1, Thomas Schubert, Raymund E Horch
1Klinik und Poliklinik für Chirurgie, Klinikum der Universität Regensburg, Germany.

Objective:
The purpose of the present study was to determine the effect of insulin therapy on hepatic function, structure, and hepatic mRNA and protein cytokine expression during the hypermetabolic cascade post burn.
Summary Background Data:
Liver function and morphology are crucial for survival of patients suffering from trauma, operations, or infections. Insulin decreased mortality and prevented the incidence of multiorgan failure in critically ill patients.
Methods:
Rats received a thermal injury and were randomly divided into the insulin or control group. Our outcome measures encompassed the effect of insulin on hepatic proteins, hepatic pro- and anti-inflammatory cytokines mRNA and proteins, hepatocyte proliferation, including Bcl-2 and hepatocyte apoptosis, with caspases-3 and caspases-9.
Results:
Insulin significantly improved hepatic protein synthesis by increasing albumin and decreasing c-reactive protein and fat (P < 0.05). Insulin decreased the hepatic inflammatory response signal cascade by decreasing hepatic pro-inflammatory cytokines mRNA and proteins IL-1beta and tumor necrosis factor at pretranslational levels. Insulin increased hepatic cytokine mRNA and protein expression of IL-2 and IL-10 at a pretranslational level when compared with controls (P < 0.05). Insulin increased hepatocyte proliferation along with Bcl-2 concentration, while decreasing hepatocyte apoptosis along with decreased caspases-3 and -9 concentration, thus improving liver morphology (P < 0.05).
Conclusions:
Our data provide insight that insulin attenuates the inflammatory response by decreasing the pro-inflammatory and increasing the anti-inflammatory cascade, thus restoring hepatic homeostasis, which has been shown to be critical for organ function and survival of critically ill patients.


Related Concept Videos
 01:28
Insulin: The Receptor and Signaling Pathways
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:25
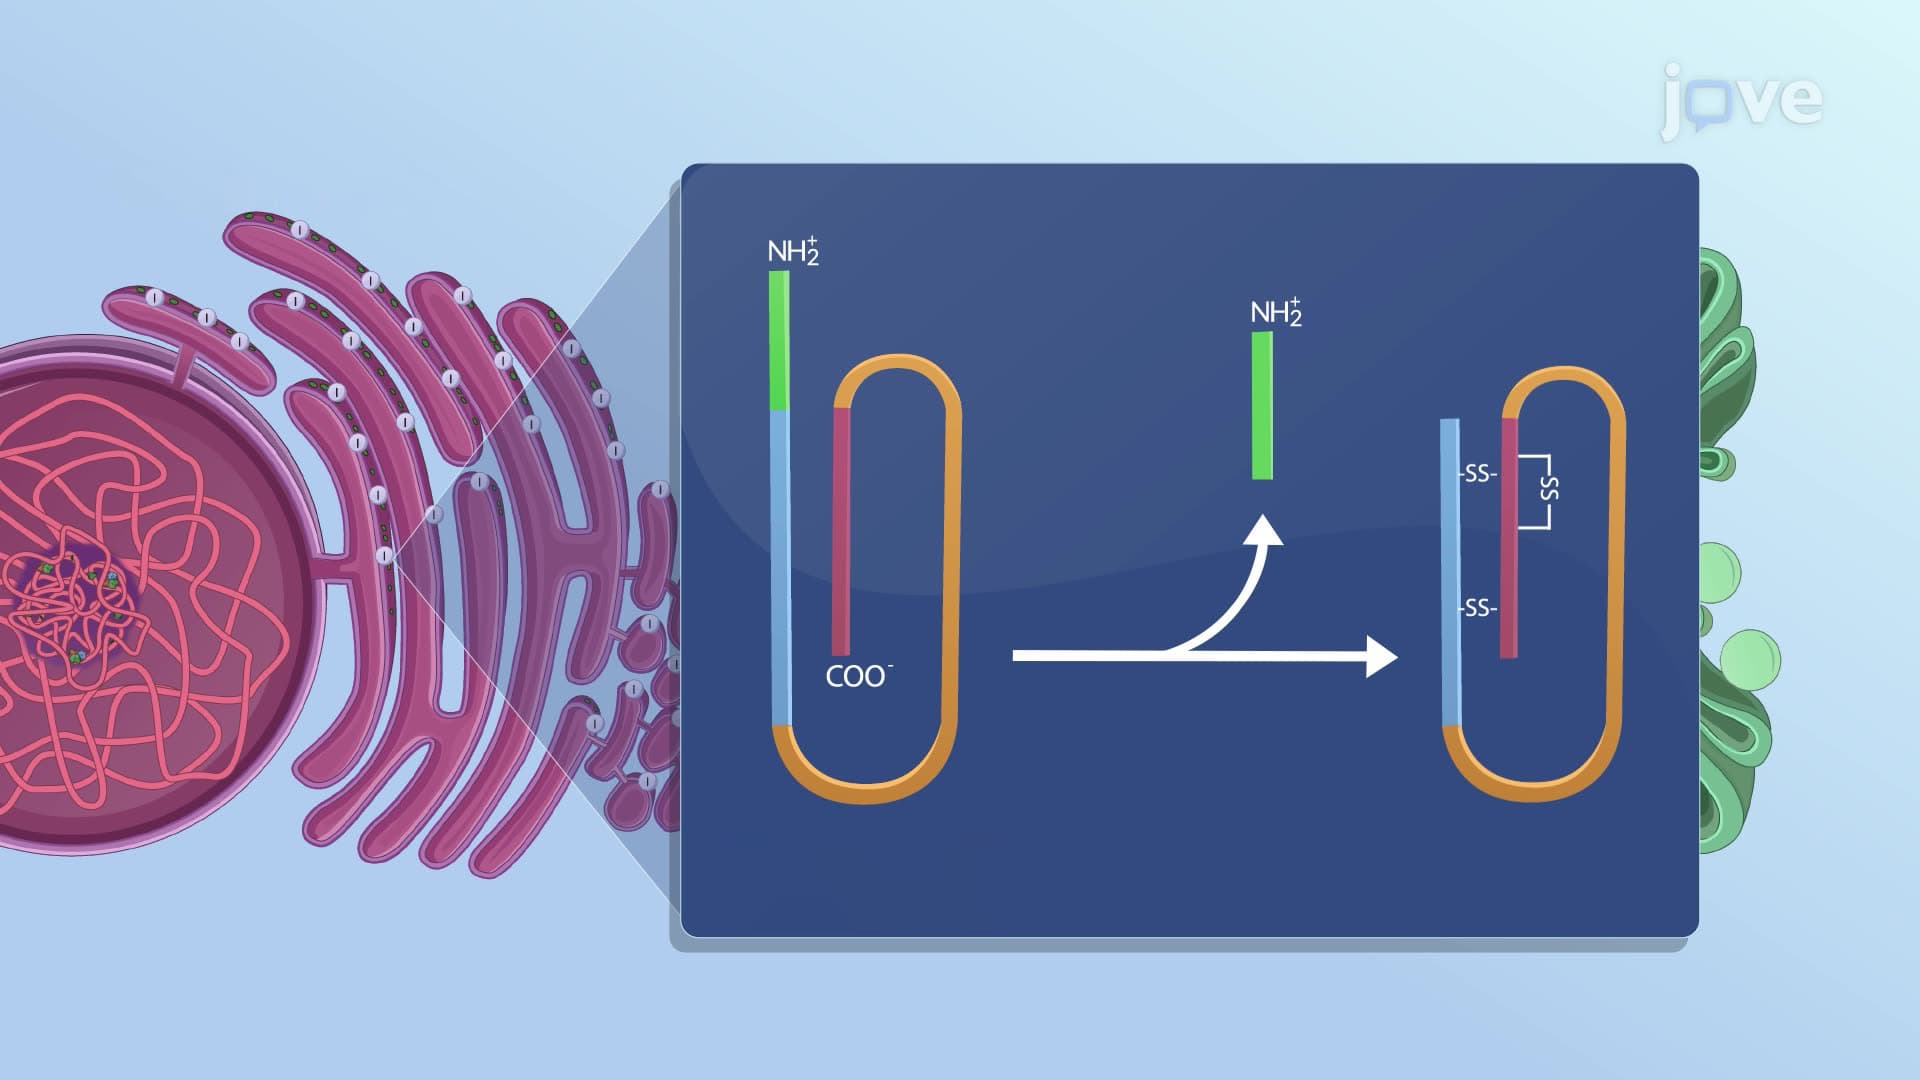
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:24
Type II Diabetes II: Pathophysiology
 01:24
Liver Regeneration
Cells of Liver
The liver comprises four major types of cells— hepatocytes, stellate, Kupffer, and sinusoidal endothelial cells. The hepatocytes are large...
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are co-secreted in...