Related Experiment Video
Updated: Aug 23, 2026

Rapid Screening of HIV Reverse Transcriptase and Integrase Inhibitors
Published on: April 9, 2014
Initiation of antiretroviral therapy: implications of recent findings
1University of Alabama at Birmingham, Birmingham, Alabama, USA.

Abstract:
A number of reports related to initiation of antiretroviral therapy have been reported recently. Available data continue to support the practice of not starting therapy for asymptomatic patients who have CD4+ cell counts above 350/mL, and consideration for initiating antiretroviral therapy below this point, but before the count drops to 200/mL. In terms of initial regimens, some data suggest better virologic response rates with nonnucleoside reverse transcriptase inhibitors (NNRTI)-based regimens than with protease inhibitor-based regimens. The differences are likely due to better tolerability of NNRTI-based regimens. Small studies in treatment-naive patients have shown poor virologic outcome in patients receiving certain regimens, such as abacavir/lamivudine/tenofovir or didanosine/lamivudine/tenofovir. These findings appear to be explained by the differing effects of the reverse transcriptase K65R mutation on different drugs. Other recent studies suggest fewer metabolic adverse effects with emtricitabine-containing treatment than with stavudine-containing treatment, comparable virologic outcomes with once-daily and twice-daily abacavir regimens; comparable virologic outcomes with once-daily and twice-daily lopinavir/ritonavir regimens, and an association between didanosine 400 mg/tenofovir regimens and declines in CD4+ cell counts despite viral suppression. This article summarizes a presentation on initiation of antiretroviral therapy by Michael S. Saag, MD, at International AIDS Society-UsA course in New York in March 2004.
Related Concept Videos
 01:10
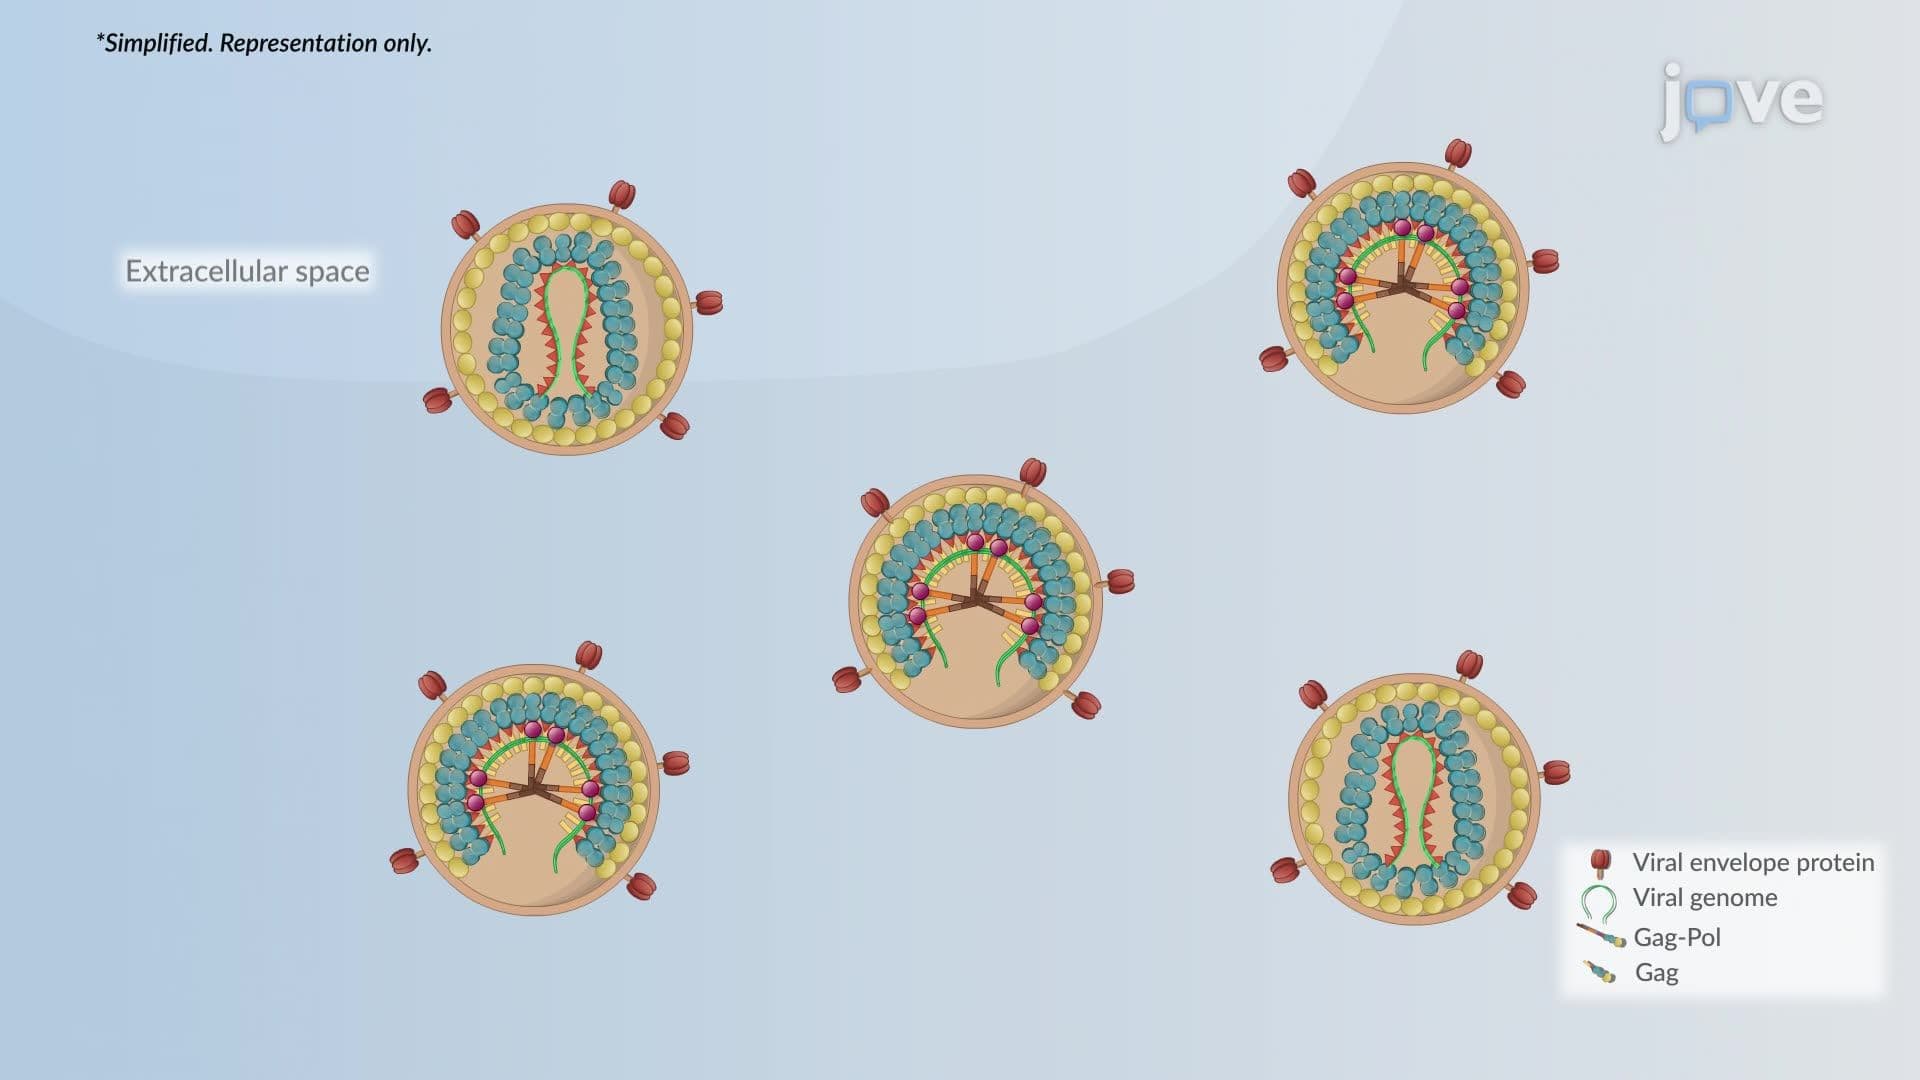
Retrovirus Life Cycles
 01:19
Inhibitors of Virion Maturation and Assembly
 01:30
Inhibitors of Viral Protein Synthesis
 01:22
Antiviral Nucleoside Inhibitors