Related Experiment Video
Updated: Aug 22, 2026
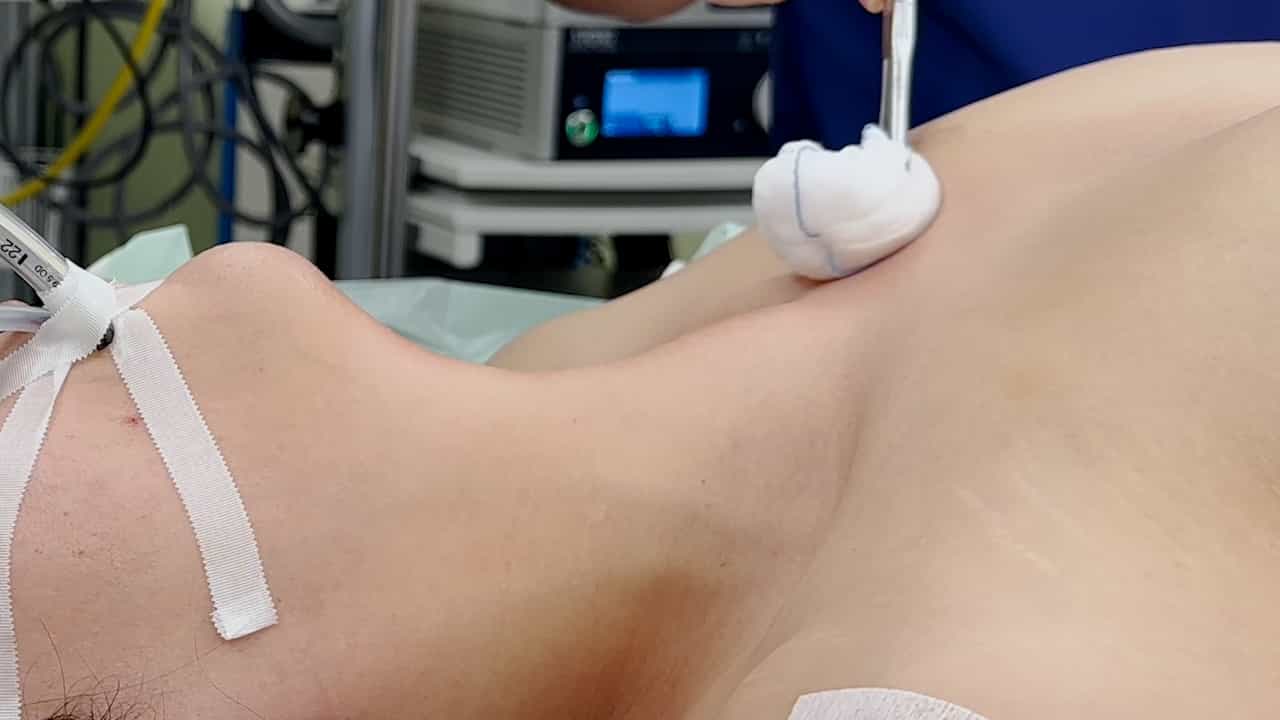

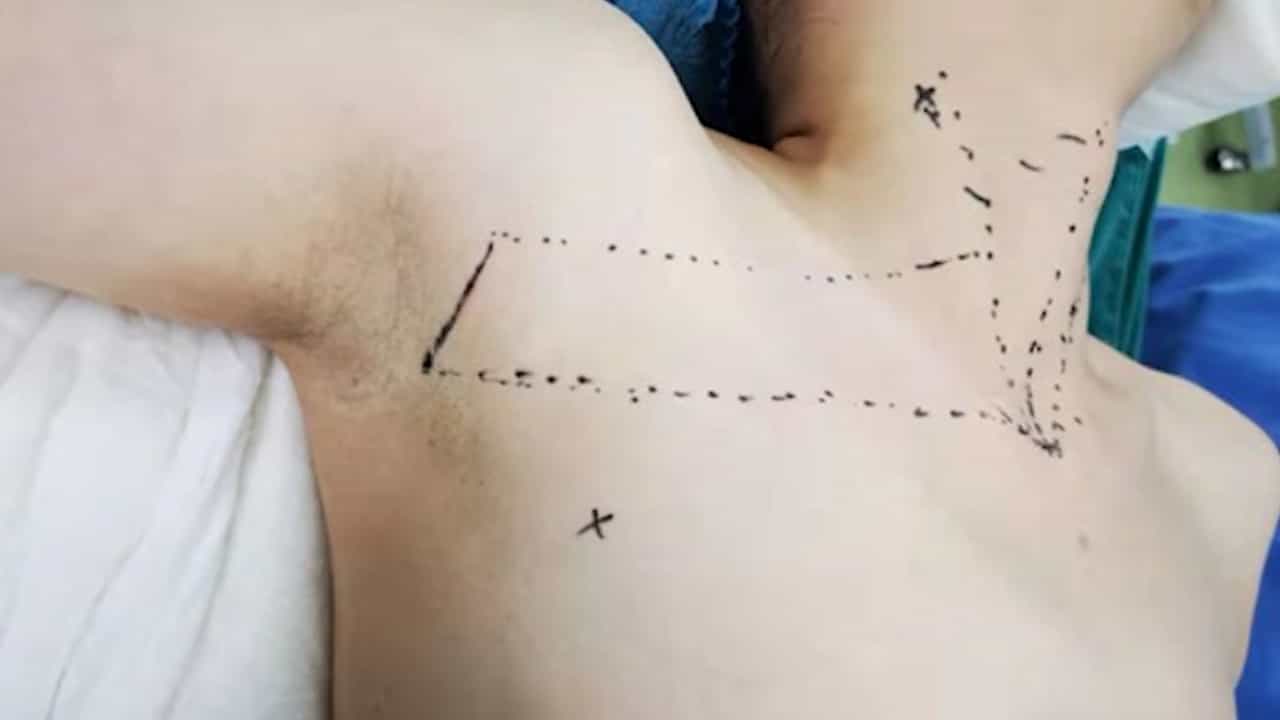
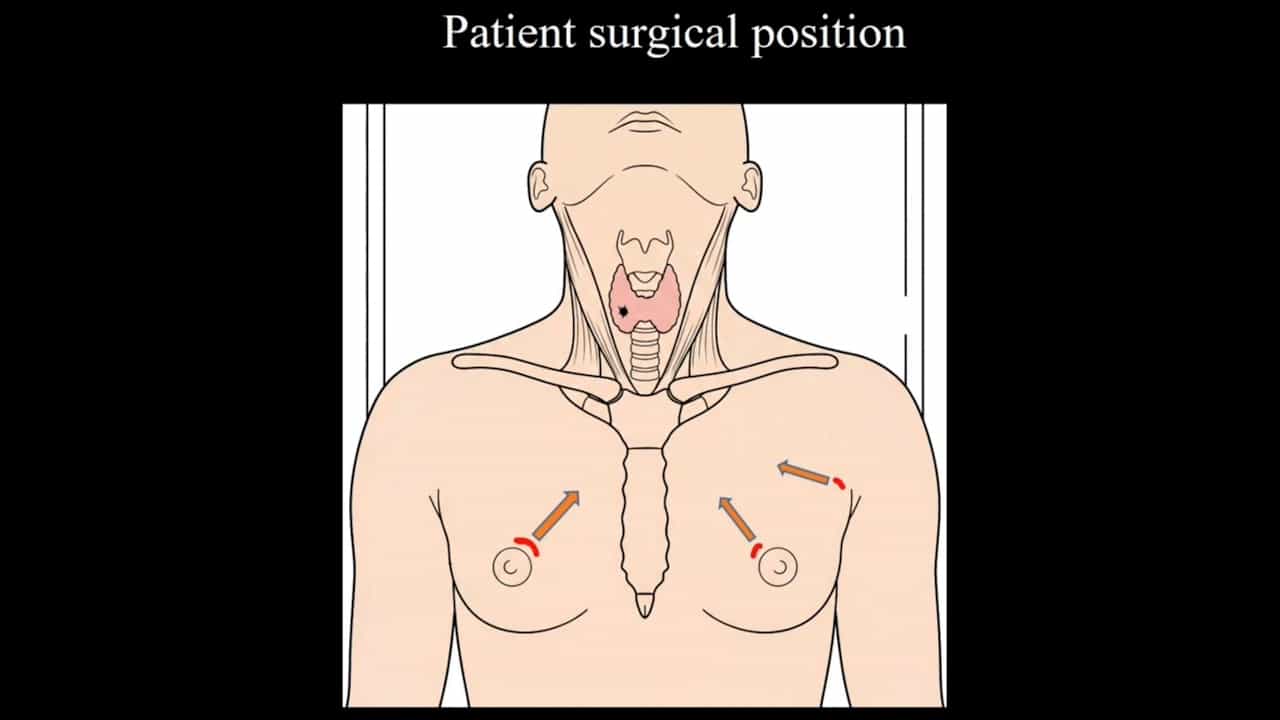
Minimal Invasive Resection of Large Retrosternal Thyroid Goiter
Published on: September 20, 2024
Report of an obstructive goiter and its surgical treatment during delivery
Todd W Preston1, Wha-Joon Lee, Brendan C Stack
1Division of Otolarygnology-Head and Neck Surgery, Penn State University, Milton S. Hershey Medical Center, Hershey, PA 17033, USA.

We report a case of a morbidly obese young woman in her third trimester of pregnancy presenting with a history of goiter and respiratory disease. The recent history of this patient was significant for worsening respiratory symptoms over a period of 2 weeks, and, on presentation at 36 weeks gestation, she was stridorous, dyspneic at rest, and had a hoarse voice. Evaluation revealed a morbidly obese individual with a large goiter. She was biochemically euthyroid. Fiberoptic laryngoscopy revealed a left true vocal cord paresis, and ultrasound evaluation was significant for diffuse multinodular enlargement, with each lobe measuring greater than 10 cm and the isthmus measuring 5. Pulmonary function testing revealed a significant degree of upper airway obstruction without significant lower airway disease. Given the patient's clinical signs and symptoms, her tenuous airway, poor candidacy for urgent tracheotomy, and her proximity to delivery, it was agreed that the patient should undergo elective cesarean section and at its completion undergo subtotal thyroidectomy for the obstructive goiter.
We report a case of a morbidly obese young woman in her third trimester of pregnancy presenting with a history of goiter and respiratory disease. The recent history of this patient was significant for worsening respiratory symptoms over a period of 2 weeks, and, on presentation at 36 weeks gestation, she was stridorous, dyspneic at rest, and had a hoarse voice. Evaluation revealed a morbidly obese individual with a large goiter. She was biochemically euthyroid. Fiberoptic laryngoscopy revealed a left true vocal cord paresis, and ultrasound evaluation was significant for diffuse multinodular enlargement, with each lobe measuring greater than 10 cm and the isthmus measuring 5. Pulmonary function testing revealed a significant degree of upper airway obstruction without significant lower airway disease. Given the patient's clinical signs and symptoms, her tenuous airway, poor candidacy for urgent tracheotomy, and her proximity to delivery, it was agreed that the patient should undergo elective cesarean section and at its completion undergo subtotal thyroidectomy for the obstructive goiter.
Related Concept Videos
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...