Related Experiment Video
Updated: Aug 22, 2026
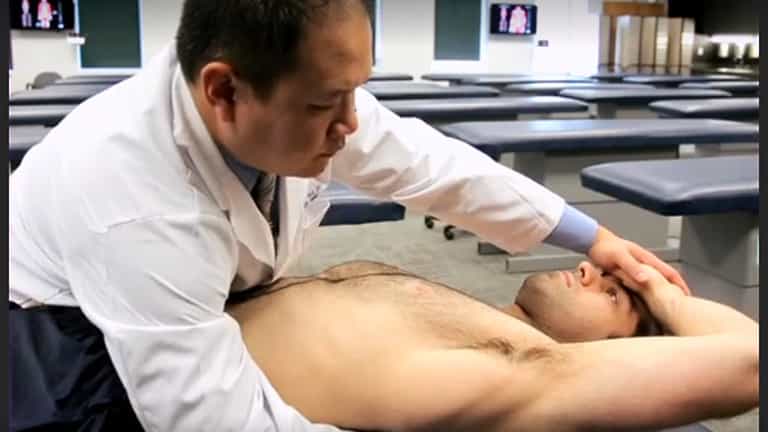

Osteopathic Manipulative Treatment as a Useful Adjunctive Tool for Pneumonia
Published on: May 6, 2014
Chest wall kinematics and respiratory muscle action in ankylosing spondylitis patients
I Romagnoli1, F Gigliotti, A Galarducci
1Don C. Gnocchi Foundation, Section of Respiratory Rehabilitation, Pozzolatico, Florence, Italy.

Abstract:
No direct measurements of the pressures produced by the ribcage muscles, the diaphragm and the abdominal muscles during hyperventilation have been reported in patients with ankylosing spondylitis. Based on recent evidence indicating that abdominal muscles are important contributors to stimulation of ventilation, it was hypothesised that, in ankylosing spondylitis patients with limited ribcage expansion, a respiratory centre strategy to help the diaphragm function may involve coordinated action of this muscle with abdominal muscles. In order to validate this hypothesis, the chest wall response to a hypercapnic/hyperoxic rebreathing test was assessed in six ankylosing spondylitis patients and seven controls by combined analysis of: 1) chest wall kinematics, using optoelectronic plethysmography, this system is accurate in partitioning chest wall expansion into the contributions of the ribcage and the abdomen; and 2) respiratory muscle pressures, oesophageal, gastric and transdiaphragmatic (Pdi); the pressure/volume relaxation characteristics of both the ribcage and the abdomen allowed assessment of the peak pressure of both inspiratory and expiratory ribcage muscles, and of the abdominal muscles. During rebreathing, chest wall expansion increased to a similar extent in patients to that in controls; however, the abdominal component increased more and the ribcage component less in patients. Peak inspiratory ribcage, but not abdominal, muscle pressure was significantly lower in patients than in controls. End-inspiratory Pdi increased similarly in both groups, whereas inspiratory swings in Pdi increased significantly only in patients. No pressure or volume signals correlated with disease severity. The diaphragm and abdominal muscles help to expand the chest wall in ankylosing spondylitis patients, regardless of the severity of their disease. This finding supports the starting hypothesis that a coordinated response of respiratory muscle activity optimises the efficiency of the thoracoabdominal compartment in conditions of limited ribcage expansion.
Related Concept Videos
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration can...
 01:25
Muscles of the Thorax
The diaphragm is at the core of thoracic musculature, the primary muscle involved in breathing. This expansive, dome-shaped muscle marks the division between the thoracic and abdominal cavities. It originates...
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like asthma or COPD,...
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:31
Respiratory System Abnormal Finding II: Palpation and Auscultation
Palpation Findings
During a respiratory assessment, palpation can reveal several vital abnormalities: