Blood glucose control during selective arterial stimulation and venous sampling for localization of focal hyperinsulinism lesions in anesthetized children
Related Experiment Video
Updated: Jun 29, 2026
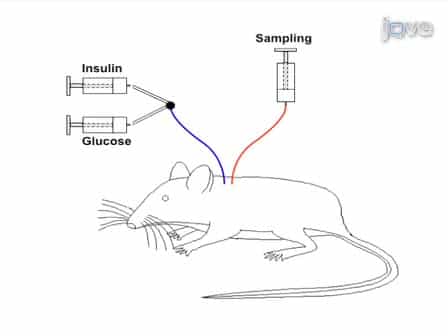
Hyperinsulinemic-Euglycemic Clamp in the Conscious Rat
Published on: February 8, 2011
Giovanni Cucchiaro1, Scott D Markowitz, Robin Kaye
1From The Children's Hospital of Philadelphia, University of Pennsylvania, Philadelphia, Pennsylvania.

Abstract:
Surgical management of congenital hyperinsulinism is improved by accurate localization of small, focal dysregulated pancreatic lesions using the arterial stimulation and venous sampling (ASVS) test, which can demonstrate increased hepatic venous insulin concentrations after selective arterial injections of calcium. However, anesthesia-related increases in blood glucose can induce insulin secretion, making it difficult to interpret ASVS test data. In this retrospective study, we examined the effect of anesthetic interventions on blood glucose concentrations in 68 children undergoing ASVS testing. We considered only the glucose concentrations observed before calcium stimulation in the final analysis. The choice of drugs for induction (sevoflurane, propofol, or thiopentone), maintenance inhaled anesthetics (sevoflurane, desflurane, or isoflurane), and the use of caudal epidural bupivacaine were not associated with significant differences in the mean blood glucose concentration before ASVS. However, patients receiving remifentanil infusions had smaller mean glucose concentrations (80 +/- 18 versus 100 +/- 44 mg x dl(-1), P = 0.01). These concentrations were also significantly smaller if tracheal intubation was delayed for at least 10 min after induction while patients received inhaled anesthetics via a face mask along with remifentanil infusions (79 +/- 14 for delayed intubation versus 95 +/- 39 mg x dl(-1) for early intubation, respectively, P = 0.03). The percentage increase in glucose concentrations from preintubation values was significantly smaller in these subjects (3.7% +/- 21.9% for delayed intubation versus 31.7% +/- 60.4% for early intubation, P = 0.02). We conclude that the anesthetic management protocol for these patients should include the use of remifentanil infusions and the administration of inhaled anesthetics and remifentanil infusions for a minimum of 10 min to establish a deep plane of anesthesia before tracheal intubation.

Related Concept Videos
 01:16
Hormones Regulating Blood Glucose
In addition to accelerating glucose uptake and utilization, insulin has...
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are co-secreted in...
 01:15
Hypoglycemia and Glucagon
 01:26
Hypoglycemia
 01:29
Hyperglycemia