Related Experiment Video
Updated: Aug 15, 2026
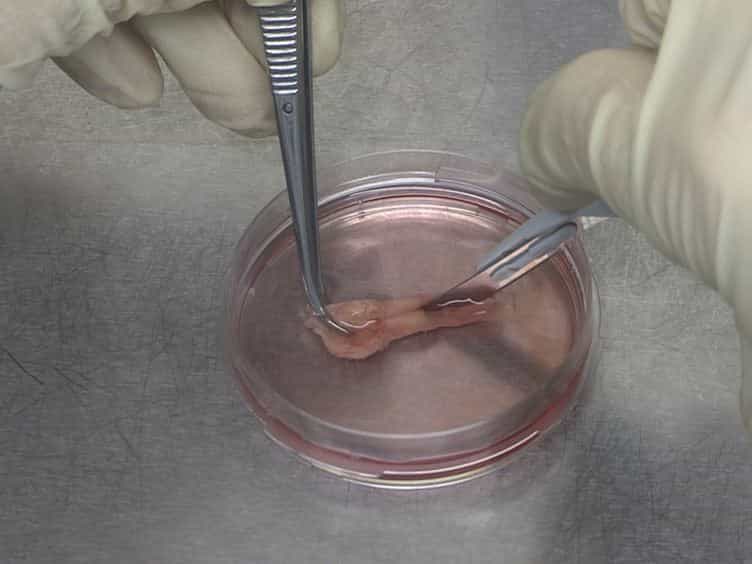

A Human Ex Vivo Atherosclerotic Plaque Model to Study Lesion Biology
Published on: May 6, 2014
Regression of atherosclerosis: which components regress and what influences their reversal
1Atherosclerosis Research Institute, University of Southern California School of Medicine, Los Angeles.

Insights
Atherosclerosis has two stages: atherosis (lipid buildup) and sclerosis (connective tissue buildup). Lipid lowering effectively treats atherosis but is less effective for advanced sclerosis, requiring different treatments for plaque reversal.
Area of Science:
- Cardiovascular Medicine
- Pathology
- Biochemistry
Background:
- Atherosclerosis presents with two distinct features: atherosis, characterized by lipid infiltration, and sclerosis, involving connective tissue deposition and endothelial dysfunction.
- Endothelial dysfunction impairs endothelium-derived relaxing factor (EDRF) release, leading to reduced arterial compliance.
Purpose of the Study:
- To investigate the differential impact of lipid lowering on the atherosis and sclerosis phases of atherosclerosis.
- To explore therapeutic strategies for established fibrous plaques in advanced atherosclerosis.
Main Methods:
- Review of clinical trial evidence regarding lipid-lowering therapies (e.g., LDL-C reduction) in various stages of atherosclerosis.
- Analysis of functional and structural changes in arterial compliance and plaque composition.
Main Results:
- Atherosis, characterized by lipid infiltration, is generally reversible with low-density lipoprotein cholesterol (LDL-C) reduction.
- While maximal LDL-C lowering can improve arterial compliance in established fibrous plaques (sclerosis), structural abnormalities persist.
- Regression of established fibrous plaques is slow in native arteries and absent in bypass grafts with maximal LDL-C reduction.
Conclusions:
- Lipid lowering is most effective in the early atherosis phase of atherosclerosis.
- Advanced atherosclerosis with significant connective tissue sclerosis may require therapeutic agents beyond lipid lowering for plaque reversal.
- Functional improvements in sclerosis can be achieved through maximal LDL-C reduction, likely via EDRF normalization, despite persistent structural changes.
Abstract:
Two major features of atherosclerosis may be distinguished: (a) atherosis caused by lipid infiltration in cells and extracellularly and (b) sclerosis caused by connective tissue deposition and by functional disturbance of the endothelium, leading to impairment of endothelium-derived relaxing factor (EDRF)-release and reduced arterial compliance. Atherosis generally rarely causes clinical symptoms and, furthermore, is reversible by lowering of LDL-C. However, the clinically significant human lesion is the fibrous atheromatous plaque. Regression of established fibrous lesions by maximal lowering of LDL-C is slow in native coronary arteries and nonexistent in bypass grafts. However, there is good evidence from recent clinical trials that even in arteries with significant fibrous plaques, functional improvement of sclerosis (increased compliance) can be achieved by reducing maximally LDL-C in spite of remaining structural connective tissue abnormalities, presumably through normalization of EDRF. Atherosclerosis, therefore, appears to be best influenced by lipid lowering when it is in its atherosis phase. In the plaques of advanced atherosclerosis, when connective tissue sclerosis is present, agents working through mechanisms other than lipid lowering appear to be required for plaque reversal.


Related Concept Videos
 01:38
Inflammation
 01:30
Coronary Artery Disease I: Introduction
 01:30
Atherosclerosis I: Introduction
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:26
Atherosclerosis III: Management
 01:23
Atherosclerosis IV: Nursing Management