Related Experiment Video
Updated: Aug 21, 2026
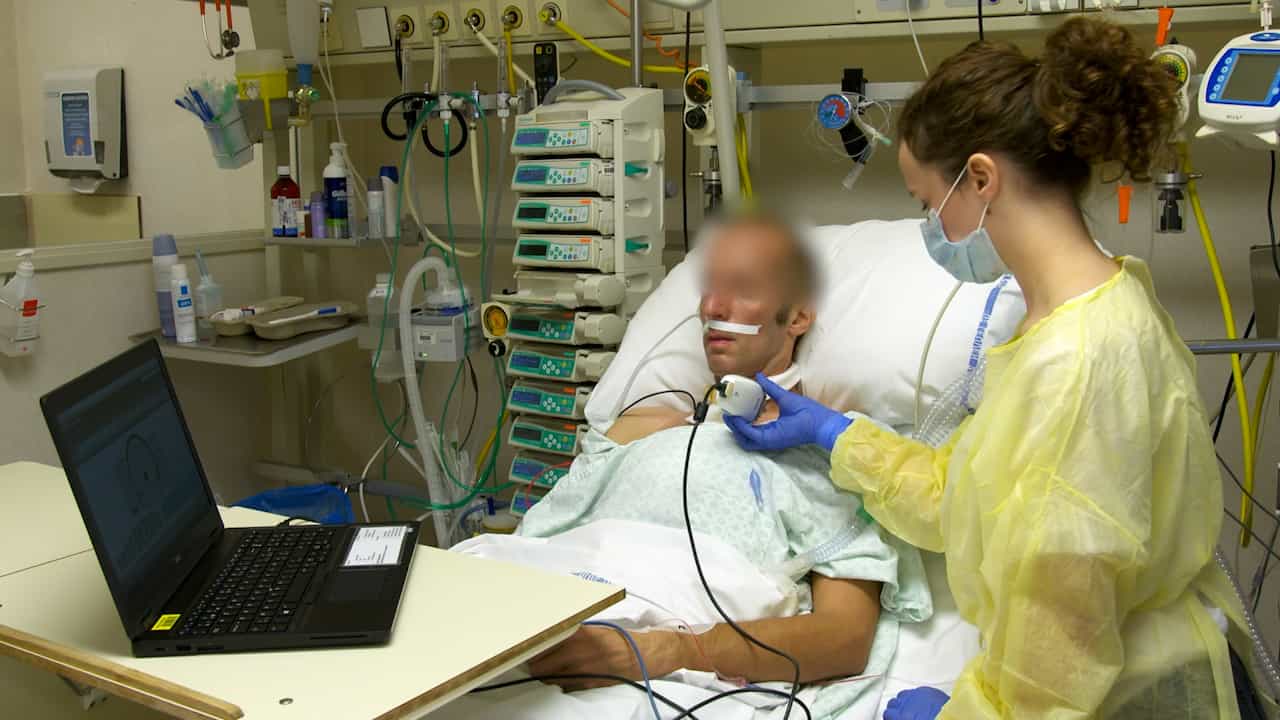

Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Growth hormone treatment of short children born small for gestational age: a US perspective
1University of Cincinnati School of Medicine and Division of Endocrinology, Cincinnati Children's Hospital Medical Center, Cincinnati, Ohio 45229-3039, USA. steven.chernausek@cchmc.org

Insights
Growth hormone (GH) therapy effectively increases growth velocity in short children born small for gestational age (SGA). Optimal dosing, timing, and patient selection for GH treatment in SGA children require further investigation.
Area of Science:
- Pediatric Endocrinology
- Growth and Development
- Genetics and Genomics
Background:
- Growth hormone (GH) therapy has demonstrated efficacy in improving growth velocity for children born small for gestational age (SGA).
- GH deficiency is not typically the cause of poor catch-up growth in SGA children.
- Current US guidelines permit GH treatment for SGA children with persistent short stature.
Purpose of the Study:
- To review the current understanding and challenges of using GH therapy in short children born SGA.
- To highlight the need for optimized treatment strategies regarding dose, timing, and patient selection.
- To emphasize the broader medical, social, and psychological needs of SGA patients.
Main Methods:
- Literature review of research on growth hormone therapy in SGA children over the past decade.
- Analysis of current treatment guidelines and clinical practices in the United States.
- Discussion of the varied etiologies of intrauterine growth retardation and their impact on GH response.
Main Results:
- GH therapy consistently enhances growth velocity in short SGA children.
- The prescribed GH doses often exceed physiological replacement levels.
- Variability in response to GH therapy exists due to diverse etiologies of SGA.
Conclusions:
- GH therapy is a valuable tool for addressing height deficits in SGA children.
- Further research is crucial to establish optimal GH treatment protocols for SGA.
- Comprehensive care addressing the holistic needs of SGA children is essential.
Abstract:
Research during the last decade shows clearly that growth hormone (GH) therapy causes a sustained increase in growth velocity when applied to short children born small for gestational age (SGA). This occurs even though GH deficiency per se is an unlikely explanation for their lack of catch-up growth. In the United States, children born weighing less than -2 SD for gestational age and who show no growth recovery (usually defined as stature persisting below -2 SD at age 2 years) are eligible for GH treatment using doses up to 0.48 mg/kg per week. The management of these children brings new challenges to the pediatric endocrinologist. Intrauterine growth retardation reflects a variety of etiologies, some of which merit special consideration and may respond variably to GH. The dose of GH used exceeds physiologic replacement and is higher than that commonly used to treat other non-GH-deficient conditions such as Turner syndrome. Thus, what constitutes optimal therapy in terms of dose, timing and patient selection remains an important question. While GH therapy provides a means by which one aspect of the SGA syndrome can be helped, there are other issues for SGA apart from height. Future efforts should include studies that better define how GH should be used in the short child born SGA and address more broadly the medical, social and psychological needs of these patients.
Related Concept Videos
 01:10
Nature and Nurture
 01:15
Hypoglycemia and Glucagon
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...
 00:49
What is Genetic Engineering?
 00:59
Gene Therapy