Related Experiment Video
Updated: Aug 20, 2026

Evaluation of Coronary Flow Reserve After Myocardial Ischemia Reperfusion in Rats
Published on: June 28, 2019
Effect of acute hyperhomocysteinemia on coronary flow reserve in healthy adults
Luigi Ascione1, Mario De Michele, Maria Accadia
1Division of Cardiology and Clinical Analysis Laboratory, S. Maria di Loreto Hospital, Naples, Italy. luigi.ascione20@tin.it

Insights
Elevated homocysteine levels significantly reduce coronary flow reserve (CFR) in healthy adults. This finding highlights a potential link between homocysteine and early arterial dysfunction.
Area of Science:
- Cardiovascular Physiology
- Metabolic Medicine
Background:
- Hyperhomocysteinemia is linked to preclinical arterial abnormalities.
- The impact of elevated homocysteine on coronary flow reserve (CFR) requires further investigation.
Purpose of the Study:
- To evaluate the effect of acute hyperhomocysteinemia on coronary flow reserve (CFR) in healthy adults.
Main Methods:
- A double-blind, placebo-controlled crossover study involving 20 healthy subjects.
- Homocysteine levels were measured via high-performance liquid chromatography after a methionine load or placebo.
- Coronary flow reserve (CFR) was assessed using transthoracic Doppler echocardiography.
Main Results:
- Methionine load significantly increased plasma homocysteine levels (P < .0001).
- Coronary flow reserve (CFR) decreased significantly after methionine load (P < .001).
- Postload homocysteine levels showed an inverse correlation with CFR (r = -0.21, P = .02).
Conclusions:
- Acute hyperhomocysteinemia is associated with a significant reduction in coronary flow reserve (CFR) in asymptomatic adults.
- This suggests a potential role for homocysteine in early coronary vascular dysfunction.
Background:
B-mode ultrasound studies indicate that hyperhomocysteinemia is associated with preclinical structural and functional arterial abnormalities. This study was designed to evaluate the effect of elevated plasma homocysteine levels on coronary flow reserve (CFR).
Methods:
A total of 20 healthy subjects aged 41 +/- 7 years were studied on 2 separate days, a week apart, before and after methionine load (100 mg/kg of body weight) or placebo in a double-blind crossover study. At each visit, homocysteine levels were measured by high performance liquid chromatography and CFR was determined by transthoracic Doppler echocardiography.
Results:
After methionine load, plasma homocysteine increased from 10.7 +/- 2.8 mumol/L to 30.4 +/- 5.1 mumol/L ( P < .0001) and CFR decreased from 3.0 +/- 0.4 to 2.3 +/- 0.3 ( P < .001). CFR was inversely related to postload homocysteine levels ( r = -0.21, P = .02). After placebo, there was no change in CFR.
Conclusion:
In asymptomatic adults, acute hyperhomocysteinemia is associated with a significant reduction in CFR.
Related Concept Videos
 01:19
Blood Studies for Cardiovascular System II: CRP, Hcy, and Cardiac Natriuretic Peptide Markers
These markers indicate stress or strain on the heart muscle:
Natriuretic Peptides (BNP)
Cardiac myocytes produce these hormones in response to ventricular stretching...
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:26
Coronary Artery Disease II: Pathophysiology
 01:19
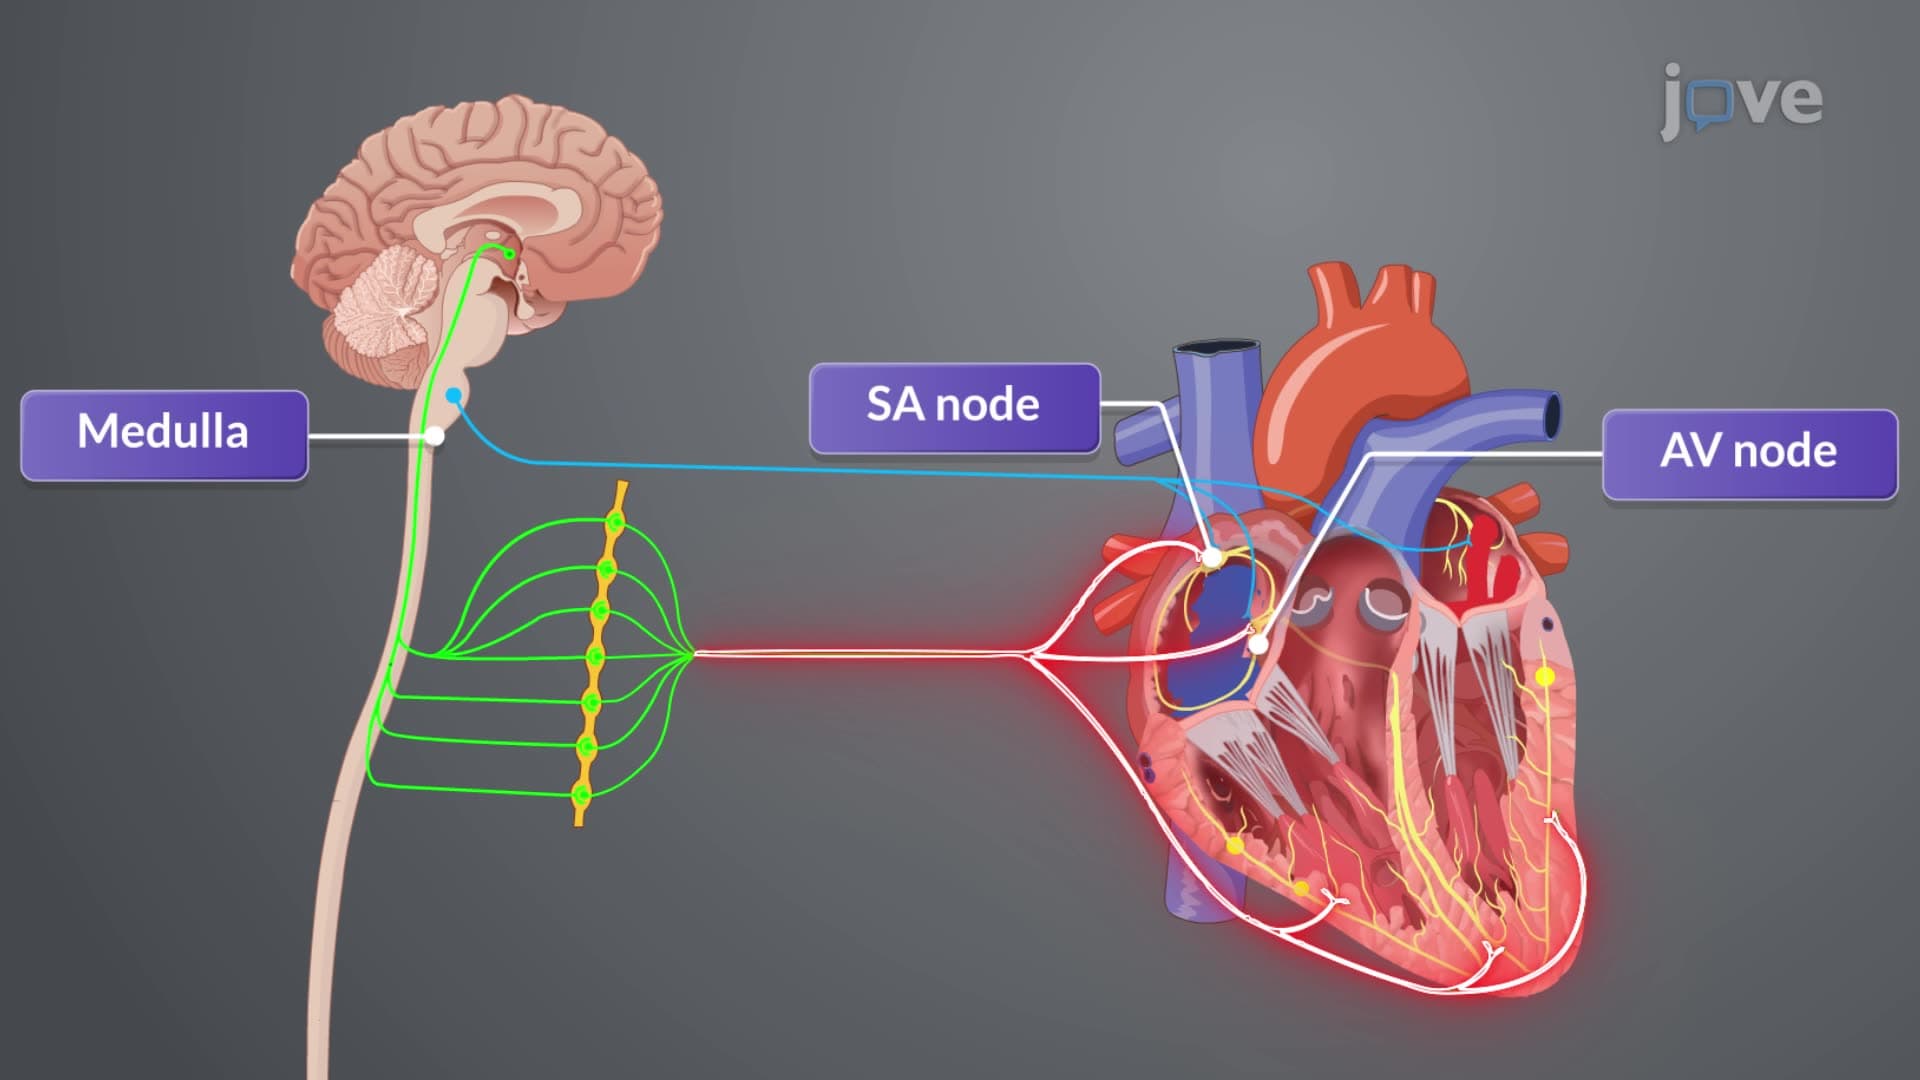
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart rate...
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow