Related Experiment Video
Updated: Aug 19, 2026


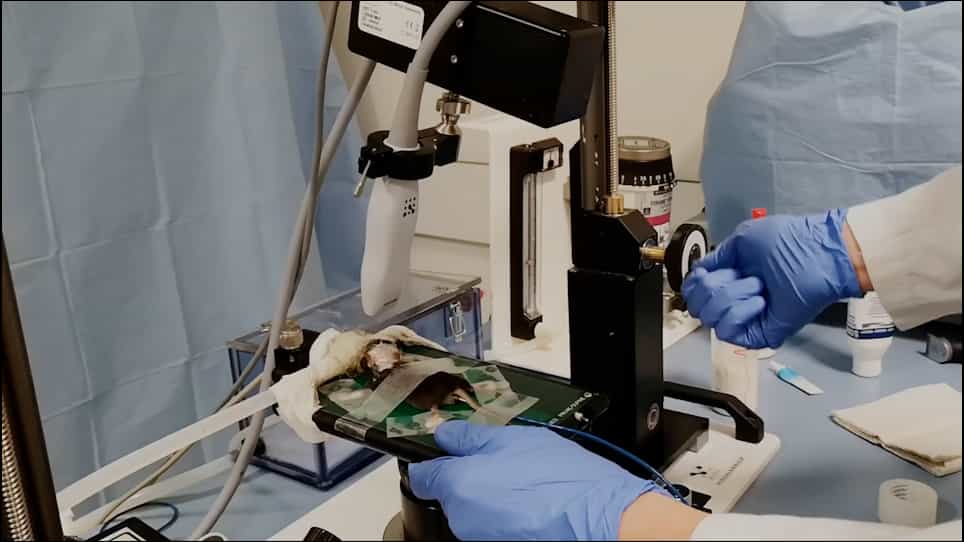
Pre-Chiasmatic, Single Injection of Autologous Blood to Induce Experimental Subarachnoid Hemorrhage in a Rat Model
Published on: June 18, 2021
Cerebral Vasospasm in Subarachnoid Hemorrhage
Alejandro A Rabinstein1, Eelco F M Wijdicks
1Department of Neurology, University of Miami School of Medicine, Miami, FL 33124, USA. arabinstein@med.miami.edu.

The treatment of vasospasm after subarachnoid hemorrhage remains a formidable challenge. The prompt recognition of this complication is essential to prevent ischemic damage. Initial orders should include adequate fluid and sodium supplementation to avoid volume depletion. Prophylactic hypervolemia is not effective in reducing the incidence of vasospasm and may be deleterious. Oral nimodipine (60 mg every 4 hours for 21 days) should be started on admission because it protects against delayed ischemic damage. Increasing blood flow velocities on serial transcranial Doppler studies are reliable indicators of early development of vasospasm. When symptomatic vasospasm occurs, hemodynamic augmentation therapy should be instituted. Crystalloids and colloids may be used to promote hypervolemia. Colloids may provide additional benefit by producing hemodilution. However, the rheological benefits of hemodilution may be offset by reduced oxygen carrying capacity when hematocrit drops below 28%. Hypertension may be induced by administering inotropic drugs and, in certain cases, cardiac output optimization using dobutamine also is necessary. When aggressive medical therapy fails to reverse ischemic deficits, prompt endovascular intervention is indicated. Focal vasospasm of larger vessels may be effectively treated with angioplasty and the benefits of this procedure are durable. Diffuse vasospasm involving smaller arterial branches may be treated with intra-arterial infusion of vasodilators, such as papaverine, verapamil, or nicardipine. Unfortunately, these dilatory effects tend to be short-lasting. In refractory cases, hypothermia may be considered, although value of this strategy remains largely unexplored.
The treatment of vasospasm after subarachnoid hemorrhage remains a formidable challenge. The prompt recognition of this complication is essential to prevent ischemic damage. Initial orders should include adequate fluid and sodium supplementation to avoid volume depletion. Prophylactic hypervolemia is not effective in reducing the incidence of vasospasm and may be deleterious. Oral nimodipine (60 mg every 4 hours for 21 days) should be started on admission because it protects against delayed ischemic damage. Increasing blood flow velocities on serial transcranial Doppler studies are reliable indicators of early development of vasospasm. When symptomatic vasospasm occurs, hemodynamic augmentation therapy should be instituted. Crystalloids and colloids may be used to promote hypervolemia. Colloids may provide additional benefit by producing hemodilution. However, the rheological benefits of hemodilution may be offset by reduced oxygen carrying capacity when hematocrit drops below 28%. Hypertension may be induced by administering inotropic drugs and, in certain cases, cardiac output optimization using dobutamine also is necessary. When aggressive medical therapy fails to reverse ischemic deficits, prompt endovascular intervention is indicated. Focal vasospasm of larger vessels may be effectively treated with angioplasty and the benefits of this procedure are durable. Diffuse vasospasm involving smaller arterial branches may be treated with intra-arterial infusion of vasodilators, such as papaverine, verapamil, or nicardipine. Unfortunately, these dilatory effects tend to be short-lasting. In refractory cases, hypothermia may be considered, although value of this strategy remains largely unexplored.
Related Concept Videos
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:17
Hemorrhagic Stroke l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology
 01:16
Vascular Spasm
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:14
Increased Intracranial Pressure l: Introduction