The tubular maximum for calcium reabsorption: a normal range in children
Related Experiment Video
Updated: Nov 8, 2026
Cytosolic Calcium Measurements in Renal Epithelial Cells by Flow Cytometry
Published on: October 28, 2014
N J Shaw1, J Wheeldon, J T Brocklebank
1Department of Paediatrics and Child Health, St James's University Hospital, Leeds, UK.

Insights
This study establishes a normal range for tubular maximum calcium reabsorption in children, finding it higher than in adults. This range aids in assessing pediatric renal calcium handling and calcium homeostasis disorders.
Area of Science:
- Pediatric Nephrology
- Renal Physiology
- Calcium Metabolism
Background:
- Accurate assessment of renal calcium handling is crucial for diagnosing and managing pediatric calcium homeostasis disorders.
- Establishing normative data for tubular calcium reabsorption is essential for clinical interpretation.
Purpose of the Study:
- To define the normal range for the tubular maximum rate of calcium reabsorption, corrected for glomerular filtration rate (TLCa/GFR), in healthy children.
- To investigate the relationship between TLCa/GFR and urinary sodium excretion and parathyroid hormone levels in children.
Main Methods:
- A prospective survey design was employed.
- One hundred and ten healthy children aged 2-14 years were recruited.
- Measurements included total plasma calcium, ultrafiltrable calcium, parathyroid hormone, and urinary calcium, sodium, and creatinine excretion.
Main Results:
- The normal range for TLCa/GFR was determined to be 1.87-3.39 mmol/l of glomerular filtrate, with a geometric mean of 2.40 mmol/l.
- A significant inverse relationship was observed between TLCa/GFR and urinary sodium excretion.
- No significant correlation was found between TLCa/GFR and parathyroid hormone levels in this cohort.
Conclusions:
- The normal range for TLCa/GFR in children is higher than that reported for adults.
- These findings provide valuable reference data for evaluating renal calcium handling in pediatric populations.
- The established normal range will assist in the clinical assessment of children with disorders affecting calcium homeostasis.
Objective:
We aimed to establish a normal range for the tubular maximum rate of reabsorption of calcium corrected for glomerular filtration rate.
Design:
A prospective survey was used.
Patients:
One hundred and ten normal children aged 2-14 years were studied.
Measurements:
Total plasma calcium, ultrafiltrable calcium and parathyroid hormone. Urinary calcium, sodium and creatinine excretion.
Results:
The normal range was found to be 1.87-3.39 mmol/l of glomerular filtrate with a geometric mean value of 2.40 mmol/l. There was a significant inverse relationship between the tubular maximum for calcium and the urinary sodium excretion. No significant relationship was found between the tubular maximum for calcium and the level of parathyroid hormone in this group of normal children.
Conclusions:
The normal range seen in children is higher than that seen in adults with a higher mean value. This normal range should be useful in the assessment of renal calcium handling in children with disorders of calcium homeostasis.
Related Concept Videos
 01:21
Skeleton and Calcium Homeostasis
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:28
Tubular Reabsorption and Secretion
Tubular reabsorption is a selective process that starts when the filtrate enters the proximal tubules. It involves substances traveling through the transcellular route (through the tubule cell and peritubular...
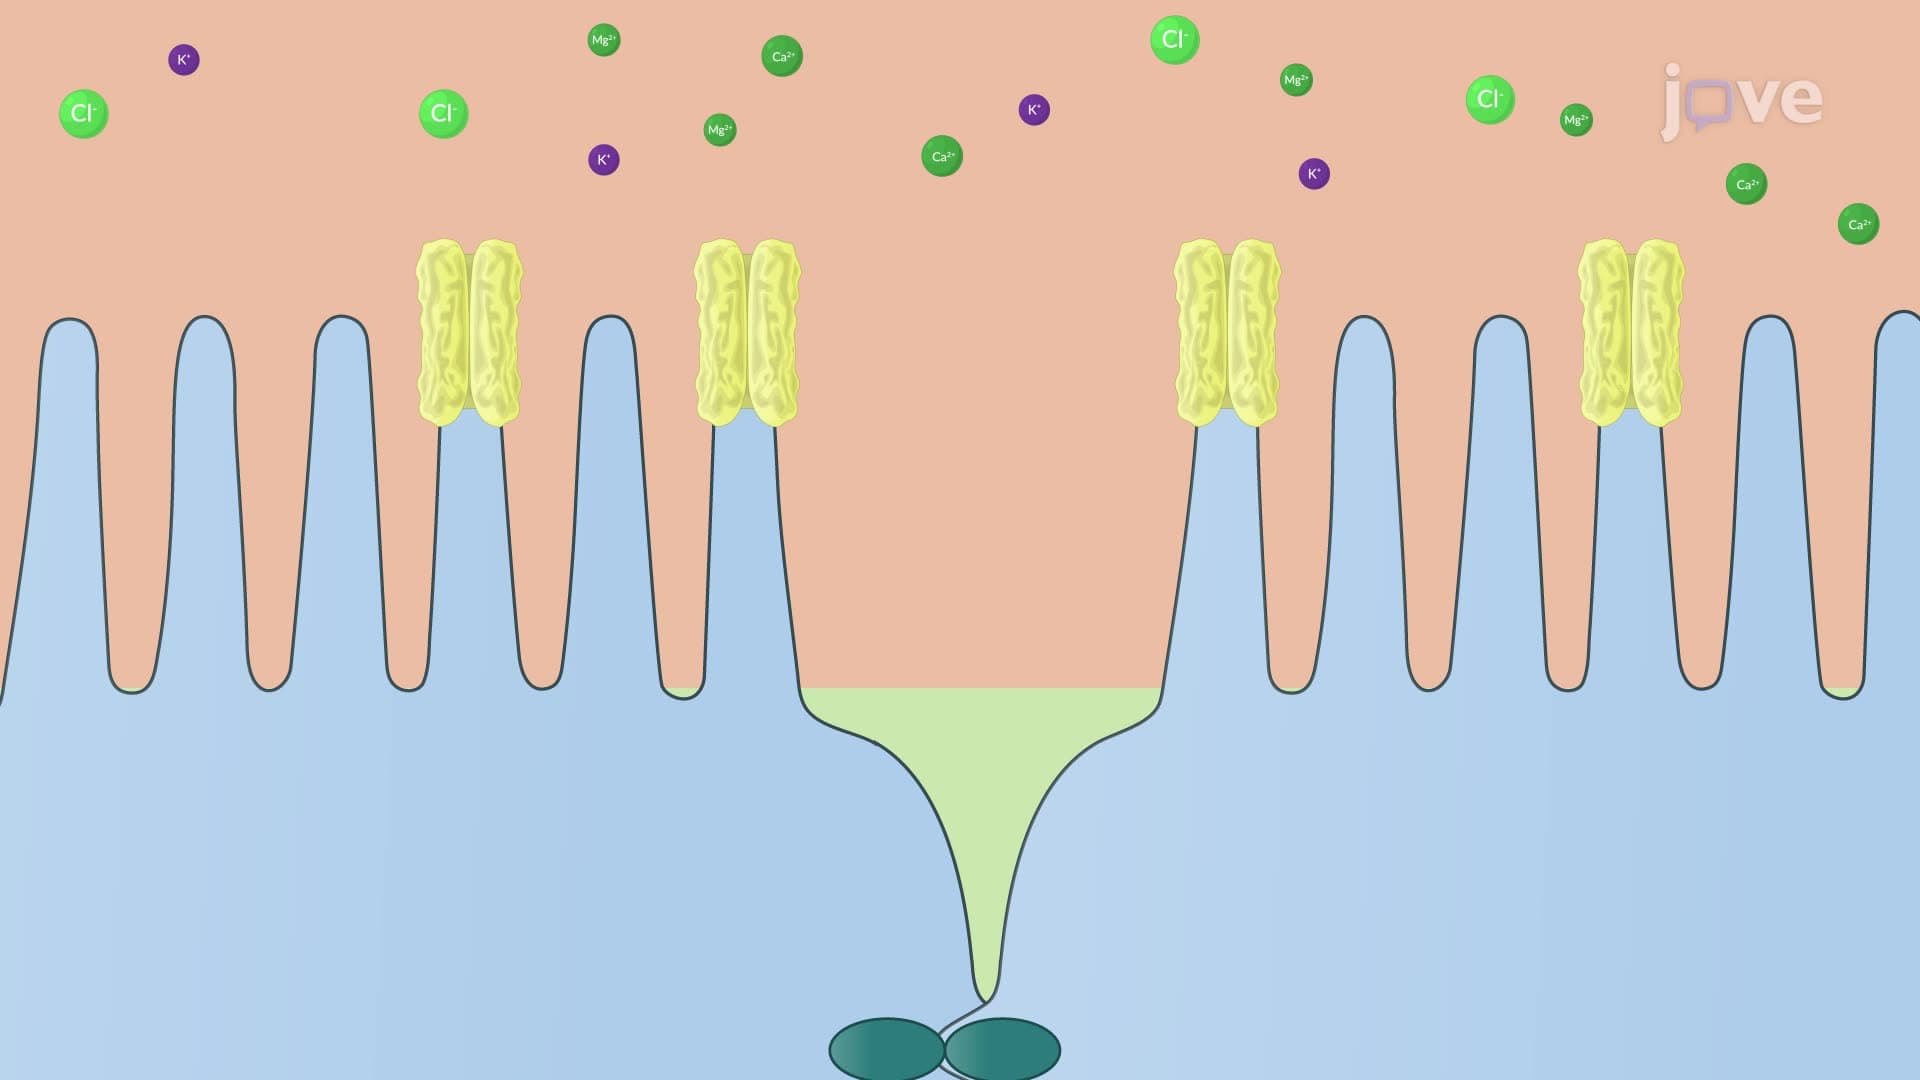 01:28
Reabsorption and Secretion in the PCT
Transport mechanisms involving sodium ions (Na+) contribute significantly to solute reabsorption. These mechanisms include symport and antiport processes.
A key example is the...
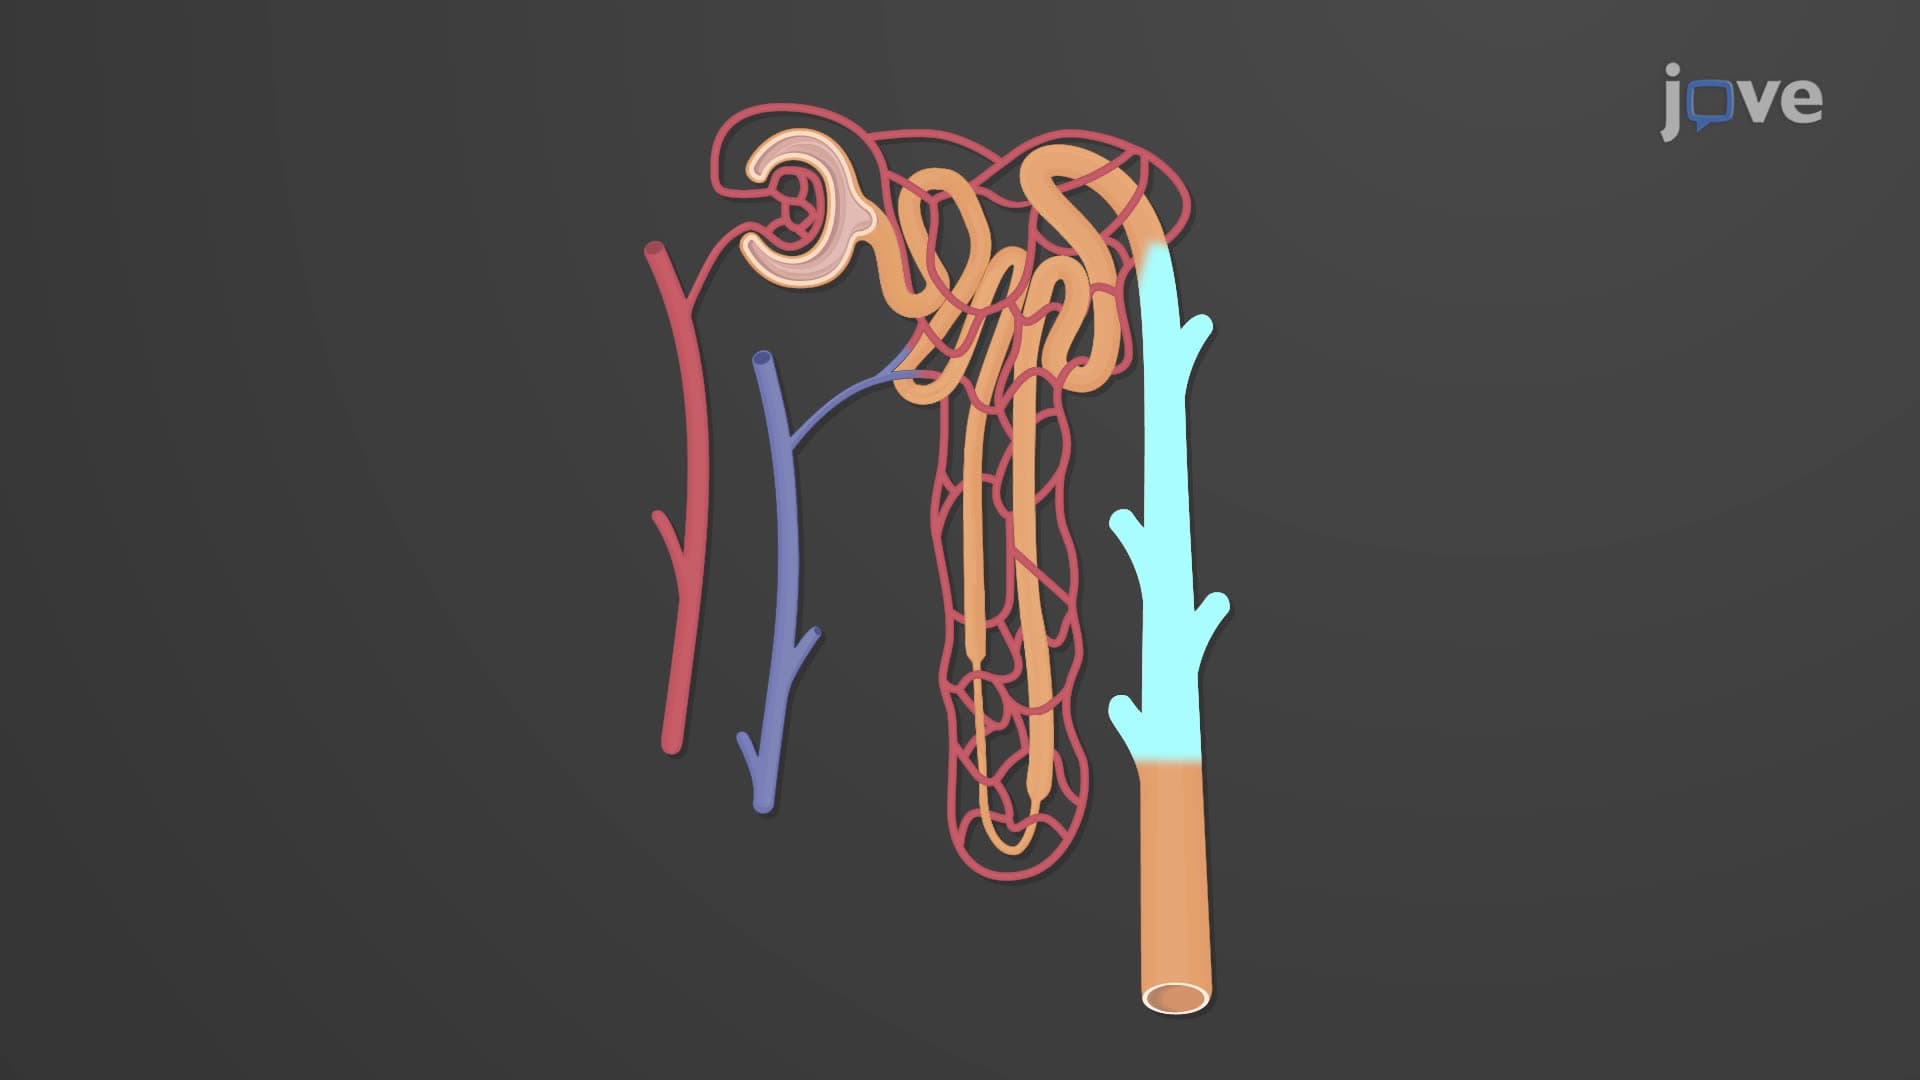 01:26
Reabsorption and Secretion in the DCT and Collecting Duct
The distal part of the DCT, along with the...
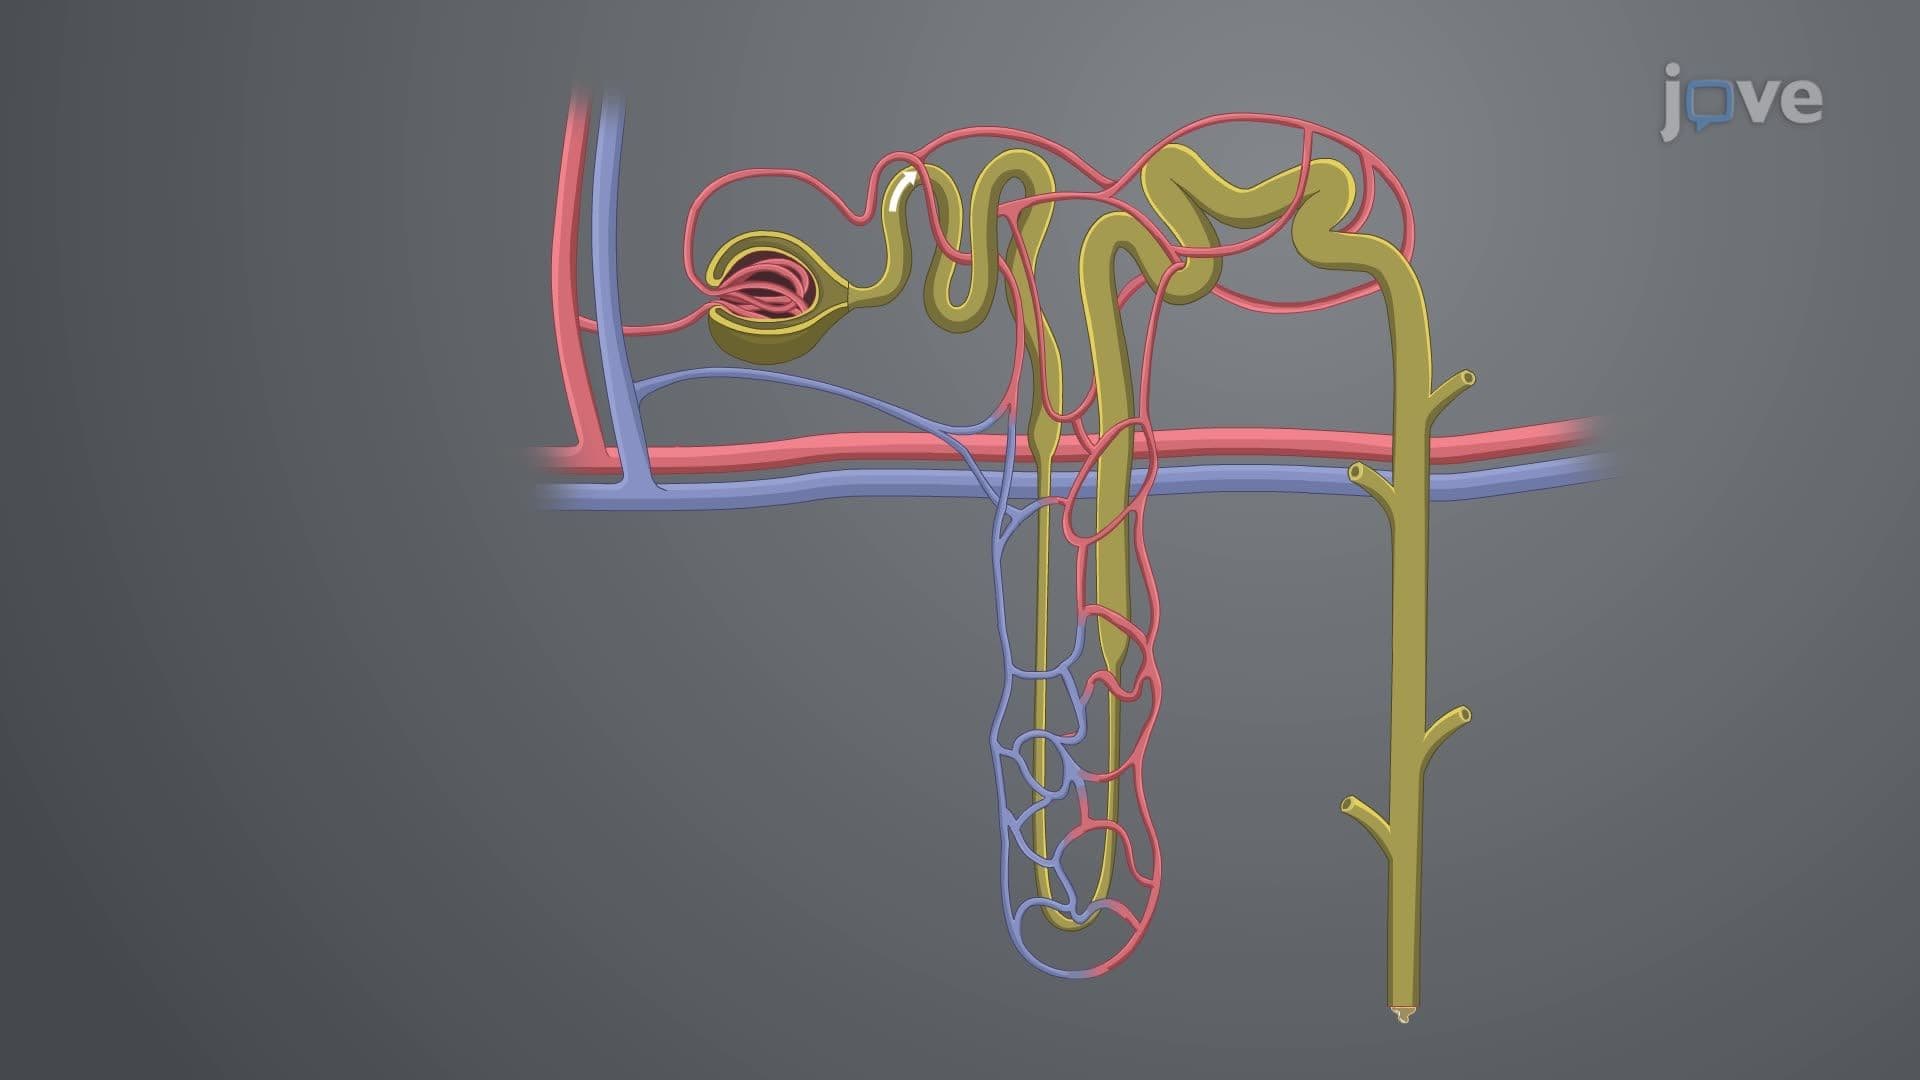 01:22
Physiology of the Genitourinary System II: Tubular Reabsorption and Secretion