The safety of newer antidepressants in pregnancy and breastfeeding
Related Experiment Video
Updated: Aug 7, 2026

Using Chronic Social Stress to Model Postpartum Depression in Lactating Rodents
Published on: June 10, 2013
1Department of Mental Health, ASL Salerno 1, District n. 4, Cava de' Tirreni (Salerno), Italy. salvatore_gentile@aliceposta.it

The pregnancy and postpartum periods are considered to be relatively high risk times for depressive episodes in women, particularly for those with pre-existing psychiatric illnesses. Therefore, it may be necessary to start or continue the pharmacological treatment of depression during these two timeframes. Hence, the aim of this review is to examine the effects on the fetus and infant of exposure, through the placenta and maternal milk, to the following drugs: fluoxetine, fluvoxamine, paroxetine, sertraline, citalopram, escitalopram, mirtazapine, venlafaxine, reboxetine and bupropion. The teratogenic risks, perinatal toxicity and effects on the neurobehavioural development of newborns associated with exposure through the placenta or maternal milk to these medications need to be carefully assessed before starting psychopharmacological treatment in pregnant or lactating women. In spite of the limitations of some of the studies reviewed, the older selective serotonin-reuptake inhibitors (SSRIs) [as we await further data regarding escitalopram] and venlafaxine seem to be devoid of teratogenic risks. By contrast, the data concerning possible consequences related to exposure to SSRIs via the placenta and breastmilk on neonatal adaptation and long-term neurocognitive infant's development are still controversial. Nevertheless, a number of reports have shown that an association between placental exposure to SSRIs and adverse but self-limiting effects on neonatal adaptation may exist. In addition, the information on both teratogenic and functional teratogenic risks associated with exposure to bupropion, mirtazapine and reboxetine is incomplete or absent; at present, these compounds should not be used as first-line agents in the pharmacological treatment of depression in pregnancy and breastfeeding. Untreated depression is not without its own risks since mothers affected by depression have a negative impact on the emotional development of their children and major depression, especially when complicated by a delusional component, may lead to the mother attempting suicide and infanticide. Consequently, clinicians need to help mothers weigh the risks of prenatal exposure to drugs for their babies against the potential risks of untreated depression and abrupt discontinuation of pharmacological treatment. Given these situations, we suggest that choosing to administer psychopharmacological treatment in pregnant or breastfeeding women with depression will result primarily from a careful evaluation of their psychopathological condition; currently, the degree of severity of maternal disease appears to represent the most relevant parameter to take this clinical decision.
The pregnancy and postpartum periods are considered to be relatively high risk times for depressive episodes in women, particularly for those with pre-existing psychiatric illnesses. Therefore, it may be necessary to start or continue the pharmacological treatment of depression during these two timeframes. Hence, the aim of this review is to examine the effects on the fetus and infant of exposure, through the placenta and maternal milk, to the following drugs: fluoxetine, fluvoxamine, paroxetine, sertraline, citalopram, escitalopram, mirtazapine, venlafaxine, reboxetine and bupropion. The teratogenic risks, perinatal toxicity and effects on the neurobehavioural development of newborns associated with exposure through the placenta or maternal milk to these medications need to be carefully assessed before starting psychopharmacological treatment in pregnant or lactating women. In spite of the limitations of some of the studies reviewed, the older selective serotonin-reuptake inhibitors (SSRIs) [as we await further data regarding escitalopram] and venlafaxine seem to be devoid of teratogenic risks. By contrast, the data concerning possible consequences related to exposure to SSRIs via the placenta and breastmilk on neonatal adaptation and long-term neurocognitive infant's development are still controversial. Nevertheless, a number of reports have shown that an association between placental exposure to SSRIs and adverse but self-limiting effects on neonatal adaptation may exist. In addition, the information on both teratogenic and functional teratogenic risks associated with exposure to bupropion, mirtazapine and reboxetine is incomplete or absent; at present, these compounds should not be used as first-line agents in the pharmacological treatment of depression in pregnancy and breastfeeding. Untreated depression is not without its own risks since mothers affected by depression have a negative impact on the emotional development of their children and major depression, especially when complicated by a delusional component, may lead to the mother attempting suicide and infanticide. Consequently, clinicians need to help mothers weigh the risks of prenatal exposure to drugs for their babies against the potential risks of untreated depression and abrupt discontinuation of pharmacological treatment. Given these situations, we suggest that choosing to administer psychopharmacological treatment in pregnant or breastfeeding women with depression will result primarily from a careful evaluation of their psychopathological condition; currently, the degree of severity of maternal disease appears to represent the most relevant parameter to take this clinical decision.
More Related Videos
 06:39
Using a Murine Model of Psychosocial Stress in Pregnancy as a Translationally Relevant Paradigm for Psychiatric Disorders in Mothers and Infants
Published on: June 13, 2021
 08:15
Network Pharmacology and Validation of the Antidepressant Mechanisms of Qiangzhifang in a Chronic Restraint Stress-induced Depression Rat Model
Published on: June 6, 2025
Related Concept Videos
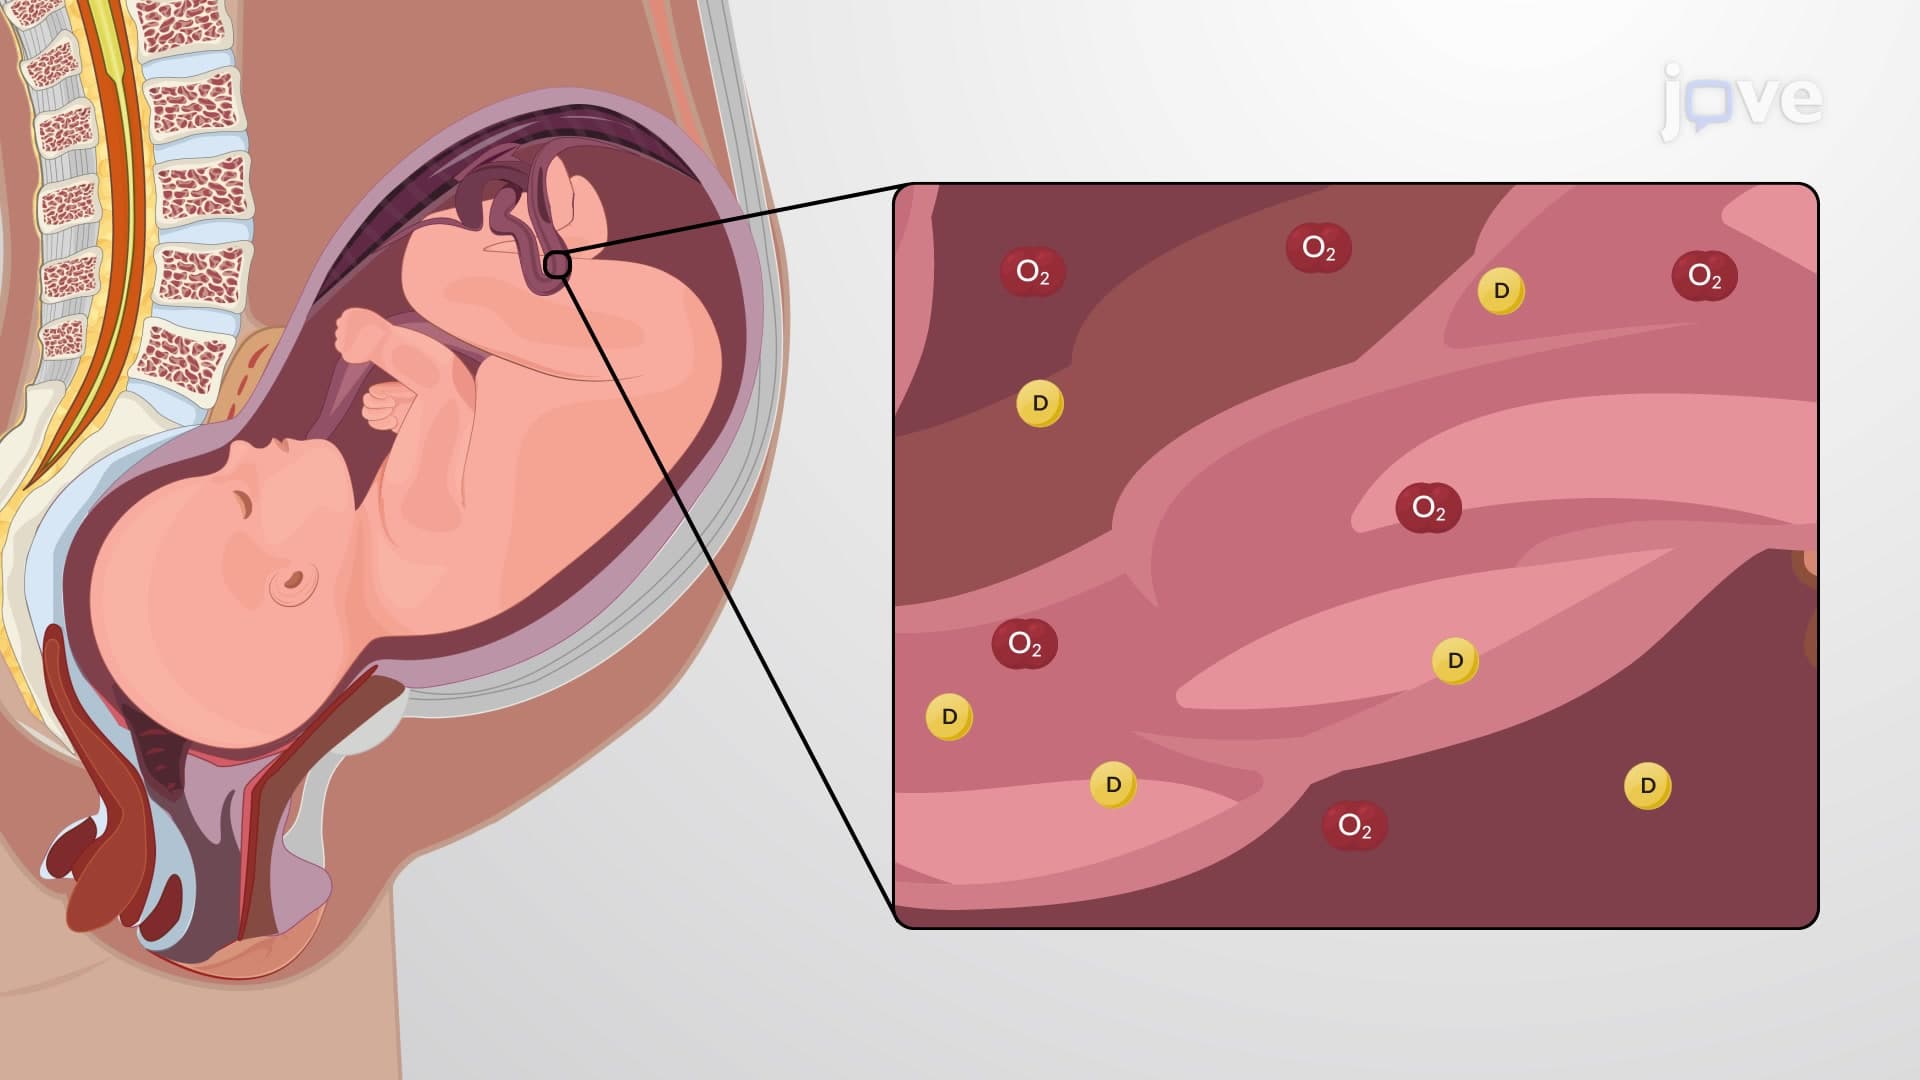 01:21
Factors Affecting Drug Response: Overview
 01:25
Antidepressant Drugs: Overview
 01:28
Antidepressant Drugs: Tricyclics, SSRIs, and SNRIs
 01:23
Antidepressant Drugs: MAOIs and Other Agents
 01:23
Upper Respiratory Drugs: Antitussives, Expectorants, and Mucolytics
Antitussives include codeine, dextromethorphan (Robitussin), and benzonatate (Tessalon). Codeine and dextromethorphan exert their effects centrally by suppressing the cough reflex center in the medulla. Benzonatate operates peripherally within the respiratory tract by anesthetizing...
 01:28
Drug Therapy
Antianxiety Medications