Related Experiment Video
Updated: Jul 16, 2026
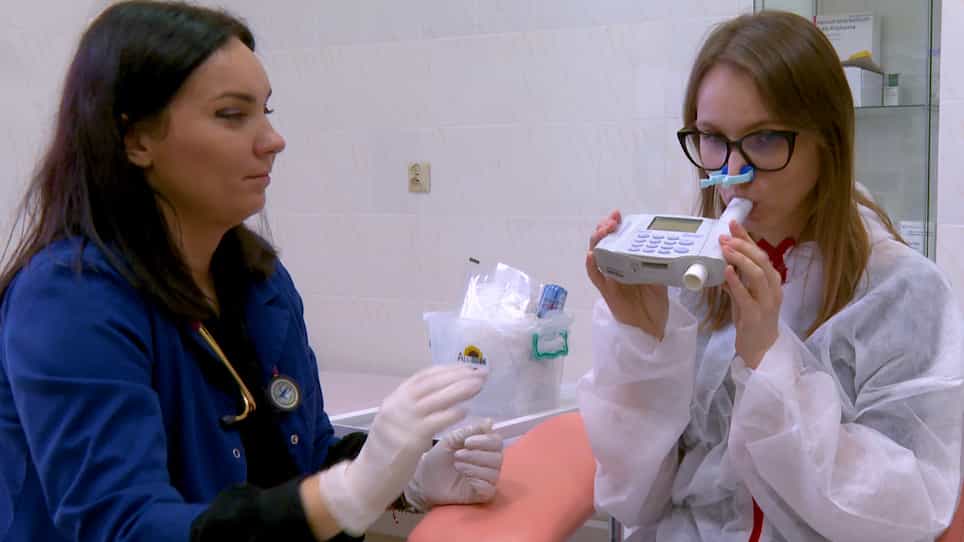

Symptom Assessment of Patients with Allergic Rhinitis Using an Allergen Exposure Chamber
Published on: March 3, 2023
Clinical outcomes and adverse effect monitoring in allergic rhinitis
Elizabeth F Juniper1, Elisabeth Ståhl, Richard L Doty
1Department of Clinical Epidemiology and Biostatistics, McMaster University, Hamilton, Canada.

Abstract:
The subjective recording in diary cards of symptoms of itch, sneeze, nose running, and blockage, with the use of a rating scale to indicate the level of severity, is usual for clinical trials in allergic rhinitis. The primary outcome measure is usually a composite score that enables a single total symptoms score endpoint. It is appreciated, however, that rhinitis has a greater effect on the individual than is reflected purely by the recording of anterior nasal symptoms. Nasal obstruction is troublesome and may lead to sleep disturbance in addition to impaired daytime concentration and daytime sleepiness. These impairments affect school and work performance. Individuals with rhinitis find it socially embarrassing to be seen sneezing, sniffing, or blowing their nose. To capture these and other aspects of the disease-specific health-related quality of life, questionnaires such as the Rhinoconjunctivitis Quality of Life Questionnaire have been developed and validated for clinical trial use. The adoption of health-related quality of life questionnaires into clinical trials broadens the information obtained regarding the effect of the therapeutic intervention and helps focus on issues relevant to the individual patient. It must be appreciated that it is not only the disease that may adversely affect health-related quality of life; administered therapy, although intended to be beneficial, may also cause health impairment. Adverse-event monitoring is thus essential in clinical trials. The first-generation H 1 -histamines, because of their effect on central H 1 -receptors, are classically associated with central nervous system (CNS) effects such as sedation. Although this is not always perceived by the patient, it is clearly evident with objective performance testing, and positron emission tomography scanning has directly demonstrated the central H 1 -receptor occupancy. The second-generation H 1 -antihistamines have reduced central H 1 -receptor occupancy and considerably reduced or absent CNS sedative effects. Therefore, the CNS effects are entirely avoidable, and the first-generation H 1 -antihistamines should no longer be used in the management of allergic rhinitis. The considerably rarer but potentially very serious cardiac arrhythmogenic effects of H 1 -antihistamines are appreciated to be molecule-specific rather than class-specific. The in vitro screening of new compounds to eliminate the further development of those with cardiotoxicity ideally will lead to this adverse effect being historic. The incorporation of electrocardiogram recording in clinical trials provides direct information relating to prolongation of QT interval corrected for heart rate. Although administered at low doses, intranasal steroids still have the potential for systemic absorption and adverse consequences. However, it is appreciated that meaningful differences exist in the bioavailability of different steroid molecules, and although a small but statistically significant effect on growth in children has been identified with the long-term use of intranasal beclomethasone when administered twice daily for 1 year, this is not evident with all intranasal steroids. In addition, twice-daily intranasal steroid administration may have more effect--from the endocrinologic perspective--than once-daily administration in the morning, which coincides better with the natural diurnal variation in cortisol. Thus, once-daily intranasal steroid administration is preferable, and when used in studies in children, measurement of height change during the study period is an important outcome variable together with other indices of systemic steroid bioavailability (eg, tests of hypothalamic-pituitary-adrenal axis function). These considerations have even greater relevance if children are concurrently also receiving inhaled steroids for asthma, because the total steroid load will be greater.

Related Concept Videos
 01:19
Pharmacovigilance
This process, termed pharmacovigilance, aims to detect, evaluate, and minimize harmful effects related to medication use. The data collection for pharmacovigilance depends on spontaneous reporting systems, where healthcare professionals or patients voluntarily report suspected ADRs.
In some cases, there...
 01:17
Drugs Used in Lower Respiratory Disorders: Overview
Bronchodilators, the first step of respiration enhancement, come in various forms, each with its own mechanism...
 01:25
Antiasthma Drugs: β2-Adrenoceptor Agonists
One class of bronchodilators includes β2-adrenoceptor agonists. These agents target the β2-adrenoceptors located on bronchial smooth muscle cells. By stimulating these receptors, β2-agonists induce relaxation in these...
 01:19
Antiasthma Drugs: Leukotriene Modifiers
Leukotriene modifiers work through two distinct mechanisms:
 01:25
Antiasthma Drugs: Mast Cell Stabilizers and Anti-IgE Drugs
Mast cell stabilizers, such as cromolyn (also known as sodium cromoglycate) and nedocromil (Tilade), are effective drugs in asthma management. These stabilizers hinder histamine release by skillfully obstructing the activation of mast cells and other cellular entities. Notably, they navigate this task without...
 01:13
Asthma III: Clinical Manifestations