Related Experiment Video
Updated: Aug 19, 2026
Clinical Efficacy of Tissue-Bone Homeostasis Manipulation on Soft Tissue Balance and Function in Knee Osteoarthritis
Published on: June 16, 2026
A two-year prospective controlled study of bone mass and bone turnover in children with early juvenile idiopathic
Gunhild Lien1, Anne M Selvaag, Berit Flatø
1Rikshospitalet University Hospital, Oslo, Norway. gunhild.lien@chello.no <gunhild.lien@chello.no>

Insights
Children with juvenile idiopathic arthritis (JIA) experience reduced bone mass gains and lean mass early in the disease. Weight-bearing activity and bone turnover markers predict bone mass changes in JIA patients.
Area of Science:
- Pediatric Rheumatology
- Pediatric Endocrinology
- Bone Metabolism
Background:
- Juvenile idiopathic arthritis (JIA) is a chronic inflammatory condition affecting children.
- Bone health is a significant concern in JIA due to potential long-term consequences.
- Early identification of bone mass reduction predictors is crucial for intervention.
Purpose of the Study:
- To investigate early bone mass changes in children with JIA.
- To identify predictors of bone mass reduction in pediatric JIA patients.
- To differentiate bone mass trajectories between JIA patients and healthy controls.
Main Methods:
- Prospective cohort study matching 108 children with early JIA to 108 healthy controls.
- Assessment of bone mineral density, bone mineral content, body composition, and growth at baseline and 24-month follow-up.
- Analysis of biochemical markers of bone turnover and weight-bearing activities.
Main Results:
- JIA patients showed significantly lower gains in total body bone mineral content and lean mass compared to healthy children.
- Reduced bone formation, bone resorption, and weight-bearing activities were noted in JIA patients.
- Serum bone-specific alkaline phosphatase, C-telopeptide of type I collagen, and weight-bearing activities predicted total body bone mineral content changes in JIA.
Conclusions:
- Children with JIA exhibit moderate reductions in bone mass accrual and lean mass early in their disease course.
- Bone turnover and weight-bearing activities are significantly impacted in early JIA.
- Specific biochemical markers and physical activity levels are key predictors of bone health in pediatric JIA.
Objective:
To explore early changes and predictors of bone mass in children with juvenile idiopathic arthritis (JIA) in order to identify patients who will develop bone mass reductions.
Methods:
We conducted a prospective cohort study of 108 children with early JIA (ages 6-18 years; mean disease duration 19.3 months) who were individually matched with 108 healthy children for age, sex, race, and county of residence. Bone mass and changes in total body, spine, femur, and forearm bone mineral density and bone mineral content (BMC), body composition, growth, and biochemical parameters of bone turnover were examined at baseline and at followup a mean of 24 months later. Low bone mass was defined as a Z score >1 SD below the reference population.
Results:
Of the 200 children evaluated at followup, the 100 healthy children had greater gains in total body BMC (P = 0.035), distal radius BMC (P < 0.001), and total body lean mass (P < 0.001) than did the 100 JIA patients. Low or very low total body BMC was observed in 24% of the patients and 12% of the healthy children. Bone formation, bone resorption, and weight-bearing activities were reduced in the patients compared with the healthy children. Multiple regression analysis showed that in patients with JIA, serum bone-specific alkaline phosphatase, serum C-telopeptide of type I collagen, and weight-bearing activities were independent predictors of changes in total body BMC. Total body BMC was lower in patients with polyarticular onset than in those with oligoarticular disease onset.
Conclusion:
Patients with JIA have moderate reductions in bone mass gains, bone turnover, and total body lean mass early in the disease course.
Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:27
Growth of Cartilage and Bone Tissue
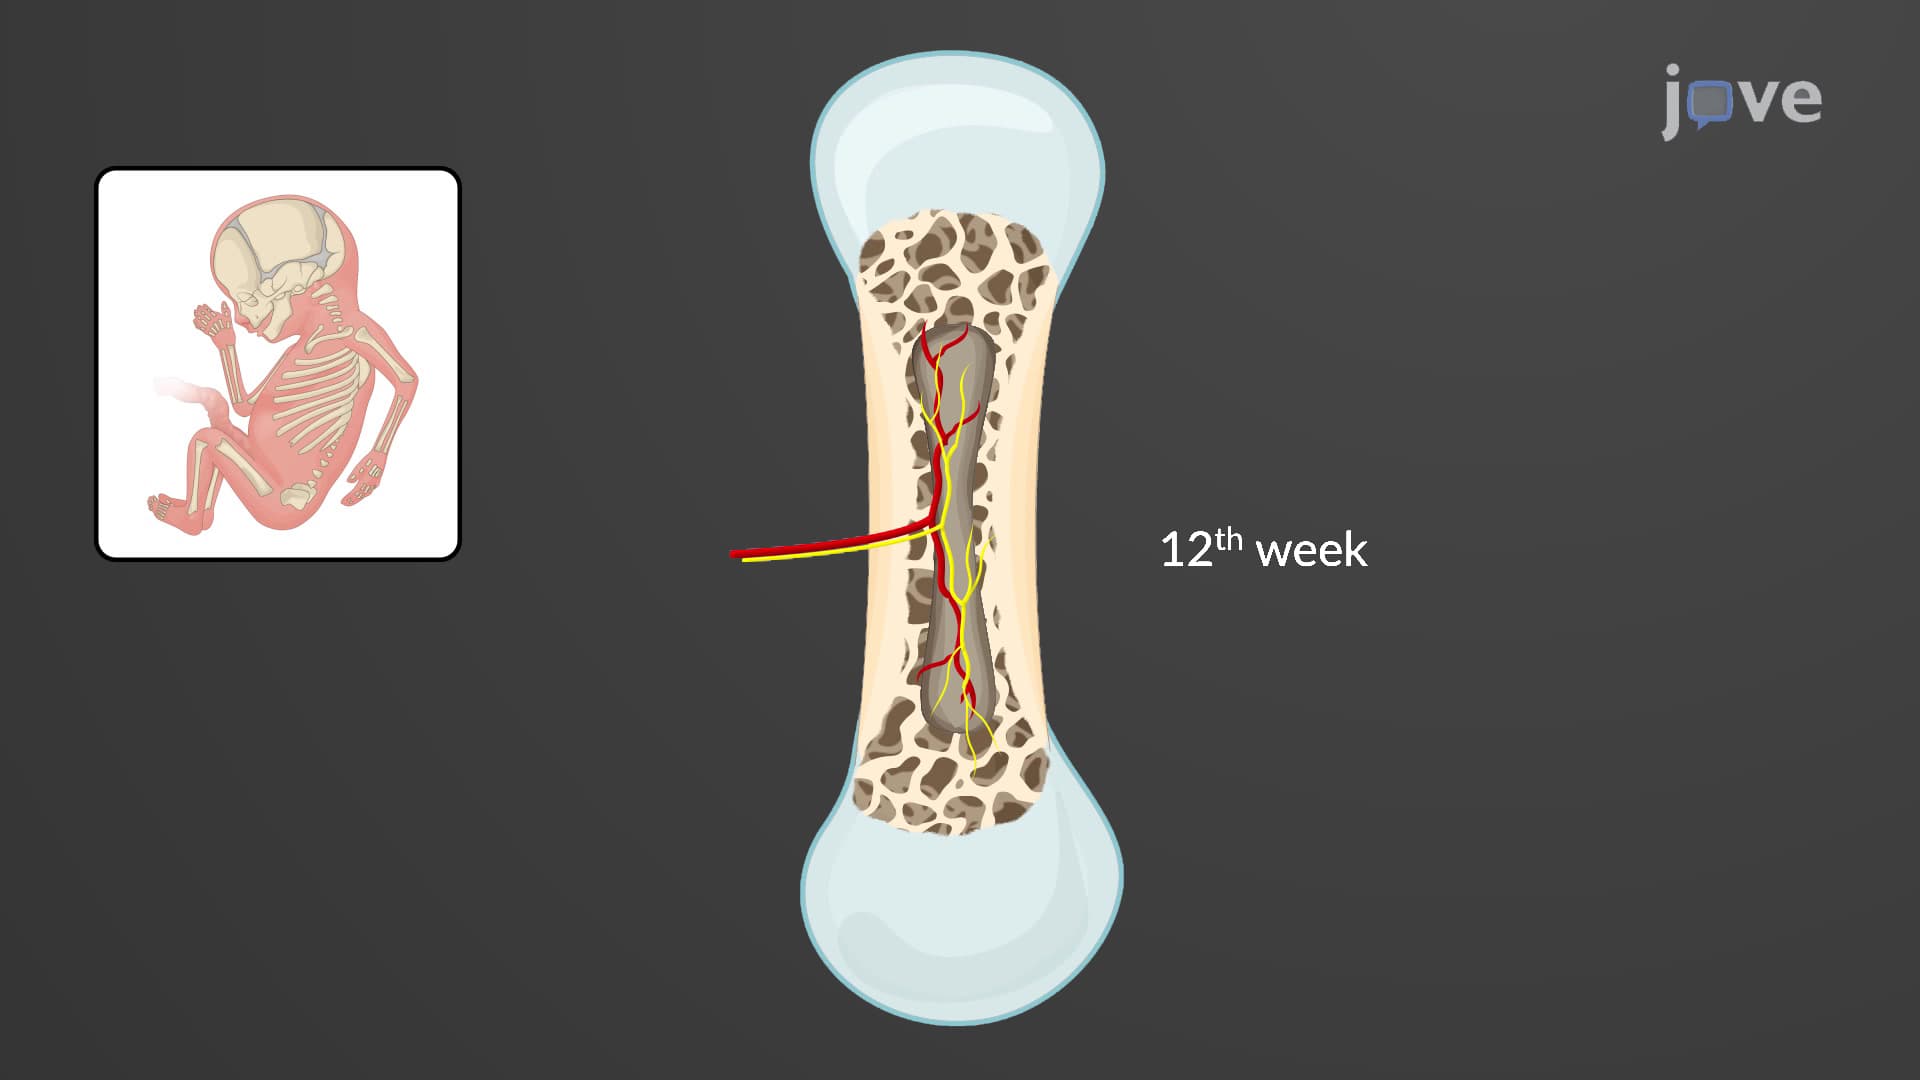 01:24
Bone Formation by Endochondral Ossification
 01:31
Osteoclasts in Bone Remodeling
 01:40
Bone Remodeling
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...