Related Experiment Video
Updated: Aug 18, 2026
Dural Stimulation and Periorbital von Frey Testing in Mice As a Preclinical Model of Headache
Published on: July 29, 2021
Mechanisms behind postspinal headache and brain stem compression following lumbar dural puncture--a physiological
1Department of Anesthesia and Intensive Care, University and University Hospital of Lund, SE-221 85 Lund, Sweden. per-olof.grande@mphy.lu.se

Background:
The cause of postspinal headache and its specific characteristics are unknown, and whether lumbar dural puncture (LP) triggers brain-stem compression in patients with brain oedema is still controversial.
Methods:
Hydrostatic effects of distal opening of the dural sac towards the atmosphere are described and applied to the normal brain and the brain with disrupted BBB. Analogue analyses from previous results using an isolated skeletal muscle enclosed in a rigid shell were applied to the brain in an attempt to simulate and verify the haemodynamic effects of distal opening of the spinal canal.
Results:
The theoretical considerations and the experimental results are compatible with the hypothesis that hydrostatic effects of distal opening of the fluid-filled spinal canal may obliterate the normal subdural venous collapse after a change from the horizontal to vertical position, which may be compatible with postural postspinal headache as occurring close to pain-sensitive meningeal regions. The hydrostatic forces may also initiate transcapillary filtration and aggravate oedema when permeability is increased, which may cause a narrower situation in the brain stem region, perhaps aggravated by venous stasis and a Cushing reflex-induced increase in blood pressure. An magnetic resonance imaging (MRI) picture illustrates how this scenario may separate the subdural space into an upper high- and a lower low-pressure cavity, pressing the brain downwards with sagging of the brain. A life-threatening positive feedback situation for brain-stem compression may develop.
Conclusion:
The present study strongly suggests that postspinal headache and brain-stem compression and other LP-related effects are predictable following LP, without involving CSF leakage, and can be explained by hydrostatic effects triggered by distal opening of the normally closed dural space to the atmosphere.
More Related Videos
 06:18
A Bedside, Single Burr Hole Approach to Multimodality Monitoring in Severe Brain Injury
Published on: March 26, 2019
 04:33
Spinal Hernia Repair and Cauda Equina Repositioning After Lumbar Decompression under Three-Dimensional Microscopy: A Case Report and Literature Review
Published on: November 8, 2024
Related Concept Videos
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:14
Increased Intracranial Pressure l: Introduction
 01:14
Spinal Cord Injury ll: Pathophysiology
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:23
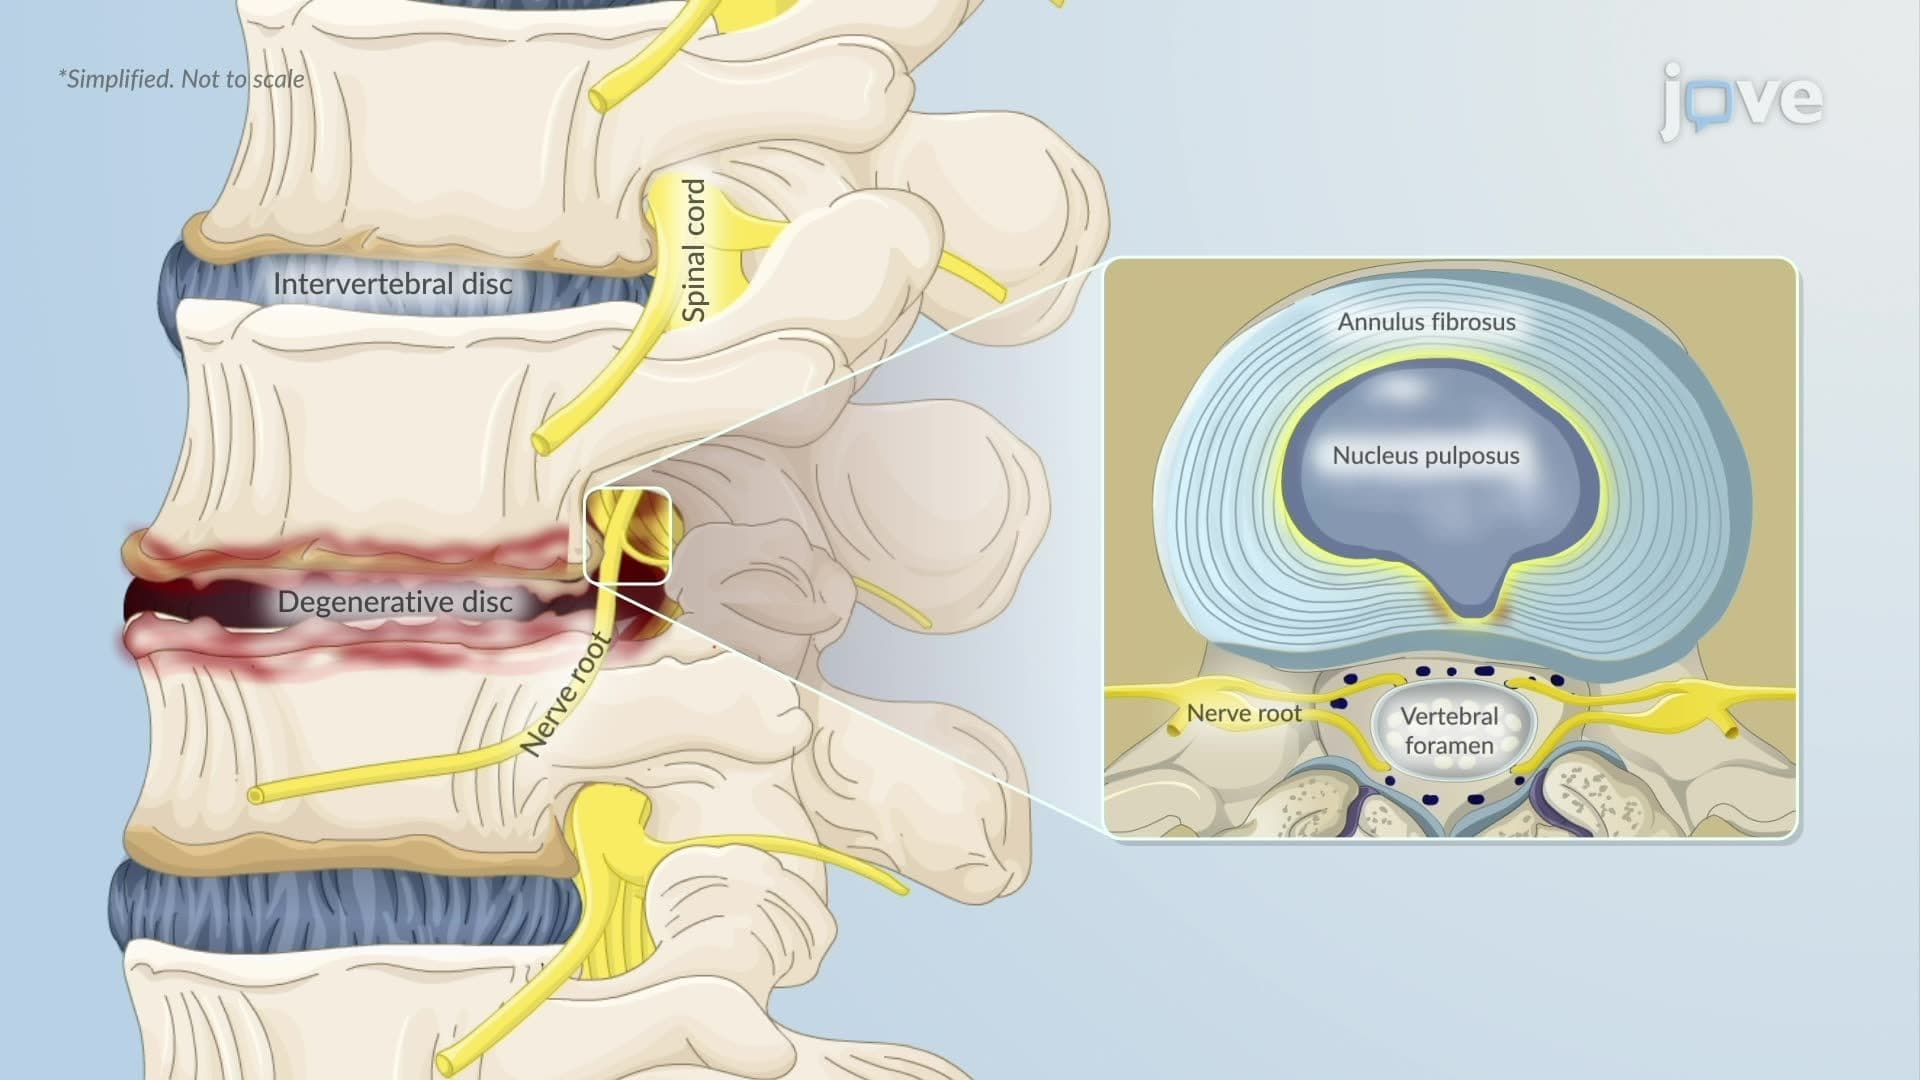
Degenerative Disc Disease ll: Pathophysiology
 01:22
Cerebral Edema ll: Pathophysiology