Related Experiment Video
Updated: Aug 18, 2026

Analysis of Cerebral Vasospasm in a Murine Model of Subarachnoid Hemorrhage with High Frequency Transcranial Duplex Ultrasound
Published on: June 3, 2021
Human middle cerebral artery flow velocity during controlled hypotension combined with hemodilution-transcranial
Makoto Fukusaki1, Masato Kanaide, Chiaki Inadomi
1Department of Anesthesia, Nagasaki Rosai Hospital, Sasebo 857-0134, Japan. fukusaki@na-robyo.jp

Study Objective:
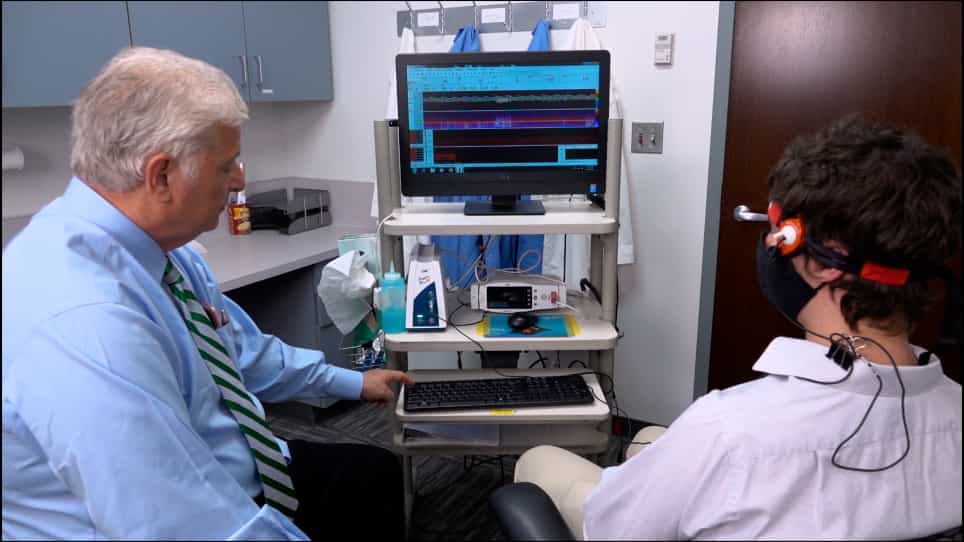
To evaluate the effects of controlled hypotension combined with hemodilution on human middle cerebral artery flow velocity (Vmca) by transcranial Doppler ultrasonography.
Design:
Randomized prospective study.
Setting:
Inpatient surgery at Nagasaki Rosai Hospital.
Patients:
Thirty American Society of Anesthesiologists physical status I and II patients scheduled for total hip arthroplasty.
Interventions:
Anesthesia was maintained with nitrous oxide-oxygen (N(2)O-O(2)) and sevoflurane during normocapnia. Hemodilution was carried out after induction of anesthesia, in which blood was withdrawn then replaced with the same amount of hydroxyethyl starch to achieve a final hematocrit level of 32% (group A = mild hemodilution group, N = 15) or 24% (group B = moderate hemodilution group, N = 15). In both groups, controlled hypotension was induced with prostaglandin E(1) to maintain mean arterial pressure at approximately 55 mm Hg for 80 minutes.
Measurements And Main Results:
Vmca and blood gas were measured before hemodilution, after hemodilution, 80 minutes after starting hypotension, and 60 minutes after recovery from hypotension. Vmca significantly increased in group A (+122%) and group B (+156%) after each hemodilution. In group B, Vmca was significantly greater than baseline values at 80 minutes after starting hypotension (+135%) and 60 minutes after recovery from hypotension (+140%).
Conclusion:
The combination of moderate hemodilution, such as hematocrit value of 24%, and prostaglandin E(1)-induced hypotension would not impair middle cerebral artery flow during sevoflurane-N(2)O-O(2) anesthesia during normocapnia.