Related Experiment Video
Updated: Aug 17, 2026
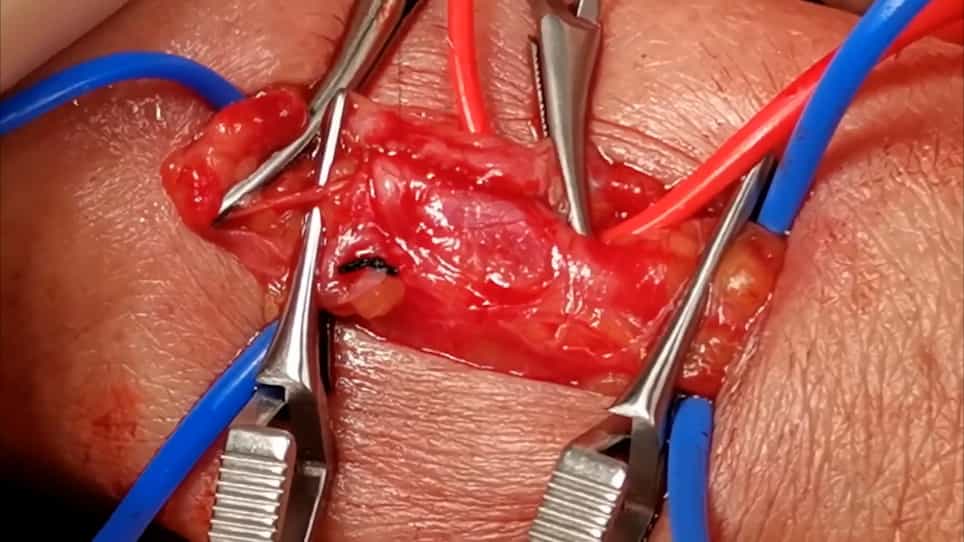

Creating Radio-cephalic Arteriovenous Fistula in the Forearm with a Modified No-Touch Technique
Published on: April 1, 2022
Role of radial artery graft in coronary artery bypass grafting
Lokeswara Rao Sajja1, Gopichand Mannam, Narasinga Rao Pantula
1Division of Cardiothoracic Surgery, Care Hospital, The Institute of Medical Sciences, Banjara Hills, Hyderabad, India. sajjal4@yahoo.com

The use of the radial artery (RA) as a coronary artery bypass graft has assumed a revival and thus a multitude of issues have arisen surrounding the routine and widespread use of this conduit in myocardial revascularization. There has been no uniformity regarding harvest techniques, assessment of the adequacy of hand collateral circulation, antispasm protocols, selection of target vessels, and the site of proximal anastomosis. It is widely believed and practiced that the RA should be harvested as a pedicle graft and preferably be used to bypass critically stenosed (>70% stenosis) coronary arteries. It is used either as a free graft with proximal anastomosis to the ascending aorta or as a composite arterial graft along with the left or right internal thoracic artery. The patency of RA grafts depends on the severity of the target coronary artery stenosis and target artery location rather than its use as an aortocoronary conduit or composite graft. In this article, we reviewed the current knowledge regarding the use of RA grafts as a coronary bypass conduit in an attempt to suggest a few acceptable strategies concerning the above issues in a given clinical scenario.
The use of the radial artery (RA) as a coronary artery bypass graft has assumed a revival and thus a multitude of issues have arisen surrounding the routine and widespread use of this conduit in myocardial revascularization. There has been no uniformity regarding harvest techniques, assessment of the adequacy of hand collateral circulation, antispasm protocols, selection of target vessels, and the site of proximal anastomosis. It is widely believed and practiced that the RA should be harvested as a pedicle graft and preferably be used to bypass critically stenosed (>70% stenosis) coronary arteries. It is used either as a free graft with proximal anastomosis to the ascending aorta or as a composite arterial graft along with the left or right internal thoracic artery. The patency of RA grafts depends on the severity of the target coronary artery stenosis and target artery location rather than its use as an aortocoronary conduit or composite graft. In this article, we reviewed the current knowledge regarding the use of RA grafts as a coronary bypass conduit in an attempt to suggest a few acceptable strategies concerning the above issues in a given clinical scenario.
Related Concept Videos
 01:11
Assessment of radial pulse
The radial pulse, located at the wrist, is often the preferred site for assessing peripheral pulse because of its accessibility and dependability. The process of determining the radial pulse involves several steps:
 01:12
Arteries of the Upper Limbs
 01:25
Assessment of apical radial pulse
The A-R pulse assessment involves simultaneous evaluation of the apical and radial pulses. When the apical and radial pulse rates vary, this assessment helps identify a pulse deficit.
Pre-Procedural Preparation