Related Experiment Video
Updated: Aug 17, 2026


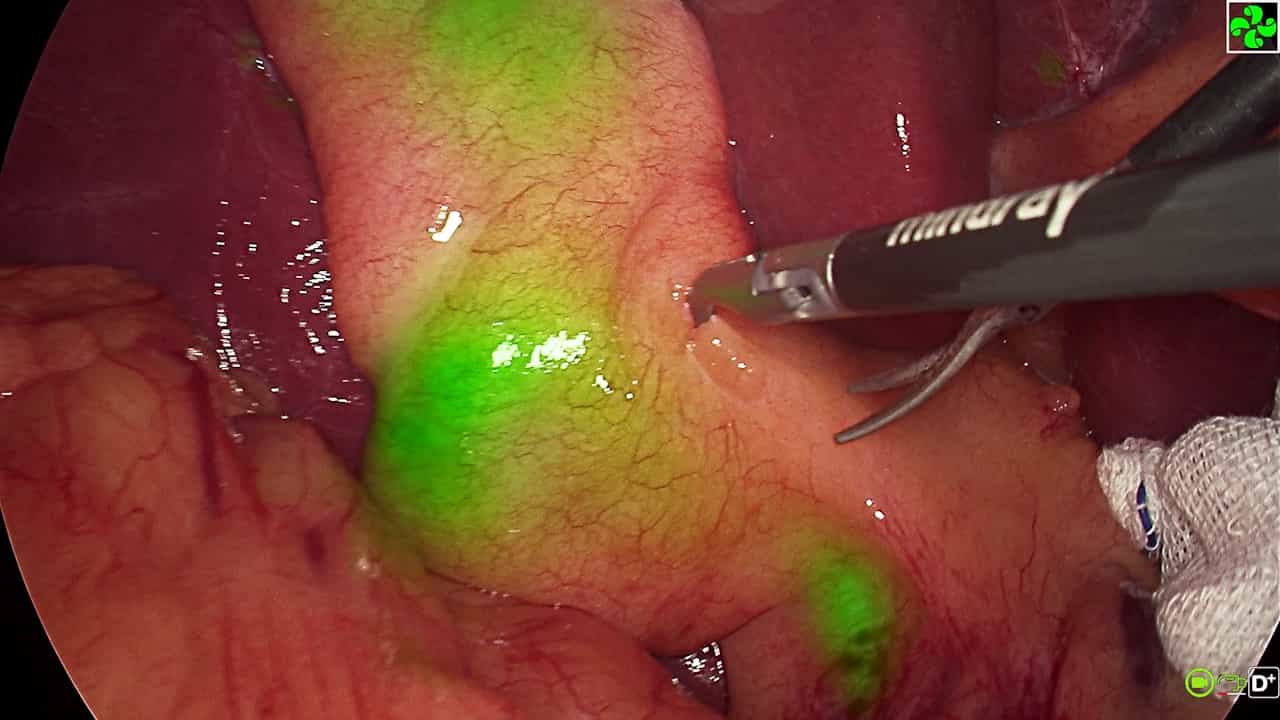
Laparoscopic Choledochal Cyst Excision and Roux-en-Y Choledochojejunostomy in Adults
Published on: February 28, 2025
Emergent biliary drainage for choledochal cyst
Shigeru Ueno1, Hitoshi Hirakawa, Seishichi Yokoyama
1Department of Pediatric Surgery, Tokai University School of Medicine, Bohseidai, Isehara-shi, Kanagawa 259-1193, Japan. ps-uenos@is.icc.u-tokai.ac.jp

Insights
Emergent biliary drainage is crucial for pediatric choledochal cyst patients experiencing complications like rupture or hypoproteinemia. Definitive surgery offers a long-term solution, but emergent drainage provides immediate safety.
Area of Science:
- Pediatric Surgery
- Gastroenterology
- Hepatobiliary Medicine
Background:
- Choledochal cysts are congenital bile duct anomalies requiring management.
- Complications such as cyst rupture and hypoproteinemia necessitate urgent intervention.
Observation:
- Case 1: A 21-month-old girl with choledochal cyst presented with spontaneous rupture, managed by emergent T-tube drainage.
- Case 2: A 29-month-old boy with choledochal cyst and hypoproteinemia showed improved serum protein levels after bile drainage via Foley catheter.
Findings:
- Emergent biliary drainage effectively manages acute complications in pediatric choledochal cyst patients.
- Protein plugs causing cyst expansion and portal hypertension leading to protein loss were implicated in the presented cases.
Implications:
- Bile drainage is a safer emergency measure compared to immediate reconstructive surgery for complicated choledochal cysts.
- Definitive surgical management, including excision and hepaticojejunostomy, is successful but carries risks, necessitating individualized treatment strategies.
Abstract:
Two patients with choledochal cyst who needed an emergent biliary drainage are presented. Case 1: Spontaneous rupture of the cyst was demonstrated by hepatobiliary scintigram in a 21-month-old girl and an emergent T-tube drainage relieved her symptom. Acute obstruction by protein plugs was considered to have caused rapid expansion of the cyst, which resulted in rupture eventually. Case 2: Marked hypoproteinemia was demonstrated in a 29-month-old boy with choledochal cyst. Bile drainage through Foley catheter promptly made the serum protein level elevated above normal range. Portal hypertension due to severely dilated cyst may have increased ascites amount, which caused extracellular fluid shift and protein to be lost into ascites. In both cases the excision of the extrahepatic bile duct and hepaticojejunostomy was carried out successfully later. Treatment of 20 pediatric cases in our institute and the literature were reviewed. Bile drainage would be safer in emergency condition even though it has been suggested that reconstructive surgery may be tolerable. Definitive surgery should be regarded as a procedure with some risk of postoperative complications because asymptomatic cases operated electively had serious ones. Treatment strategy of patients with choledochal cyst is not straightforward and should be arranged based upon their conditions.
Related Concept Videos
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:20
Cholecystitis