Related Experiment Video
Updated: Aug 17, 2026
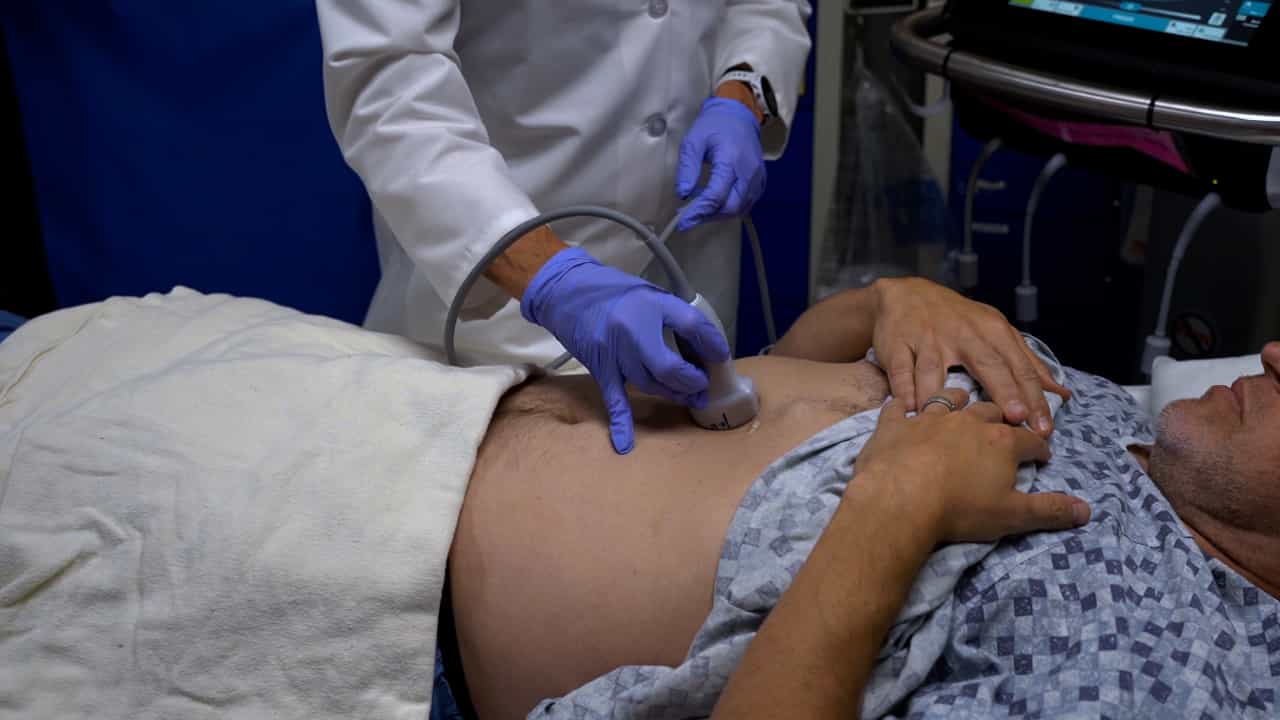
Gastric Point of Care Ultrasound in Adults: Image Acquisition and Interpretation
Published on: September 22, 2023
A patient with abdominal distension
1Department of Internal Medicine, Radboud University Nijmegen Medical Centre, Nijmegen, The Netherlands. F.Vos@AIG.umcn.nl

Abstract:
A 74-year-old woman was admitted to our hospital because of vomiting and abdominal pain. She had been well until 24 hours before admission, when she had had her last meal. She had not eaten anything unusual. She developed pain in the left lower abdominal quadrant, and difficulties with her bowel movements. An enema was given unsuccessfully. There was progressive distension of the abdomen. The patient started to vomit gastric and later bilious contents. No history of abdominal symptoms or weight loss was reported. She currently takes oral antidiabetic agents and an angiotensin II blocker because of hypertension. On physical examination she was not in distress and was afebrile, blood pressure 130/100 mmHg, pulse rate 88 beats/min. On auscultation increased bowel sounds with rushes of high-pitched sounds were heard. Her abdomen was distended and a large tender mass filling the whole left lower quadrant without signs of peritoneal irritation was found. There were no faeces on rectal examination. The leucocyte count was 10.2 mmol/L, haemoglobin 7.2 mmol/L, C-reactive protein 36 mg/l and lactate dehydrogenase 535 U/l. Under suspicion of a mechanical bowel obstruction without signs of peritonitis, the patient was treated with a nasogastric tube, fasting and enemas on which she improved. An abdominal X-ray in bed taken on day two showed no bowel distension (figure 1). After removing the nasogastric tube on day two the nausea returned. Abdominal examination was unchanged. An abdominal computed tomography (CT) scan after drinking oral contrast and intravenous contrast was performed (figure 2).
Related Concept Videos
 01:23
Assessment of the Abdomen III: Palpation
 01:07
Intestinal Obstruction II: Pathophysiology
 01:22
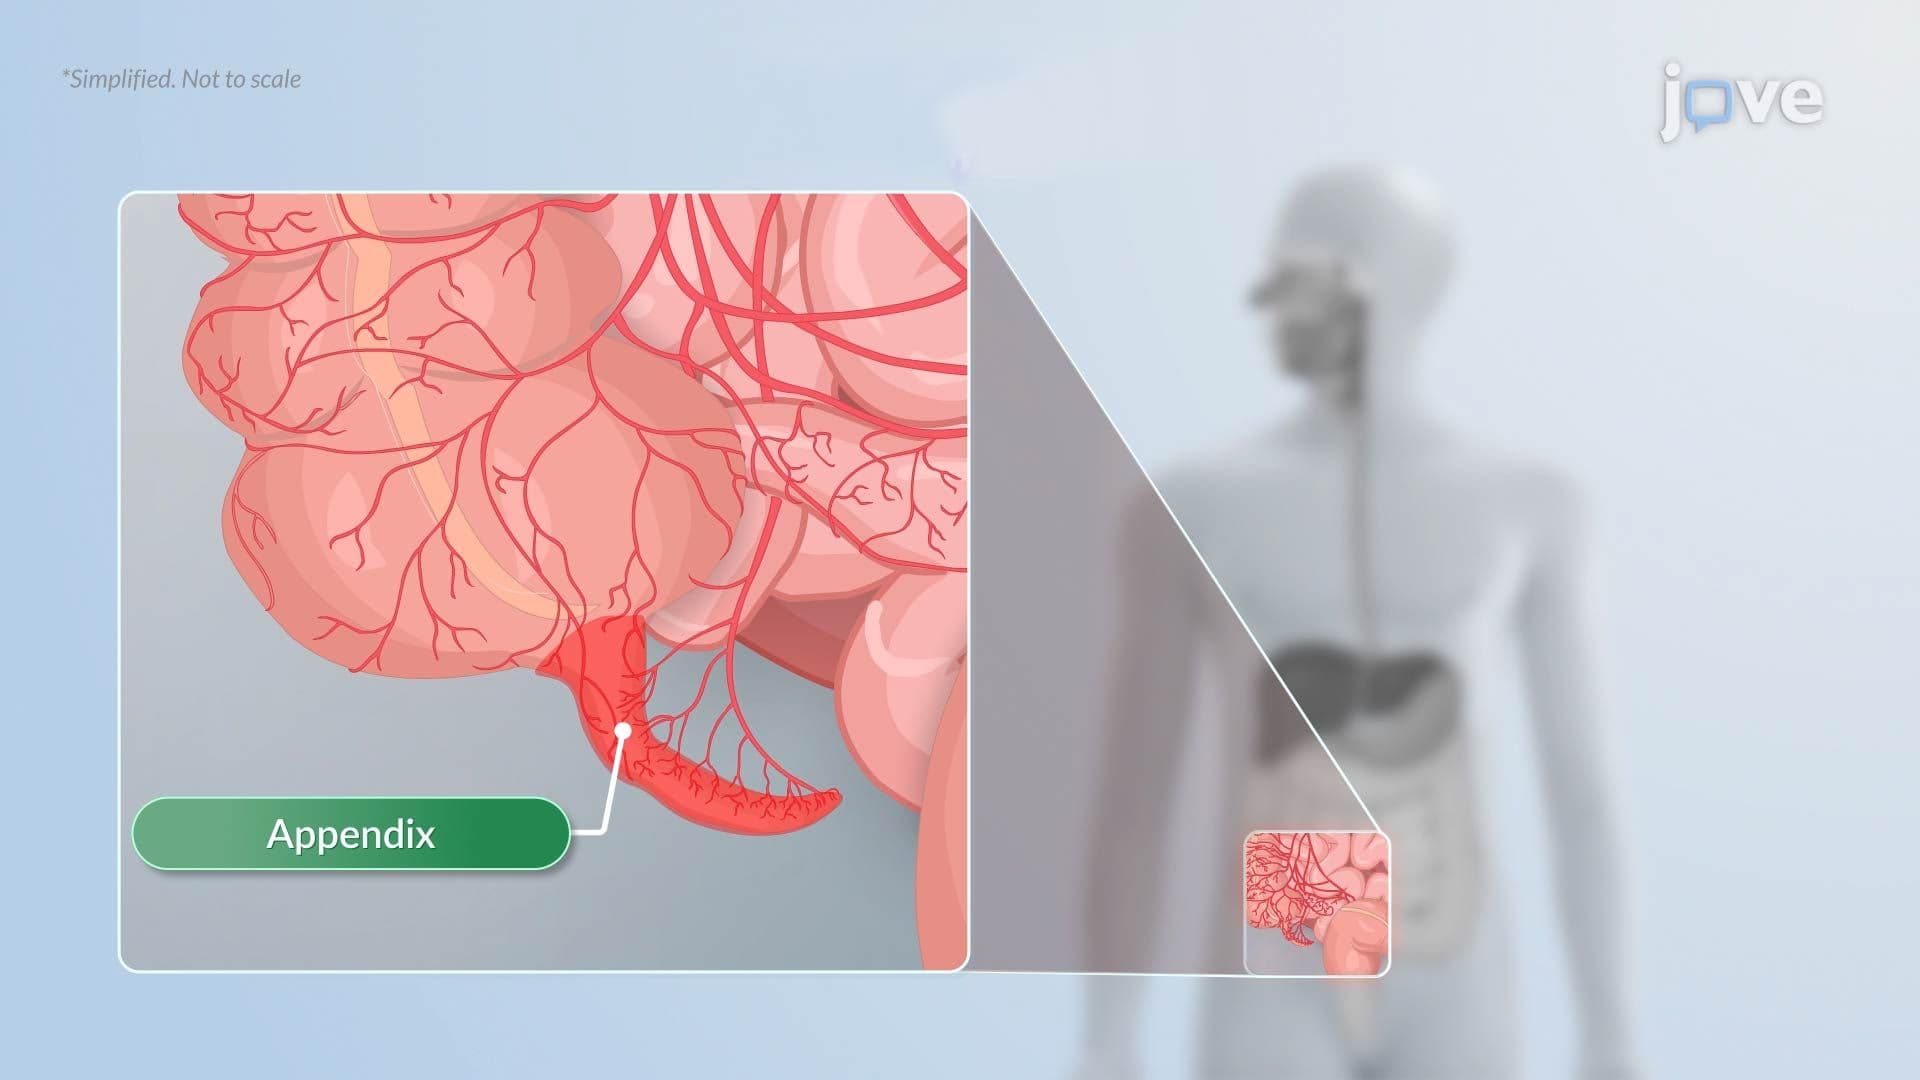
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:19
Appendicitis
 01:25
Assessment of the Abdomen I: Inspection and Auscultation
The abdominal examination is a cornerstone of clinical medicine, serving as a critical tool in diagnosing various gastrointestinal (GI) diseases. It involves a systematic approach that includes inspection and auscultation, each with distinct yet complementary roles in assessing the abdomen. This article will delve into these two primary methods healthcare professionals use to examine the abdomen.
Inspection of the Abdomen
The first step in any abdominal examination is inspection.
 01:11
Pyloric Obstruction