Related Experiment Video
Updated: Aug 11, 2026
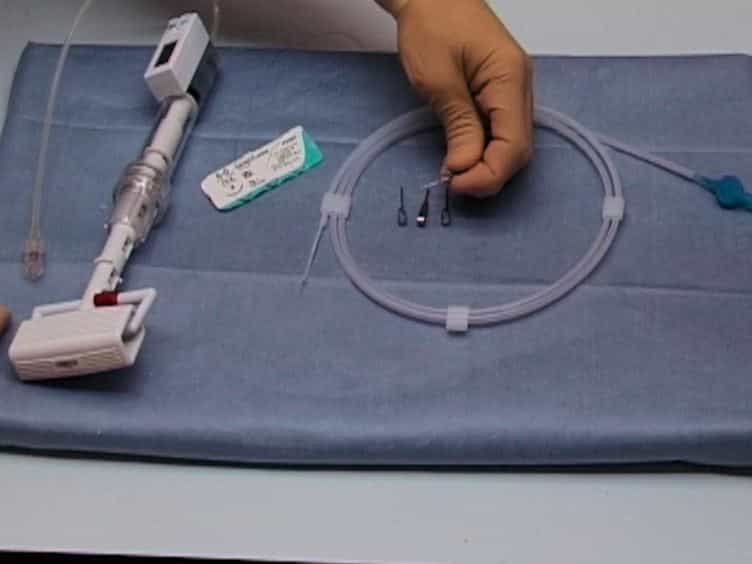

A New Murine Model of Endovascular Aortic Aneurysm Repair
Published on: July 7, 2013
Is endovascular therapy the preferred treatment for all visceral artery aneurysms?
Stephanie S Saltzberg1, Thomas S Maldonado, Patrick J Lamparello
1Division of Vascular Surgery, New York University Medical Center, New York, NY, USA. stephanie.saltzberg@med.nyu.edu

Endovascular intervention can provide an alternative method of treatment for visceral artery aneurysms. We conducted a retrospective review of all patients with visceral artery aneurysms at a single university medical center from 1990 to 2003, focusing on the outcome of endovascular therapy. Sixty-five patients with visceral artery aneurysms were identified: 39 splenic (SAA), 13 renal, seven celiac, three superior mesenteric (SMA), and three hepatic. Eleven patients (16.9%) had symptoms attributable to their aneurysms, which included a total of four ruptures (6.2%): three splenic and one hepatic. Management consisted of 18 (27.7%) endovascular interventions, nine (13.9%) open surgical repairs, and 38 (58.5%) observations. Mean aneurysm diameter for patients treated expectantly was significantly less than for those who underwent intervention (p = 0.001). Endovascular interventions included 15 (83.3%) embolizations (11 SAA, three renal, one hepatic) and three (16.7%) stent grafts (two SMA, one renal). The initial technical success rate of the endovascular procedures was 94.4% (17/18). However, there were four patients (22.2%) with major endovascular procedure-related complications: one late recurrence requiring open surgical repair, two large symptomatic splenic infarcts, and one episode of severe pancreatitis. These four patients had distal splenic artery aneurysms at or adjacent to the splenic hilum. There were no endovascular procedure-related deaths. Reasons for performing open surgical repair included three SAA ruptures diagnosed at laparotomy and complex anatomy not amenable to endovascular intervention (six patients). One surgical patient had a postoperative small bowel obstruction treated nonoperatively; and there was one perioperative death in a patient operated on emergently for rupture. Endovascular management of visceral artery aneurysms is a reasonable alternative to open surgical repair in carefully selected patients. Individual anatomic considerations play an important role in determining the best treatment strategy if intervention is warranted. However, four of 11 (36.4%) patients with distal splenic artery aneurysms treated with endovascular embolization developed major complications. Based on our experience, traditional surgical treatment of SAA with repair or ligation and concomitant splenectomy when necessary may be preferred in these cases.
Endovascular intervention can provide an alternative method of treatment for visceral artery aneurysms. We conducted a retrospective review of all patients with visceral artery aneurysms at a single university medical center from 1990 to 2003, focusing on the outcome of endovascular therapy. Sixty-five patients with visceral artery aneurysms were identified: 39 splenic (SAA), 13 renal, seven celiac, three superior mesenteric (SMA), and three hepatic. Eleven patients (16.9%) had symptoms attributable to their aneurysms, which included a total of four ruptures (6.2%): three splenic and one hepatic. Management consisted of 18 (27.7%) endovascular interventions, nine (13.9%) open surgical repairs, and 38 (58.5%) observations. Mean aneurysm diameter for patients treated expectantly was significantly less than for those who underwent intervention (p = 0.001). Endovascular interventions included 15 (83.3%) embolizations (11 SAA, three renal, one hepatic) and three (16.7%) stent grafts (two SMA, one renal). The initial technical success rate of the endovascular procedures was 94.4% (17/18). However, there were four patients (22.2%) with major endovascular procedure-related complications: one late recurrence requiring open surgical repair, two large symptomatic splenic infarcts, and one episode of severe pancreatitis. These four patients had distal splenic artery aneurysms at or adjacent to the splenic hilum. There were no endovascular procedure-related deaths. Reasons for performing open surgical repair included three SAA ruptures diagnosed at laparotomy and complex anatomy not amenable to endovascular intervention (six patients). One surgical patient had a postoperative small bowel obstruction treated nonoperatively; and there was one perioperative death in a patient operated on emergently for rupture. Endovascular management of visceral artery aneurysms is a reasonable alternative to open surgical repair in carefully selected patients. Individual anatomic considerations play an important role in determining the best treatment strategy if intervention is warranted. However, four of 11 (36.4%) patients with distal splenic artery aneurysms treated with endovascular embolization developed major complications. Based on our experience, traditional surgical treatment of SAA with repair or ligation and concomitant splenectomy when necessary may be preferred in these cases.
More Related Videos


Related Concept Videos
 01:19
Anastomoses
Anastomoses can be formed at arterial, venous, and lymphatic vessels.
Arterial Anastomosis: These occur between arteries. They are most common in...
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:26
Aneurysm III: Interprofessional Care
 01:22
Aneurysm IV: Nursing Management
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:29
Venous Thrombosis III: Interprofessional Care