Related Experiment Video
Updated: Jun 23, 2026


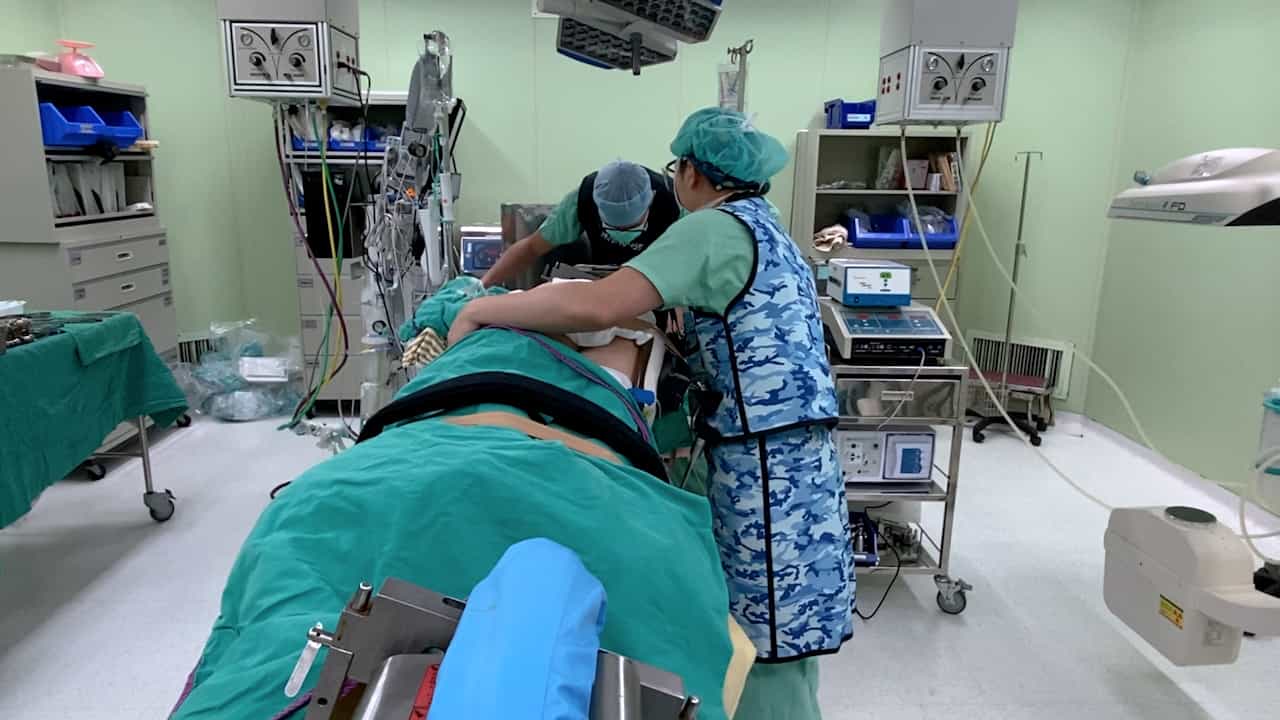
An Educational Video Demonstration of How to Prone a Critically Ill Intubated Patient
Published on: November 30, 2022
Effect of prone positioning on clinical outcomes in children with acute lung injury: a randomized controlled trial
Martha A Q Curley1, Patricia L Hibberd, Lori D Fineman
1Children's Hospital Boston, Medical-Surgical Intensive Care Unit, 300 Longwood Ave, Boston, MA 02115, USA. martha.curley@childrens.harvard.edu

Insights
Prone positioning did not improve clinical outcomes for pediatric acute lung injury patients. This study found no significant difference in ventilator-free days between prone and supine positioning.
Area of Science:
- Pediatric Critical Care Medicine
- Respiratory Medicine
- Clinical Trials
Background:
- Prone positioning has shown promise in improving oxygenation in pediatric acute lung injury (ALI) patients in uncontrolled studies.
- However, its impact on clinical outcomes in children with ALI remains unknown.
Purpose of the Study:
- To determine if prone positioning improves clinical outcomes in pediatric patients with acute lung injury.
- The primary hypothesis was that prone positioning would lead to more ventilator-free days at 28 days compared to supine positioning.
Main Methods:
- A multicenter, randomized, controlled trial involving 102 pediatric patients (2 weeks to 18 years) with ALI.
- Patients were randomized to either supine or prone positioning, with the prone group positioned for 20 hours daily for up to 7 days.
- Ventilator-free days to day 28 was the primary outcome measure.
Main Results:
- The trial was stopped early due to futility.
- No significant difference was observed in ventilator-free days between the prone and supine groups (15.6 vs 15.8 days).
- Secondary outcomes, including mortality, recovery time, organ-failure-free days, and functional health, also showed no significant differences between groups.
Conclusions:
- Prone positioning does not significantly reduce ventilator-free days in pediatric patients with acute lung injury.
- The study concludes that prone positioning does not offer clinical outcome benefits for this patient population.
Context:
In uncontrolled clinical studies, prone positioning appeared to be safe and to improve oxygenation in pediatric patients with acute lung injury. However, the effect of prone positioning on clinical outcomes in children is not known.
Objective:
To test the hypothesis that at the end of 28 days infants and children with acute lung injury treated with prone positioning would have more ventilator-free days than those treated with supine positioning.
Design, Setting, And Patients:
Multicenter, randomized, controlled clinical trial conducted from August 28, 2001, to April 23, 2004, of 102 pediatric patients from 7 US pediatric intensive care units aged 2 weeks to 18 years who were treated with supine vs prone positioning. Randomization was concealed and group assignment was not blinded.
Intervention:
Patients were randomized to either supine or prone positioning within 48 hours of meeting acute lung injury criteria, with those patients in the prone group being positioned within 4 hours of randomization and remaining prone for 20 hours each day during the acute phase of their illness for a maximum of 7 days, after which they were positioned supine. Both groups were treated using lung protective ventilator and sedation protocols, extubation readiness testing, and hemodynamic, nutrition, and skin care guidelines.
Main Outcome Measure:
Ventilator-free days to day 28.
Results:
The trial was stopped at the planned interim analysis on the basis of the prespecified futility stopping rule. There were no differences in the number of ventilator-free days between the 2 groups (mean [SD], 15.8 [8.5] supine vs 15.6 [8.6] prone; mean difference, -0.2 days; 95% CI, -3.6 to 3.2; P = .91). After controlling for age, Pediatric Risk of Mortality III score, direct vs indirect acute lung injury, and mode of mechanical ventilation at enrollment, the adjusted difference in ventilator-free days was 0.3 days (95% CI, -3.0 to 3.5; P = .87). There were no differences in the secondary end points, including proportion alive and ventilator-free on day 28 (P = .45), mortality from all causes (P>.99), the time to recovery of lung injury (P = .78), organ-failure-free days (P = .88), and cognitive impairment (P = .16) or overall functional health (P = .12) at hospital discharge or on day 28.
Conclusion:
Prone positioning does not significantly reduce ventilator-free days or improve other clinical outcomes in pediatric patients with acute lung injury.
More Related Videos

Related Concept Videos
 01:11
Anatomical Positions
The body is upright, facing forward, and standing erect.
The feet are parallel and flat on the floor.
The arms are hanging by the...
 01:23
Acute Respiratory Failure-IV