Related Experiment Video
Updated: Aug 16, 2026

03:57

Generation of Hypoparathyroid Rats via Carbon-Nanoparticle-Assisted Parathyroidectomy
Published on: July 14, 2023
Parathyroid adenoma presenting as paraneoplastic syndrome secondary to renal cell carcinoma
Kevin K Wong1, Jeffrey R Harris
1Division of Otolaryngology, Faculty of Medicine and Dentistry, University of Alberta, Edmonton.
The Journal of Otolaryngology
|July 29, 2005

Abstract
No abstract available in PubMed .
Related Concept Videos
 00:59
The Parathyroid Glands
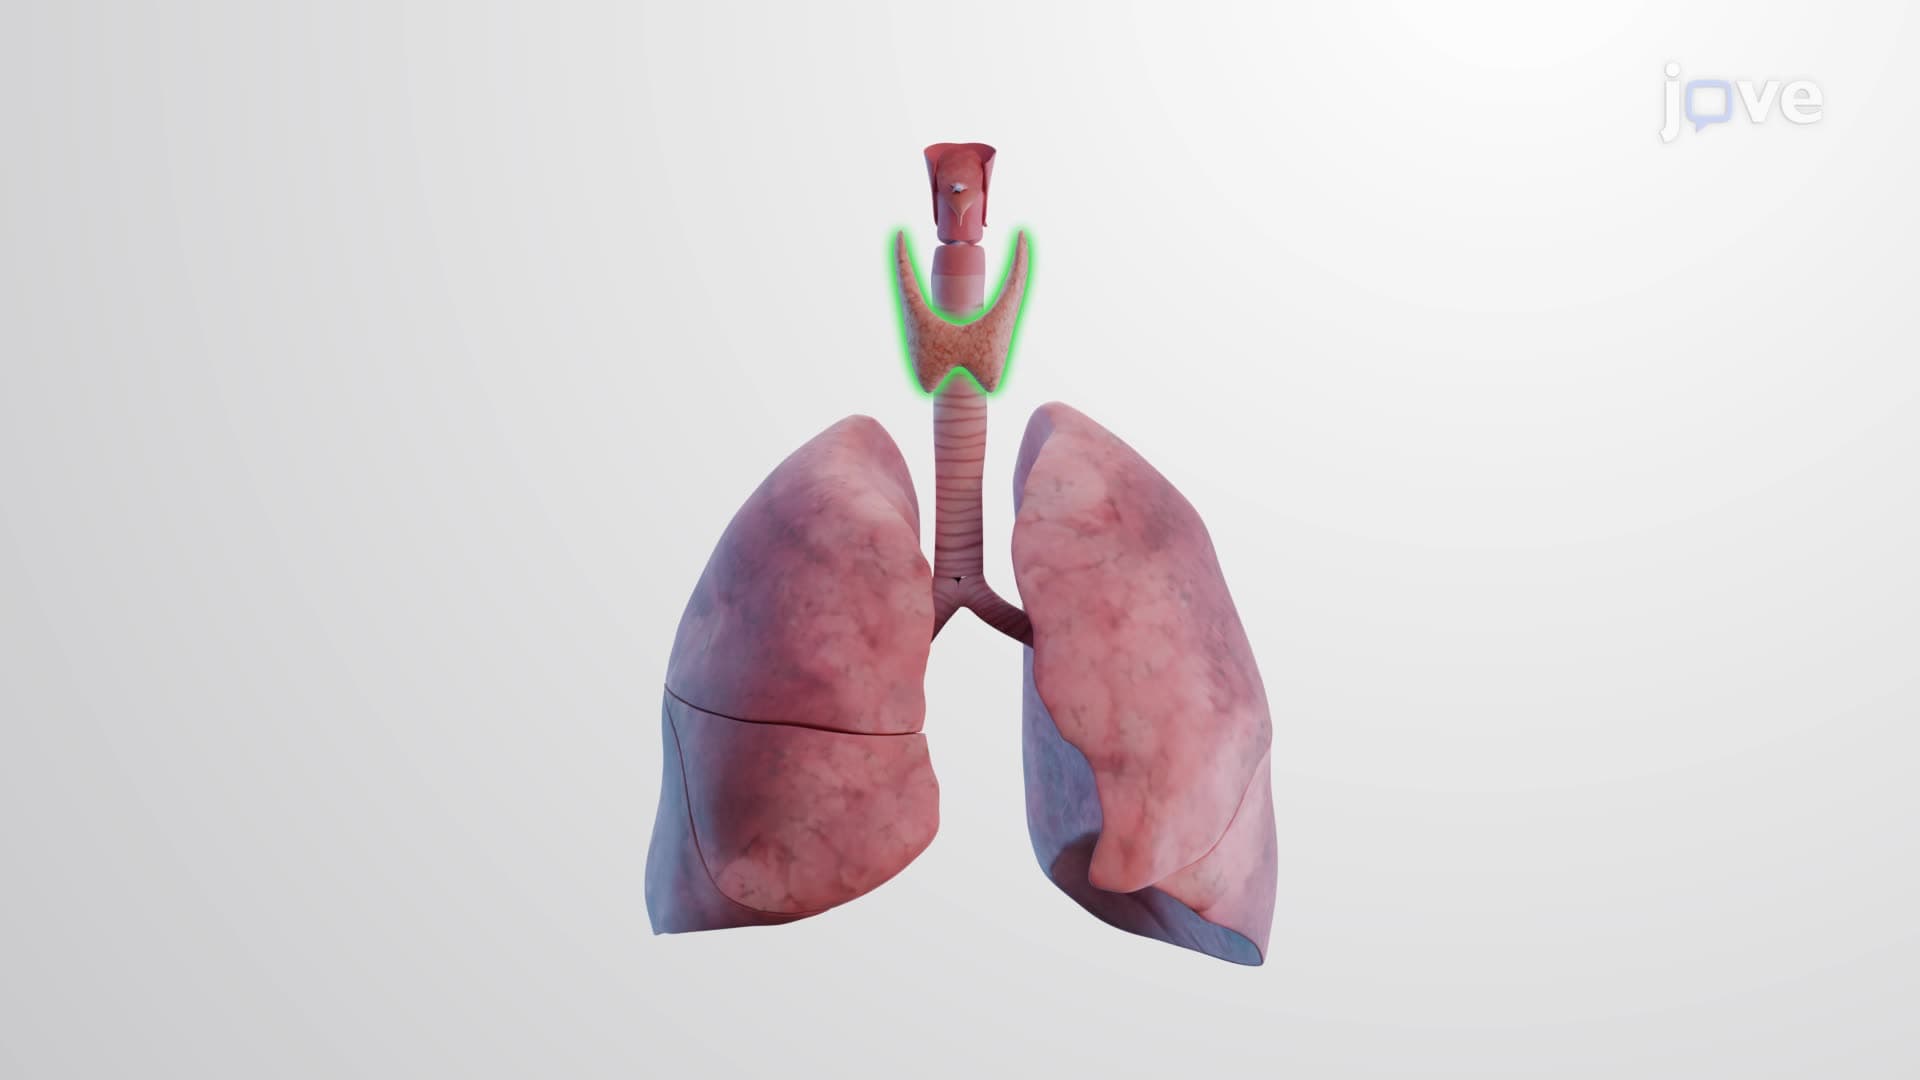
The two pairs of parathyroid glands embedded within the posterior surface of the thyroid gland are restricted by a dense capsule around them. These glands comprise two distinct cell populations—parathyroid oxyphil and parathyroid principal cells- pivotal in calcium homeostasis.
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
Renal calculi, commonly termed kidney stones, are crystalline solid masses that form in the kidneys but can occur at any point within the urinary system, encompassing the kidneys, ureters, bladder, and urethra.The pathophysiology of renal stones involves several key factors: supersaturation of the urine with stone-forming constituents, changes in urine pH, a decrease in urine volume, and the presence of substances that promote or inhibit stone formation.Supersaturation of Urine: This is the...
 01:24
Nephrotic Syndrome I : Introduction
Nephrotic Syndrome is a chronic kidney disorder defined by clinical findings such as severe proteinuria, hypoalbuminemia, hyperlipidemia, and edema. These symptoms result from damage to the glomeruli, the kidney’s filtering units, increasing their permeability to proteins.Definition and Meaning:Proteinuria, defined as the loss of more than 3.5 grams of protein per day in adults, is a crucial feature of nephrotic syndrome. This condition is often accompanied by edema, the accumulation of fluid...
 01:24
Graves Disease II: Pathophysiology
Graves’ disease is an autoimmune disorder characterized by the production of thyroid-stimulating immunoglobulins (TSI) that activate TSH receptors, leading to excessive synthesis and release of thyroid hormones (T3 and T4) and resulting in hyperthyroidism.Among all causes of hyperthyroidism, Graves’ disease is the most common and can happen at any age, though it is more frequent in women. It produces a hypermetabolic state with features such as weight loss, tachycardia, tremor, and heat...
 01:19
Cushing Syndrome II: Pathophysiology
Cortisol production is normally governed by the hypothalamic–pituitary–adrenal (HPA) axis, which maintains hormonal balance through tightly regulated feedback mechanisms. Disruption of this regulatory system is central to the development of Cushing syndrome, whether the excess cortisol originates from external medications or internal pathology. Persistent cortisol elevation alters metabolism, immune function, and endocrine signaling, producing the characteristic clinical features of the...
 01:27
Hyperthyroidism II: Pathophysiology
Hyperthyroidism is a hypermetabolic state caused by elevated levels of thyroid hormones, triiodothyronine (T3) and thyroxine (T4). It results from dysregulation at the thyroid, pituitary, or immune system level and affects multiple organ systems.PathophysiologyThe most common cause of hyperthyroidism is Graves’ disease, an autoimmune disorder in which antibodies, specifically thyroid-stimulating antibodies (TSAb), a subtype of TSH receptor antibodies (TRAb), bind to and activate TSH receptors...