Relationships among exercise capacity, hypertrophy, and left ventricular diastolic function in nonobstructive hypertrophic cardiomyopathy
Related Experiment Video
Updated: Aug 16, 2026

Scanning Electron Microscopy of Macerated Tissue to Visualize the Extracellular Matrix
Published on: June 14, 2016
Afonso Y Matsumoto1, Edmundo Arteaga, Barbara M Ianni
1Departmnet of Cardiomyopathy, Heart Institute (InCor), University of São Paulo Medical School, São Paulo, Brazil. fymatsumoto@superig.com.br

Insights
Exercise capacity in nonobstructive hypertrophic cardiomyopathy (NOHCM) is linked to diastolic function, not left ventricular hypertrophy. Relaxation changes and inadequate left ventricular filling may impair exercise capacity.
Area of Science:
- Cardiology
- Cardiovascular Physiology
Background:
- Nonobstructive hypertrophic cardiomyopathy (NOHCM) presents unique challenges in understanding its impact on patient function.
- Exercise capacity (EC) is a crucial metric for assessing functional status in cardiovascular diseases.
Purpose of the Study:
- To investigate the interrelationships between exercise capacity, left ventricular hypertrophy (LVH), and diastolic function in patients with NOHCM.
Main Methods:
- Echocardiography was used to assess LVH.
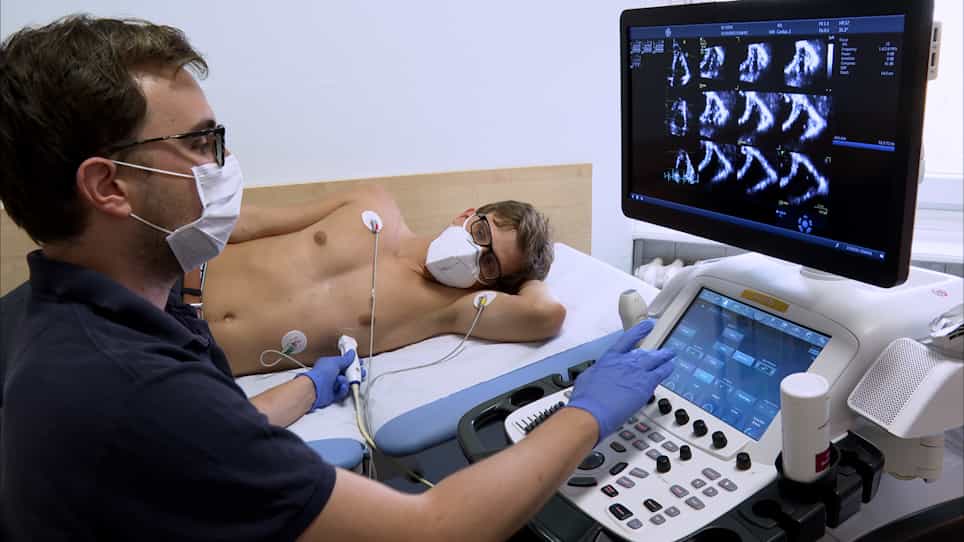
- Mitral and pulmonary vein flow, along with tissue Doppler imaging, were employed to evaluate diastolic function.
- Peak oxygen uptake (VO2) and anaerobic threshold (AT) were determined to assess EC.
Main Results:
- No significant correlation was found between EC and LVH.
- Peak VO2 and AT showed correlations with diastolic function parameters, specifically D and Ea/Aa.
- Patients exhibited evidence of elevated left ventricular end-diastolic pressure despite normal filling pressures.
Conclusions:
- Diastolic dysfunction, characterized by relaxation abnormalities and impaired left ventricular filling, appears to be a primary determinant of reduced exercise capacity in NOHCM.
- Left ventricular hypertrophy is not directly correlated with exercise limitations in this patient cohort.
Aim:
The aim of this study was to analyze the relationships among exercise capacity (EC), hypertrophy, and diastolic function in nonobstructive hypertrophic cardiomyopathy (NOHCM).
Methods And Results:
Twenty-seven patients with NOHCM were studied. Left ventricular hypertrophy (LVH) was determined by appropriate echocardiographic indexes. For diastolic function evaluation, the following were measured: the early (E) and late (A) waves, E/A, and deceleration time of E of the mitral flow; the systolic (S), diastolic (D), and atrial reversal (AR) waves, S/D, and the atrial systolic filling fraction of the pulmonary vein flow; and the early (Ea), late (Aa) waves, Ea/Aa, and E/Ea by tissue Doppler imaging. The difference between the duration of AR and A waves (DurAR - DurA), the peak VO2, and anaerobic threshold (AT) were also determined. In these patients, the E/Ea ratio was 8.9 +/- 3.2 and DurAR - DurA was 22.6 +/- 32.6 milliseconds. The peak VO2 and AT correlated with D (r = 0.55, P = .003 and .51, P = .007, respectively) and Ea/Aa (r = 0.56, P = .007 and .45, P = .03, respectively). There was no correlation between EC and LVH.
Conclusions:
Patients with NOHCM demonstrated evidences of elevated left ventricular (LV) end-diastolic pressure with normal filling pressure. EC compromise may be attributed to relaxation changes with inadequate filling of the left ventricle.
More Related Videos

Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Heart Failure II: Pathophysiology
 01:29
Cardiomyopathy V: Interprofessional Care
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy