Related Experiment Video
Updated: Aug 9, 2026
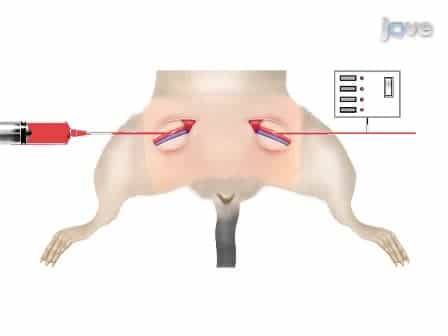

Fixed Volume or Fixed Pressure: A Murine Model of Hemorrhagic Shock
Published on: June 6, 2011
Pre-hospital fluid therapy in the critically injured patient--a clinical update
Eldar Søreide1, Charles D Deakin
1Division of Acute Care Medicine, Stavanger University Hospital, Stavanger, Norway. soed@sir.no

Abstract:
Venous access and fluid therapy should still be considered to be essential elements of pre-hospital advanced life support (ALS) in the critically injured patient. Initiation of fluid therapy should be based on a clinical assessment, most importantly the presence, or otherwise, of a radial pulse. The goal in penetrating injury is to avoid hypovolaemic cardiac arrest during transport, but at the same time not to delay transport, or increase systolic blood pressure. The goal in blunt injury is to secure safe perfusion of the injured brain through an adequate cerebral perfusion pressure, which generally requires a systolic blood pressure well above 100 mmHg. Patients without severe brain injury tolerate lower blood pressures (hypotensive resuscitation). Importantly, using systolic blood pressure targets to titrate therapy is not as easy as it seems. Automated (oscillometric) blood pressure measurement devices frequently give erroneously high values. The concept of hypotensive resuscitation has not been validated in the few studies done in humans. Hence, the suggested targeted systolic blood pressures should only provide a mental framework for the decision-making. The ideal pre-hospital fluid regimen may be a combination of an initial hypertonic solution given as a 10-20 minutes infusion, followed by crystalloids and, in some cases, artificial colloids. This review is intended to help the clinician to balance the pros and cons of fluid therapy in the individual patient.

Related Concept Videos
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:22
Heart Failure VI: Adjunct Therapies
 01:30
Continuous Renal Replacement Therapy
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:22
Acute Kidney Injury VI: Nursing Management