Related Experiment Video
Updated: Aug 16, 2026
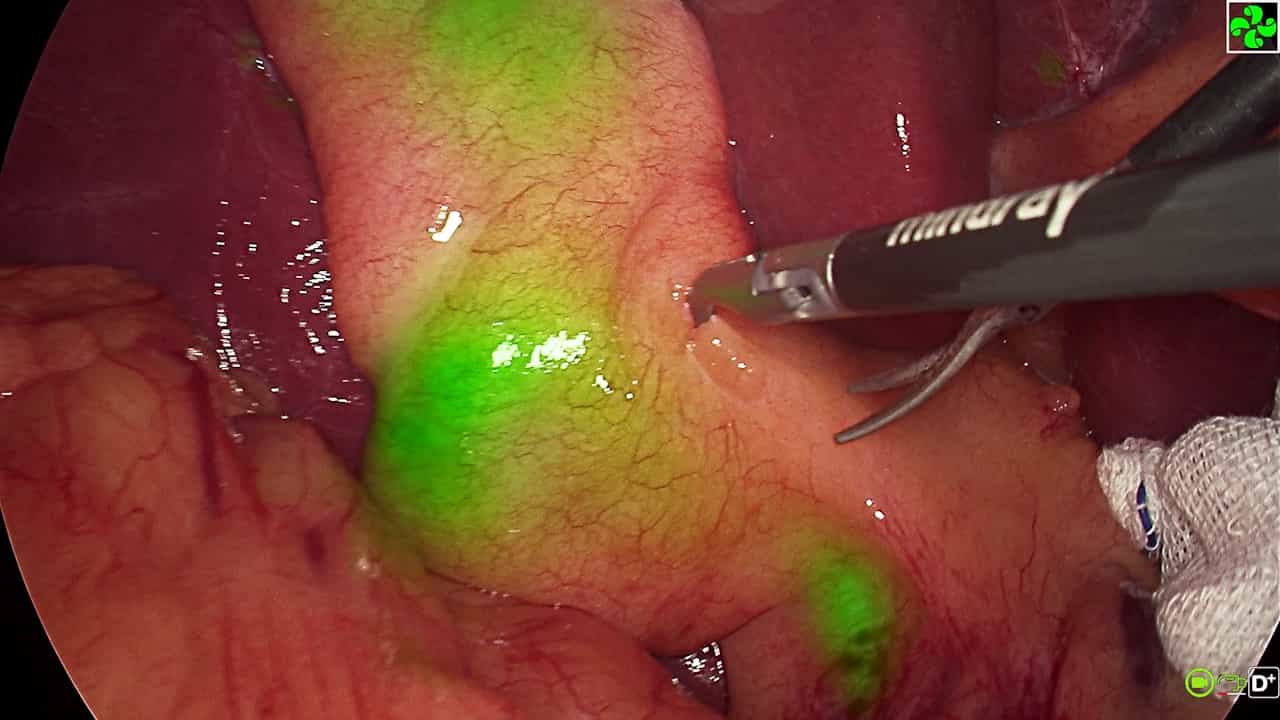

Laparoscopic Cholecystectomy with Indocyanine Green Fluorescence: Choledochoscopic Stone Extraction and Primary Duct Suture
Published on: November 25, 2025
Elective laparoscopic cholecystectomy for symptomatic gallstone disease in patients receiving anticoagulant therapy
Emmanuel Leandros1, Ilias P Gomatos, Panagoula Mami
1Laparoendoscopic Unit, Hippokrateion Hospital of Athens, Athens, Greece.

Insights
Elective laparoscopic cholecystectomy (LC) is safe for patients on anticoagulant therapy with cardiovascular conditions. Careful adjustment of cardiopulmonary and coagulation parameters ensures successful outcomes in this patient group.
Area of Science:
- Cardiovascular Surgery
- Gastroenterology
- Anesthesiology
Background:
- Laparoscopic cholecystectomy (LC) is a safe procedure for patients with various pre-existing conditions.
- The study investigates the safety and applicability of elective LC in patients with cardiovascular conditions undergoing anticoagulant therapy.
Purpose of the Study:
- To evaluate the safety and feasibility of elective laparoscopic cholecystectomy (LC) in patients with pre-existing cardiovascular conditions who are on anticoagulant treatment.
Main Methods:
- A cohort of 33 patients on long-term anticoagulant therapy for cardiovascular conditions underwent elective LC.
- A control group of 33 non-anticoagulated patients matched for age and sex was used for comparison.
- Patient data included valve replacement history, atrial fibrillation, deep vein thrombosis, pulmonary embolism, and dilated cardiomyopathy.
Main Results:
- No intraoperative or postoperative mortality or morbidity was observed in the anticoagulated group.
- Mean LC duration was similar between anticoagulated and control groups (63.6 vs. 64.9 minutes).
- Anticoagulated patients were mobilized by postoperative day 1, with a mean hospital stay of 3.6 days, which was significantly longer than the control group (1.5 days).
Conclusions:
- Elective laparoscopic cholecystectomy (LC) is a safe procedure for patients with severe cardiovascular disease requiring anticoagulant therapy.
- Careful, individualized adjustment of cardiopulmonary and coagulation parameters is crucial for successful outcomes.
Background:
The safety of laparoscopic cholecystectomy (LC) has been proven in patients with several pre-existing clinical conditions. This study was conducted to evaluate the applicability and safety of elective LC in patients with pre-existing cardiovascular conditions who were receiving anticoagulant treatment.
Patients And Methods:
Between January 1998 and December 2002, 33 patients preoperatively receiving long-term anticoagulant therapy for pre-existing disease were scheduled to undergo elective LC for symptomatic gallstone disease in our laparoendoscopic unit. The study group included 19 patients with one valve replacement (57.6%), 1 patient (3%) with two valves replaced, and 1 patient (3%) with three cardiac valves replaced. There were also 9 patients (27.3%) suffering from chronic atrial fibrillation, 1 patient (3%) with a history of deep vein thrombosis, 1 patient with a history of pulmonary embolism, and 1 patient with dilated cardiomyopathy and systemic lupus erythematosous (SLE). Thirty-three non-anticoagulated patients matched for age and sex who were scheduled for elective LC in our department during the same period served as the control group.
Results:
There was no intraoperative or postoperative mortality or morbidity in our series. The mean duration of the LC did not differ significantly between the anticoagulated and control groups (63.6 minutes vs. 64.9 minutes, P=0.643). All anticoagulated patients were mobilized by postoperative day 1 and were discharged from the hospital in a mean 3.6+/-0.8 days (median, 3 days; range, 3-6 days) after an uneventful postoperative course. The length of stay was significantly longer in the anticoagulated group of patients (3.6 days vs. 1.5 days in the control group, P<0.001).
Conclusion:
Elective LC can be performed safely in patients under anticoagulant therapy for severe pre-existing cardiovascular disease, as long as their cardiopulmonary and coagulation parameters are carefully individualized and adjusted.
