Related Experiment Video
Updated: Aug 16, 2026


X-ray Dose Reduction through Adaptive Exposure in Fluoroscopic Imaging
Published on: September 11, 2011
Computer calculated dose in paediatric prescribing
Richard C Kirk1, Denise Li-Meng Goh, Jeya Packia
1Department of Paediatrics, The Children's Medical Institute, National University Hospital, Singapore.

Insights
Medication errors are common in paediatric prescriptions, particularly underdosing. Computer-calculated doses significantly reduce these errors, but other factors also need attention for optimal safety.
Area of Science:
- Pediatric pharmacology
- Patient safety
- Health informatics
Background:
- Medication errors pose significant risks in pediatric hospital settings.
- Limited data exists on medication errors in pediatric outpatient, emergency, and discharge settings.
- Children are at higher risk for adverse drug events due to medication errors.
Purpose of the Study:
- To determine the frequency of medication errors in ambulatory pediatric patients.
- To evaluate the impact of computer-calculated doses on prescribing errors for paracetamol and promethazine.
Main Methods:
- Prospective cohort study in a university teaching hospital's pediatric unit.
- Comparison of traditional prescribing versus computer-calculated doses for paracetamol and promethazine.
- Analysis of 4274 prescriptions across outpatient, emergency, and discharge settings.
Main Results:
- Overall medication error rates were 15.7% (emergency), 21.5% (outpatient), and 23.6% (discharge).
- Underdosing constituted the majority of errors (64%).
- Computer-calculated doses reduced error rates to 12.6% compared to 28.2% with traditional methods.
Conclusions:
- Medication errors, especially underdosing, are prevalent in pediatric outpatient and discharge prescriptions.
- Computer-calculated dosing systems substantially decrease medication errors.
- Addressing prescriber seniority, training, and drug type is crucial for maximizing error reduction.
Background And Objective:
Medication errors are an important cause of hospital-based morbidity and mortality. However, only a few medication error studies have been conducted in children. These have mainly quantified errors in the inpatient setting; there is very little data available on paediatric outpatient and emergency department medication errors and none on discharge medication. This deficiency is of concern because medication errors are more common in children and it has been suggested that the risk of an adverse drug event as a consequence of a medication error is higher in children than in adults.
Objective:
The aims of this study were to assess the rate of medication errors in predominantly ambulatory paediatric patients and the effect of computer calculated doses on medication error rates of two commonly prescribed drugs.
Methods:
This was a prospective cohort study performed in a paediatric unit in a university teaching hospital between March 2003 and August 2003. The hospital's existing computer clinical decision support system was modified so that doctors could choose the traditional prescription method or the enhanced method of computer calculated dose when prescribing paracetamol (acetaminophen) or promethazine. All prescriptions issued to children (<16 years of age) at the outpatient clinic, emergency department and at discharge from the inpatient service were analysed. A medication error was defined as to have occurred if there was an underdose (below the agreed value), an overdose (above the agreed value), no frequency of administration specified, no dose given or excessive total daily dose. The medication error rates and the factors influencing medication error rates were determined using SPSS version 12.
Results:
From March to August 2003, 4281 prescriptions were issued. Seven prescriptions (0.16%) were excluded, hence 4274 prescriptions were analysed. Most prescriptions were issued by paediatricians (including neonatologists and paediatric surgeons) and/or junior doctors. The error rate in the children's emergency department was 15.7%, for outpatients was 21.5% and for discharge medication was 23.6%. Most errors were the result of an underdose (64%; 536/833). The computer calculated dose error rate was 12.6% compared with the traditional prescription error rate of 28.2%. Logistical regression analysis showed that computer calculated dose was an important and independent variable influencing the error rate (adjusted relative risk = 0.436, 95% CI 0.336, 0.520, p < 0.001). Other important independent variables were seniority and paediatric training of the person prescribing and the type of drug prescribed.
Conclusions:
Medication error, especially underdose, is common in outpatient, emergency department and discharge prescriptions. Computer calculated doses can significantly reduce errors, but other risk factors have to be concurrently addressed to achieve maximum benefit.

Related Concept Videos
 01:29
Drug Dosing: Infants and Children
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:01
Dosage Regimens: Partial Pharmacokinetic Parameters
 01:23
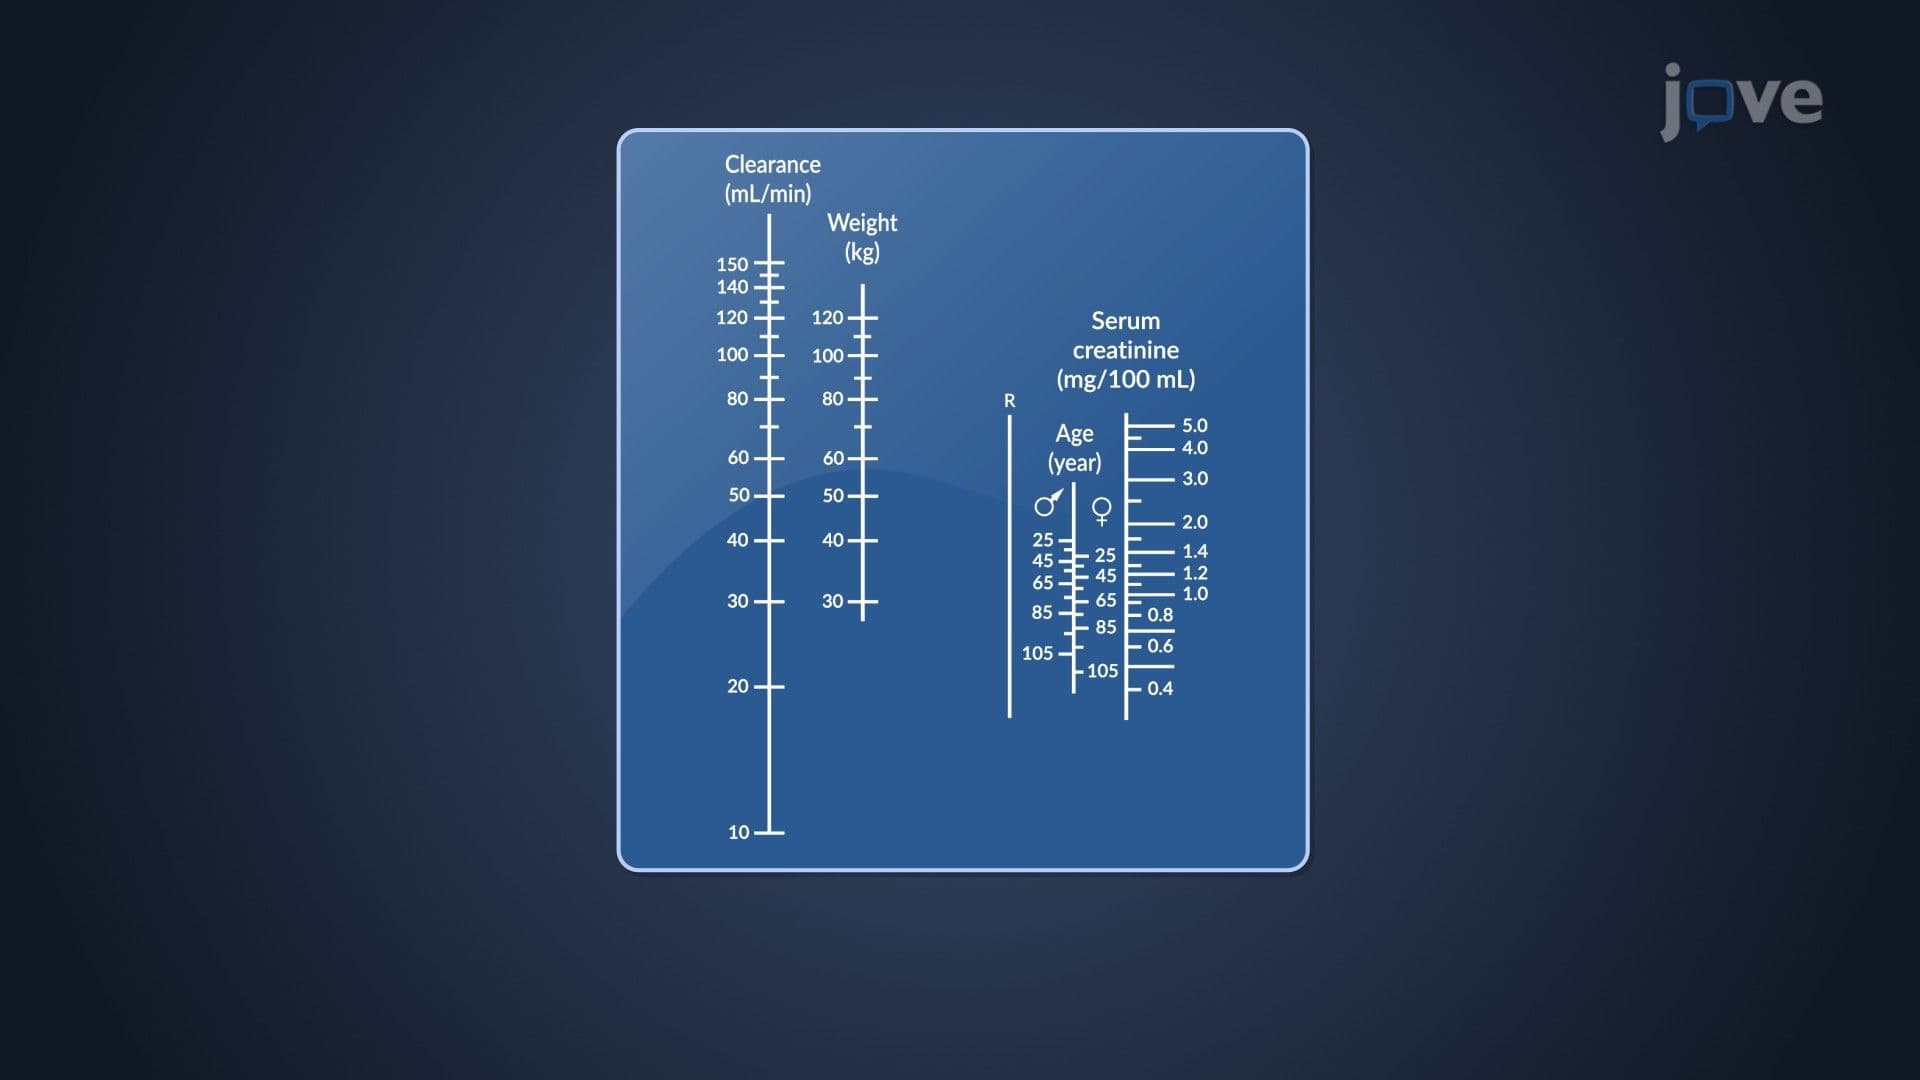
Dosage Regimen Designs: Nomograms and Tabulations